Related Experiment Video
Updated: Jun 13, 2025


Digital Hybrid Model Preparation for Virtual Planning of Reconstructive Dentoalveolar Surgical Procedures
Published on: August 5, 2021
Fully digital occlusion planning in orthognathic surgery - A crossover study
Bogomil Sabev1, Sead Abazi2, Raphael Patcas3
1Oral- and Cranio-Maxillofacial Surgery, Cantonal Hospital Aarau, Tellstrasse, 5001 Aarau, Switzerland; Clinic of Orthodontics and Pediatric Dentistry, Center of Dental Medicine, University of Zurich, Plattenstrasse 11, 8032 Zürich, Switzerland.

Abstract:
Orthognathic surgery enables patients with severe jaw malocclusions to normalise their chewing function and, as such, to improve their quality of life. Over the last few years, digitalisation has been set in motion by intraoral scanners and the improvement of planning software in the field of oral and maxillofacial surgery. Previous studies based on plaster cast models showed that the virtual occlusion based on digitally scanned models can be comparable to conventional methods. This retrospective crossover study aimed to prove that the virtual occlusion finding with the IPS CaseDesigner® (version 2.3.5.2, KLS Martin, Tuttlingen, Germany) is accurate enough to use intraoral scans exclusively.
Materials And Methods:
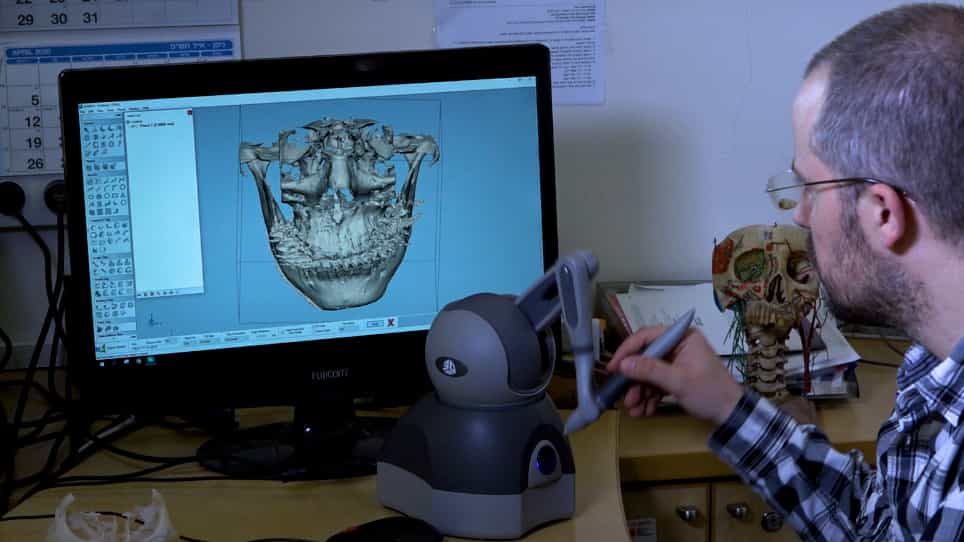
A total of 23 orthognathic surgery patients receiving an intraoral scan for their treatment were included in this study. Two experienced maxillofacial surgeons haptically performed the occlusion finding on three-dimensional (3D) stereolithographic models using the fully digital pathway. One surgeon repeated the procedure a second time to evaluate intra-observer variability. The study aimed to show the difference between these two planning methods by upholding the surgical accuracy of less than 2 mm in translation and 2° in rotation. The conventional haptic occlusion was set as a reference throughout the whole study. The data were tested with a one-sample Wilcoxon test for the fit into the surgical accuracy.
Results:
The difference between the virtual and conventional groups was significantly smaller than the surgical accuracy (all p < 0.001). Both translational movements (anterior/posterior (median 0.51 mm [0.28, 0.88]), left/right (median 0.46 mm [0.20, 0.87]), cranial/caudal (median 0.37 mm [0.11, 0.69])) and rotations (Roll (median 0.71° [0.29, 1.35]), Pitch (median 0.72° [0.29, 1.44]), Yaw (median 1.09° [0.33, 1.60])) were in the range of surgical accuracy (2 mm/2°). The most significant differences were found in the anterior/posterior translation (median 0.51 mm [0.28, 0.88]) and the Yaw rotation (median 1.09° [0.33, 1.60]).
Conclusion:
These results demonstrate that the entirely virtual workflow in orthognathic surgery, including intraoral scanning and the virtual semi-automatic occlusion finding, represents a reliable and state-of-the-art alternative to the conventional haptic method.