Related Experiment Video
Updated: Jul 16, 2026


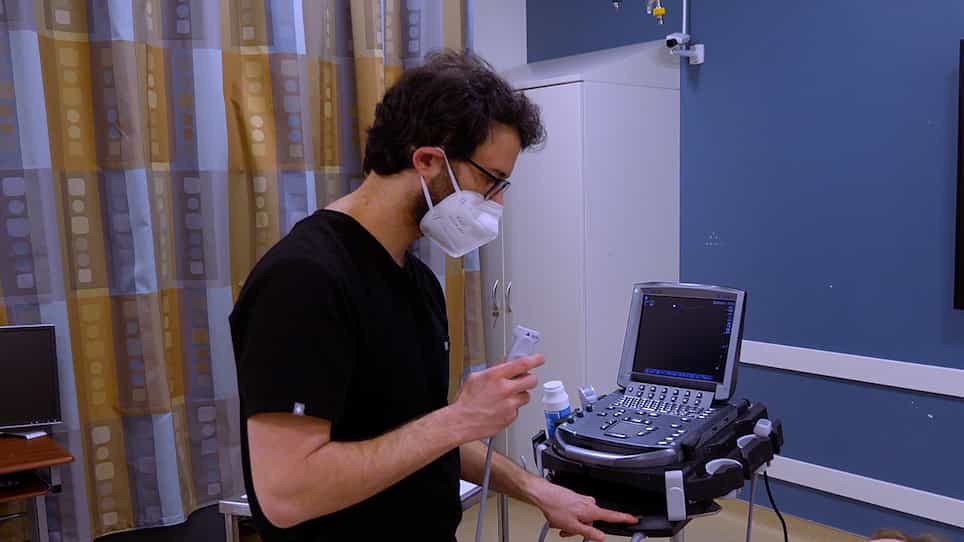
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
Point-of-Care Lung Ultrasound to Evaluate Lung Isolation During One-Lung Ventilation in Children: A Blinded
Alok Moharir1,2, Yoshikazu Yamaguchi3, Jennifer H Aldrink4
1From the Department of Anesthesiology & Pain Medicine, Nationwide Children's Hospital, Columbus, Ohio.

Background:
Minimally invasive thoracic surgical techniques require effective lung isolation using one-lung ventilation (OLV). Verification of lung isolation may be confirmed by auscultation, visual confirmation using fiberoptic bronchoscopy (FOB), or more recently, point-of-care ultrasound (POCUS). The aim of this study was to prospectively compare lung ultrasound with clinical auscultation to confirm OLV before thoracic surgery in pediatric patients.
Methods:
This prospectively blinded feasibility study included 40 patients ranging in age from 0 to 20 years. After confirmation of lung separation by the primary anesthesia team using FOB, the sonographer and the auscultator, both blinded to the laterality of surgery and lung separation, entered the operating room. The sonographer evaluated for pleural lung sliding and the auscultator listened for breath sounds. Successful lung separation was definitively confirmed by direct visualization of lung collapse during the operation.
Results:
In confirming effective single-lung ventilation, lung ultrasound had a diagnostic accuracy of 95% (95% confidence interval [CI], 82.7%-98.5%). In contrast, auscultation could only reliably confirm lung isolation with 68% accuracy (95% CI, 51.5%-80.4%). The McNemar test showed a statistically significant difference between the use of lung ultrasound and auscultation ( P < .001). The median time to perform ultrasonography was 67 seconds (interquartile range [IQR], 46-142) and the median time to perform auscultation was 21 seconds (IQR, 10-32).
Conclusions:
Based on the initial results of our feasibility trial, lung ultrasound proved to be a fast and reliable method to verify single-lung ventilation in pediatric patients presenting for thoracic surgery with a high degree of diagnostic accuracy.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History