Related Experiment Video
Updated: Jun 13, 2025
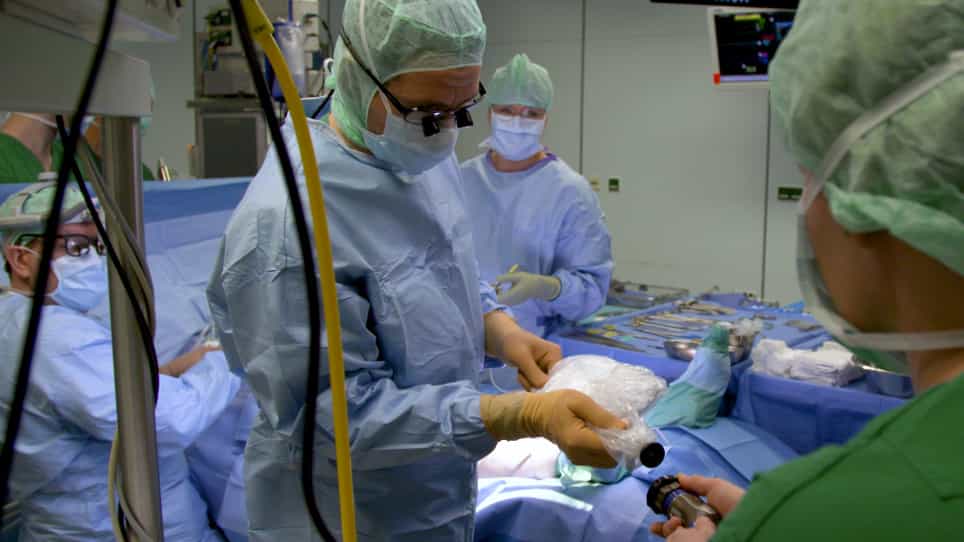

Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
Contemporary Outcomes of Infrainguinal Vein Bypass Surgery for Chronic Limb-Threatening Ischaemia: A Two-Centre
Thomas Lovelock1, Sharan Randhawa2, Cameron Wells2,3
1Department of Vascular Surgery, Waikato Hospital, Hamilton 3204, New Zealand.

Insights
This study on chronic limb-threatening ischaemia (CLTI) found infrainguinal bypass outcomes consistent with BEST-CLI trial results. Male sex and statin use predicted better outcomes, while dialysis dependence worsened them.
Area of Science:
- Vascular Surgery
- Cardiovascular Medicine
Background:
- Chronic limb-threatening ischaemia (CLTI) presents a significant clinical challenge.
- Recent trials (BEST-CLI, BASIL-2) offer divergent treatment strategies for CLTI.
- Investigating infrainguinal bypass outcomes in Aotearoa New Zealand is crucial for local treatment guidelines.
Purpose of the Study:
- To evaluate the outcomes of infrainguinal bypass grafting in patients with CLTI.
- To compare findings with results from major international trials like BEST-CLI and BASIL-2.
- To identify demographic and clinical factors influencing treatment success in CLTI patients.
Main Methods:
- A retrospective review of 119 patients undergoing infrainguinal bypass for CLTI between 2020-2021.
- Primary outcome: composite of death, above-ankle amputation, or major limb reintervention.
- Kaplan-Meier survival analysis and log-rank tests for demographic factor impact.
Main Results:
- The primary composite outcome occurred in 42.8% of patients; death was the most frequent component (26%).
- Male sex and statin use were protective factors against the composite outcome (p<0.05).
- Dialysis dependence independently predicted a higher likelihood of meeting the composite outcome (p=0.018).
Conclusions:
- Infrainguinal bypass outcomes in this New Zealand cohort align with BEST-CLI findings.
- Differences from BASIL-2 may stem from variations in patient populations, disease patterns, and graft conduit choices.
- Further research is needed to personalize CLTI management strategies, balancing open surgery and endovascular approaches.
Abstract:
Background/Objectives: Chronic limb-threatening ischaemia (CLTI) is a significant life and limb-threatening condition. Two recent seminal trials, BEST-CLI and BASIL-2, have provided seemingly conflicting results concerning the optimal treatment modality for patients with CLTI. We sought to investigate the outcomes of patient undergoing infrainguinal bypass at two centres in Aotearoa New Zealand. Methods: A cross-sectional retrospective review of all patients who underwent infrainguinal bypass grafting for CLTI at Auckland City Hospital and Waikato Hospital between January 2020 and December 2021 was performed. The primary outcome was a composite of death, above-ankle amputation, and major limb reintervention. The secondary outcome was minor limb reintervention. Kaplan-Meier survival analysis was performed to determine time to the primary and secondary endpoints. Demographic factors were examined using the log-rank test to examine the effect on the outcome. Results: One hundred and nineteen patients who underwent infrainguinal bypass for CLTI in the study period were identified. Of these, 93 patients had a bypass with ipsilateral or contralateral GSV. The median follow-up time was 1.85 years. The most common indication for surgery was tissue loss (69%, n = 63), with the most common distal bypass target being the below-knee popliteal artery (45%, n = 41). The primary composite outcome occurred in 42.8% of the cohort (n = 39). Death was the most common component of the primary outcome (26%, n = 24). Male sex (HR 0.48, 95% CI 0.26-0.88, p = 0.018) and statin use (HR 0.49, 95% CI 0.24-0.98, p = 0.044) were independent predictors of protection from the composite outcome on multivariate analysis. Dialysis dependence (HR 3.32, 95% CI 1.23-8.99, p = 0.018) was an independent predictor for patients meeting the composite outcome. Conclusions: This study's results are consistent with the published outcomes of BEST-CLI. The patient cohorts examined, anatomical disease patterns, and conduit use may explain some of the differences observed between this study, BEST-CLI and BASIL-2. Further work is required to define the specific patient populations who will benefit most from an open surgical or endovascular first approach to the management of CLTI.
More Related Videos


Related Concept Videos
 01:15
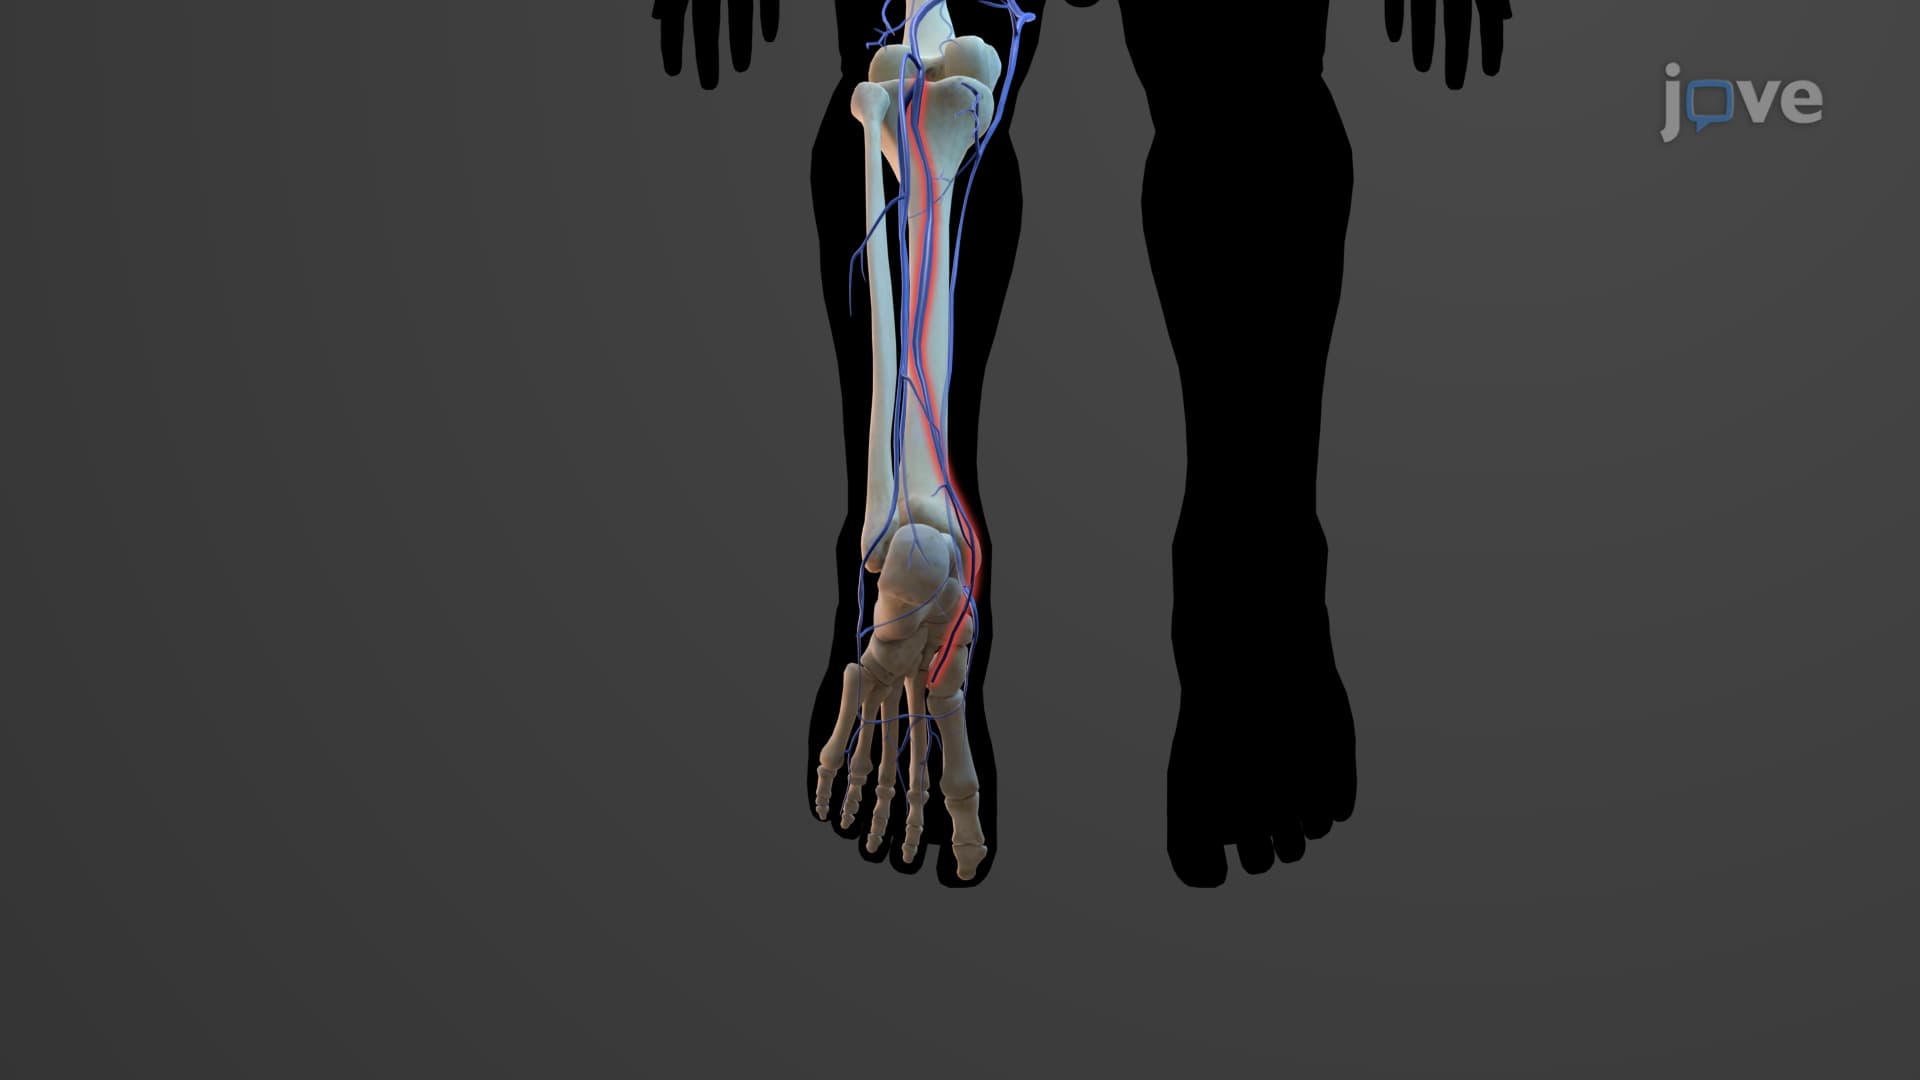
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:04
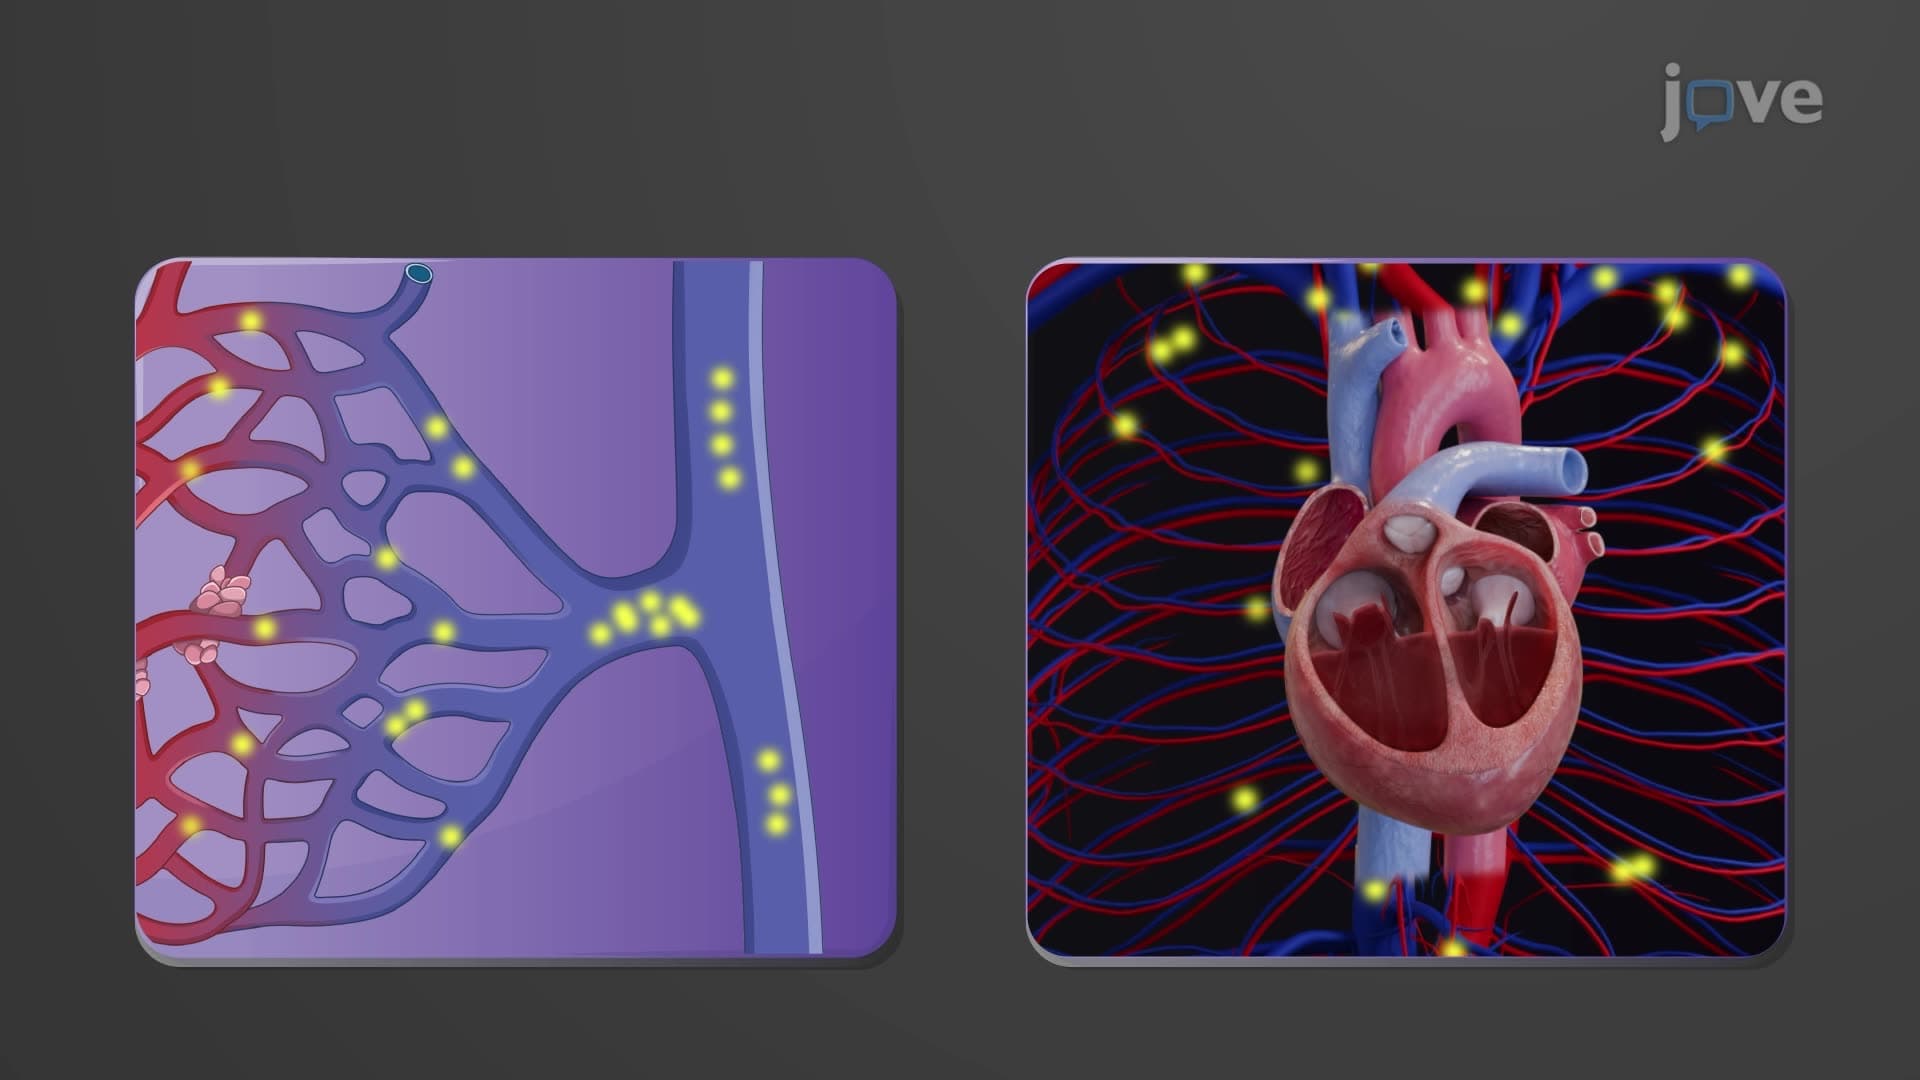
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...