Related Experiment Video
Updated: Jun 13, 2025


Imaging of the Microstructural Failure Mechanism in the Human Hip
Published on: September 29, 2023
[Greenstick fractures of the forearm shaft-Is it obligatory or facultative to break the cortex?]
Thomas Petnehazy1, Martin Münnich2, Ferdinand Füsi2
1Universitätsklinik für Kinder- und Jugendchirurgie, Medizinische Universität Graz, Auenbruggerplatz 34, 8036, Graz, Österreich. thomas.petnehazy@uniklinikum.kages.at.

Background:
To break or not to break-That is the question that has been asked in pediatric traumatology for many years regarding the treatment of greenstick fractures of the diaphyseal forearm shaft.
Objective:
The frequency of greenstick fractures of the forearm shaft in children and adolescents; the influence of breaking the fracture on the refracture rate.
Methods:
Analysis and discussion of relevant articles, analysis of the refracture rate of pediatric greenstick fractures of the forearm shaft in our own patient population.
Results:
Greenstick fractures frequently occur in the area of the forearm shaft and incomplete consolidation leads to an increased refracture rate. In the patient collective of the authors of 420 children with greenstick fractures of the diaphyseal forearm, there was a refracture rate of 9.5%; however, the rate for non-completed fractures was significantly higher compared to the group with completed fractures (15.2% vs. 3%). While in the subgroup of conservatively treated fractures (n = 234), breaking the intact cortex significantly reduced the refracture rate, breaking the intact cortical bone during surgical treatment with elastic stable intramedullary nailing (ESIN) did not change the refracture rate.
Conclusion:
As part of the conservative treatment of greenstick fractures of the diaphyseal forearm, completing the fracture can be recommended in order to lower the refracture rate. Completing the fracture does not appear to be necessary during surgical treatment using ESIN.
More Related Videos
 08:04
Proximal Cadaveric Femur Preparation for Fracture Strength Testing and Quantitative CT-based Finite Element Analysis
Published on: March 11, 2017
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:15
Bones of the Upper Limb: Ulna
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:19
Bones of the Upper Limb: Humerus
 01:09
Bones of the Upper Limb: Radius
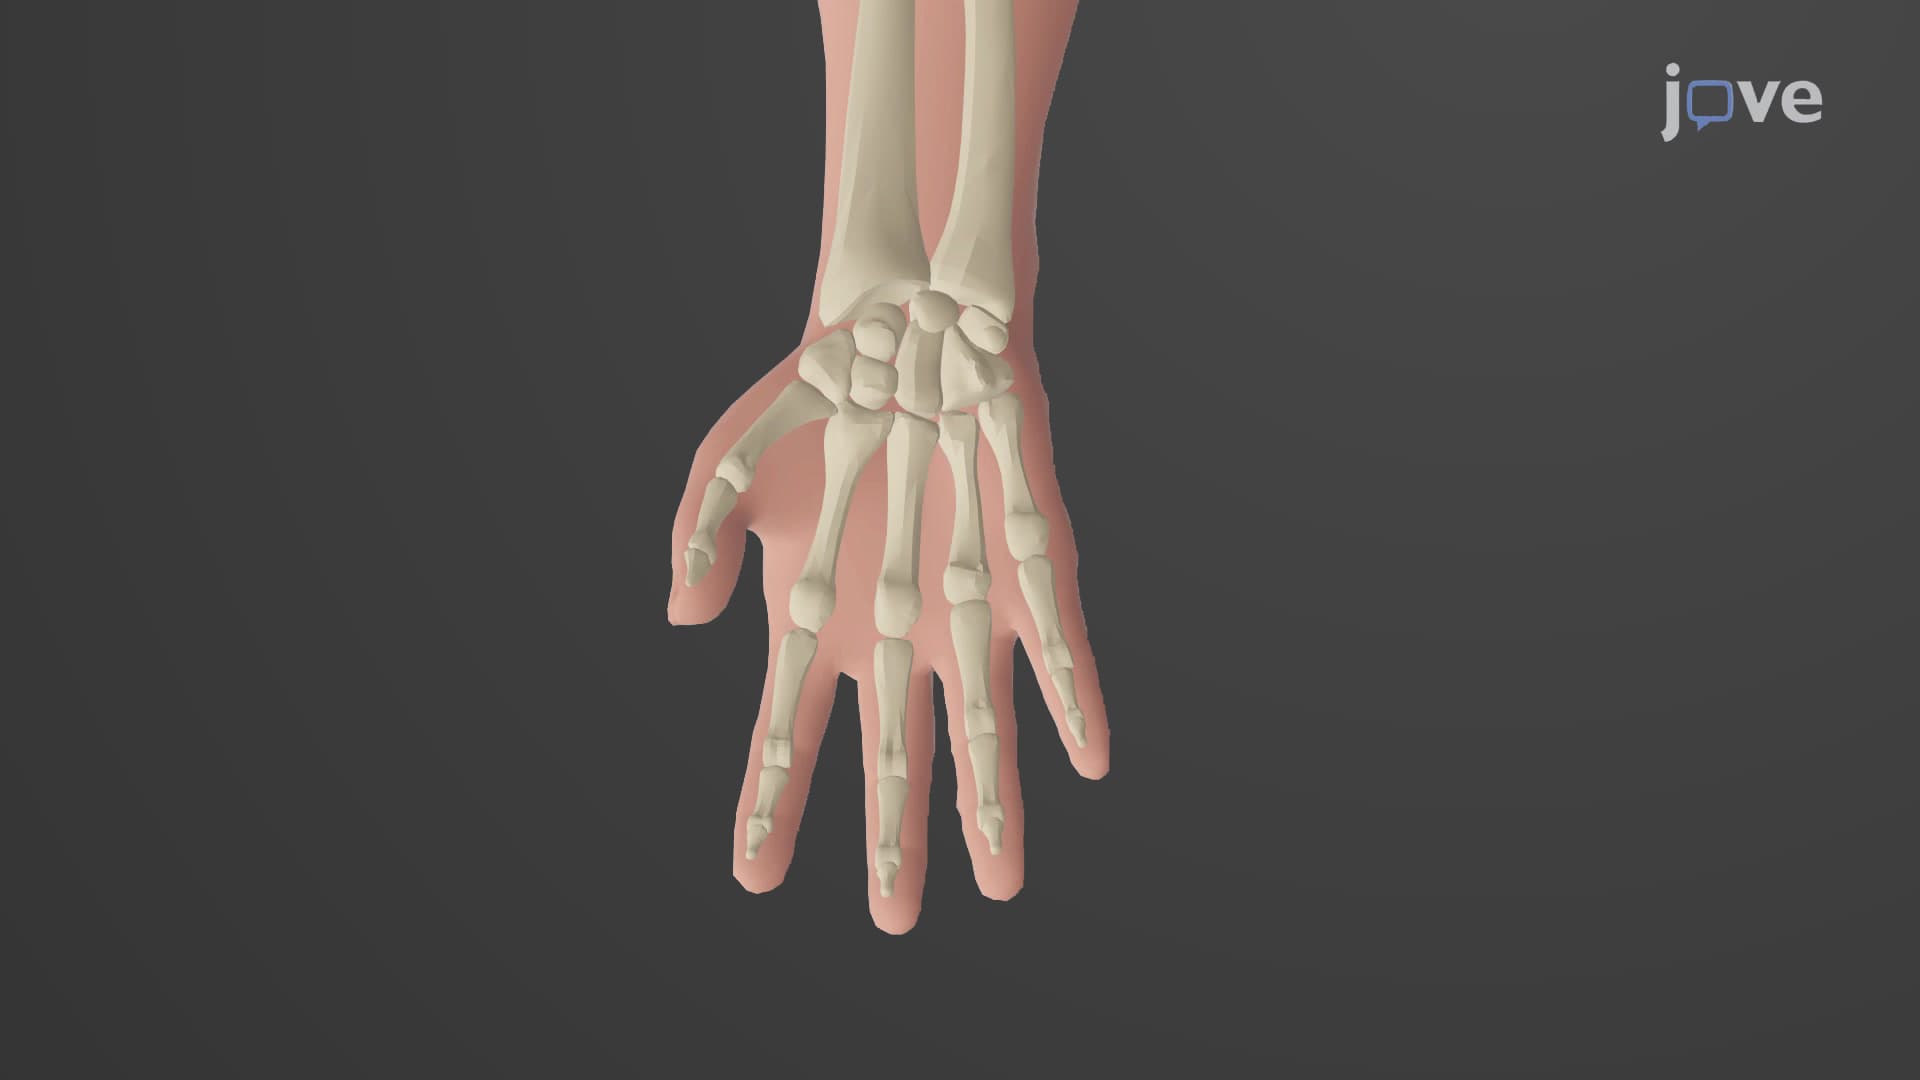
The radius has a nail-shaped head, and a...
 01:17
Gross Anatomy of Bone
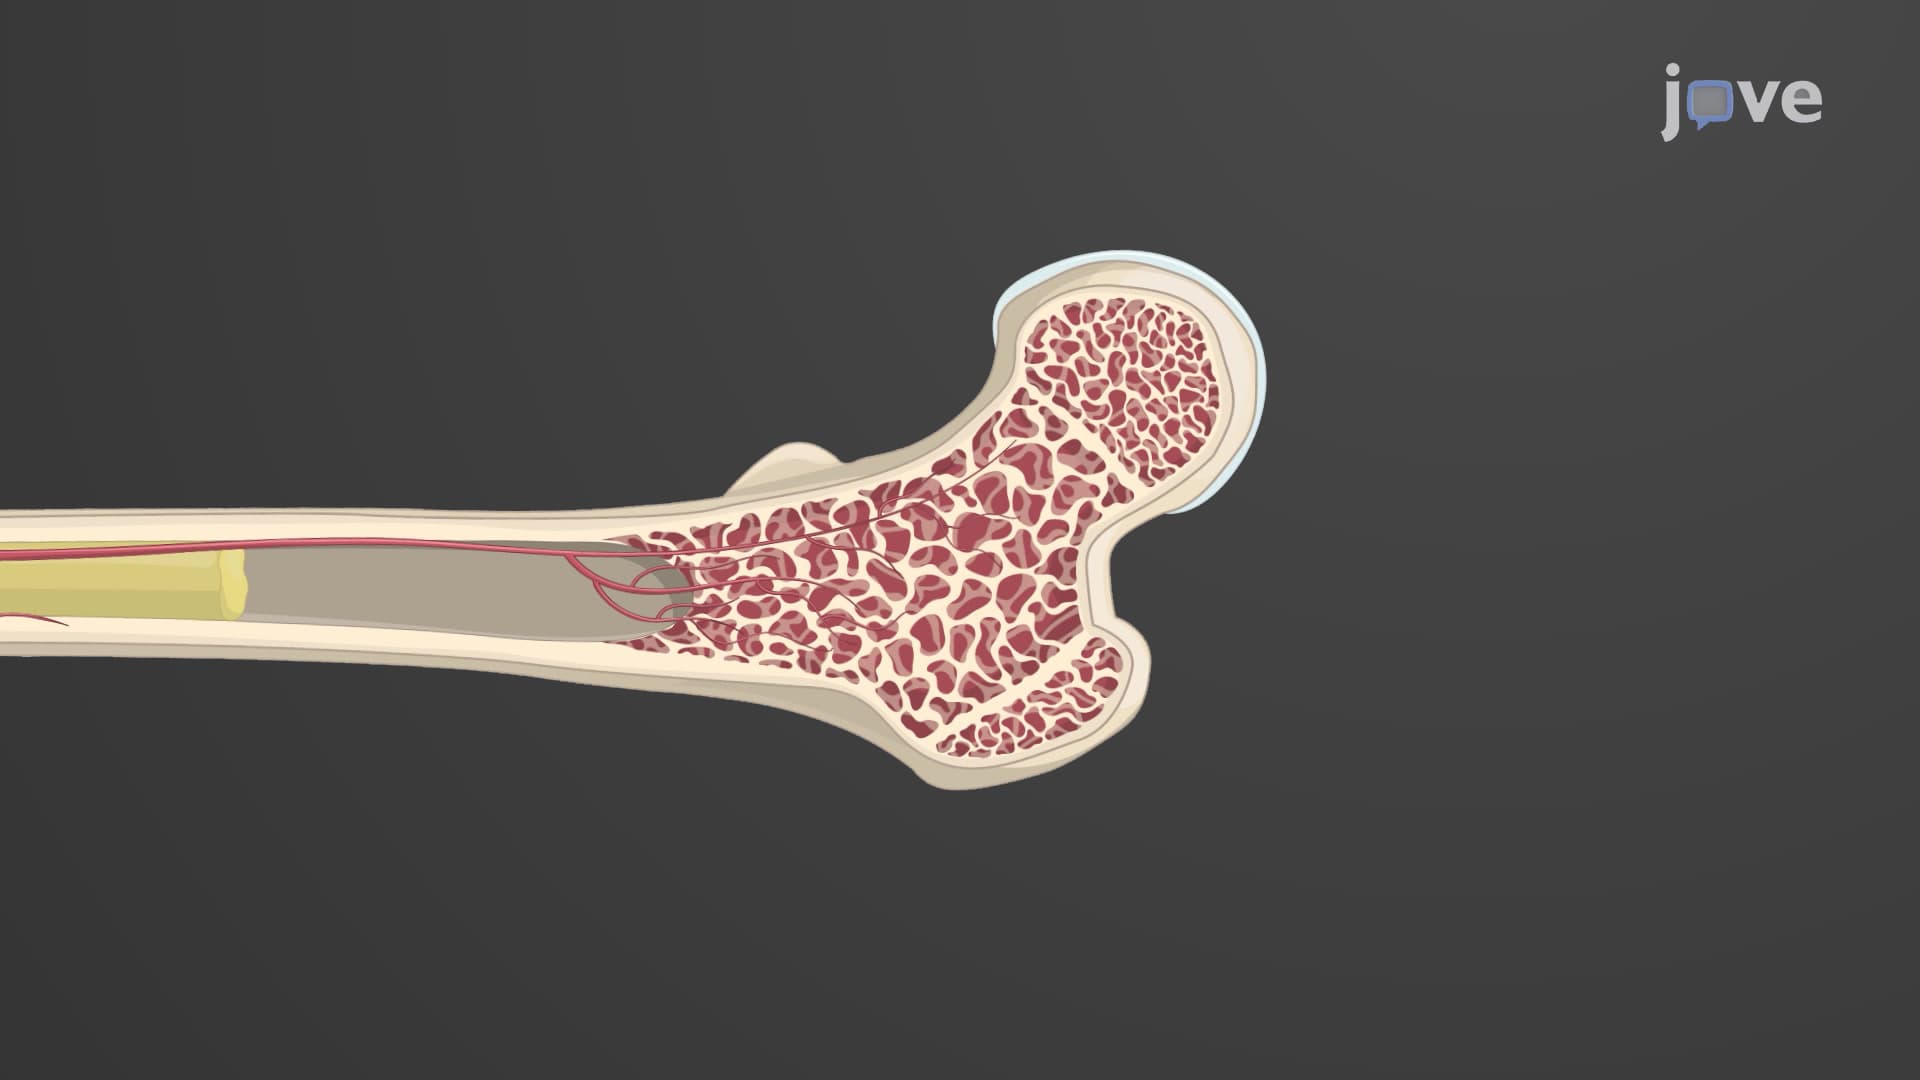
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...
 01:27
Compact Bone
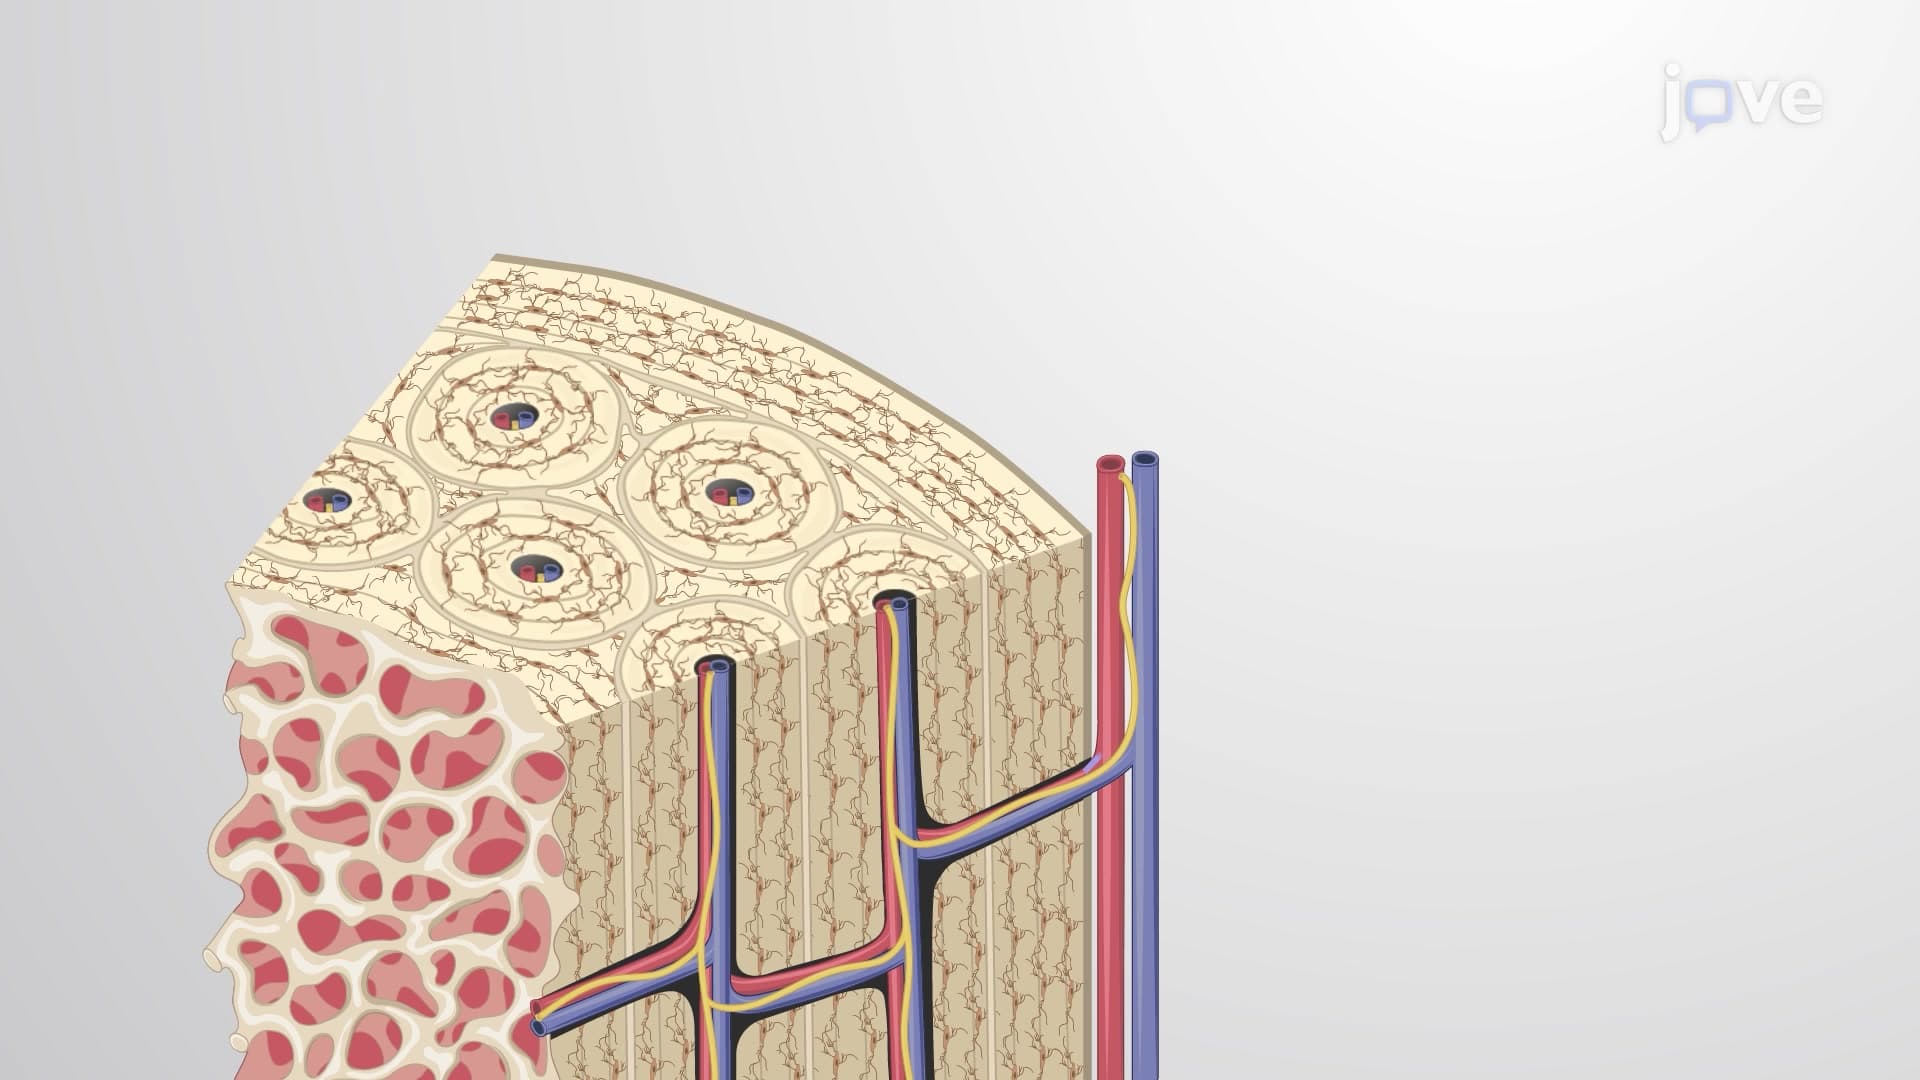
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...