Related Experiment Video
Updated: Jun 12, 2025

Bile Duct Ligation in Mice: Induction of Inflammatory Liver Injury and Fibrosis by Obstructive Cholestasis
Published on: February 10, 2015
Correlation of bilirubin and toxic bile acids in critically ill patients with cholestatic liver dysfunction and
Caroline Gräfe1, Helen Graf2, Vassilissa Wustrow2
1Department of Anesthesiology, LMU University Hospital, LMU Munich, Marchioninistrasse 15, 81377, Munich, Germany. caroline.graefe@med.uni-muenchen.de.

Abstract:
Bilirubin is one of the most frequently used laboratory values to monitor critically ill patients with cholestatic liver dysfunction. Besides bilirubin, toxic bile acids (TBAs), which may cause severe organ damage, are typically elevated. A correlation between both parameters seems plausible, but data are lacking. The aim was to investigate whether there is a correlation between bilirubin and TBAs in patients' blood and whether a compareable reduction can be observed during the use of the adsorber CytoSorb (CS). As part of the Cyto-SOLVE study (NCT04913298), 16 critically ill patients with cholestatic liver dysfunction, bilirubin concentration > 10 mg/dl, continuous kidney replacement therapy and CS-application were investigated. Bilirubin and TBA concentrations were measured from arterial blood at defined time points (before start, after 6 and 12 h). Relative reduction (RR) was calculated using the formula[Formula: see text]. A moderate to high correlation between bilirubin and TBA concentration at all defined timepoints (rstart=0.64, p = 0.008; r6h = 0.85, p < 0.001, r12h = 0.72, p = 0.002) was observed. In the first six hours of CS-application, a significant elimination of TBA (median TBA: 30.8→20.1µmol/l, p < 0.001) and bilirubin (median bilirubin: 17.1→11.9 mg/dl, p < 0.001) was observed. The median RR after 6 h was 26.1% and 39.8% for bilirubin and TBA, respectively. No further reduction was observed after 12 h (RRbilirubin: - 0.6%, RRTBA: 1.8%). There was an at least moderate correlation between bilirubin and TBA in patients with cholestatic liver dysfunction. Therefore, bilirubin seems to be a suitable surrogate parameter for TBA elimination during CytoSorb application.
More Related Videos


Related Concept Videos
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...
 01:14
Prevention of Further Absorption of Poison
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
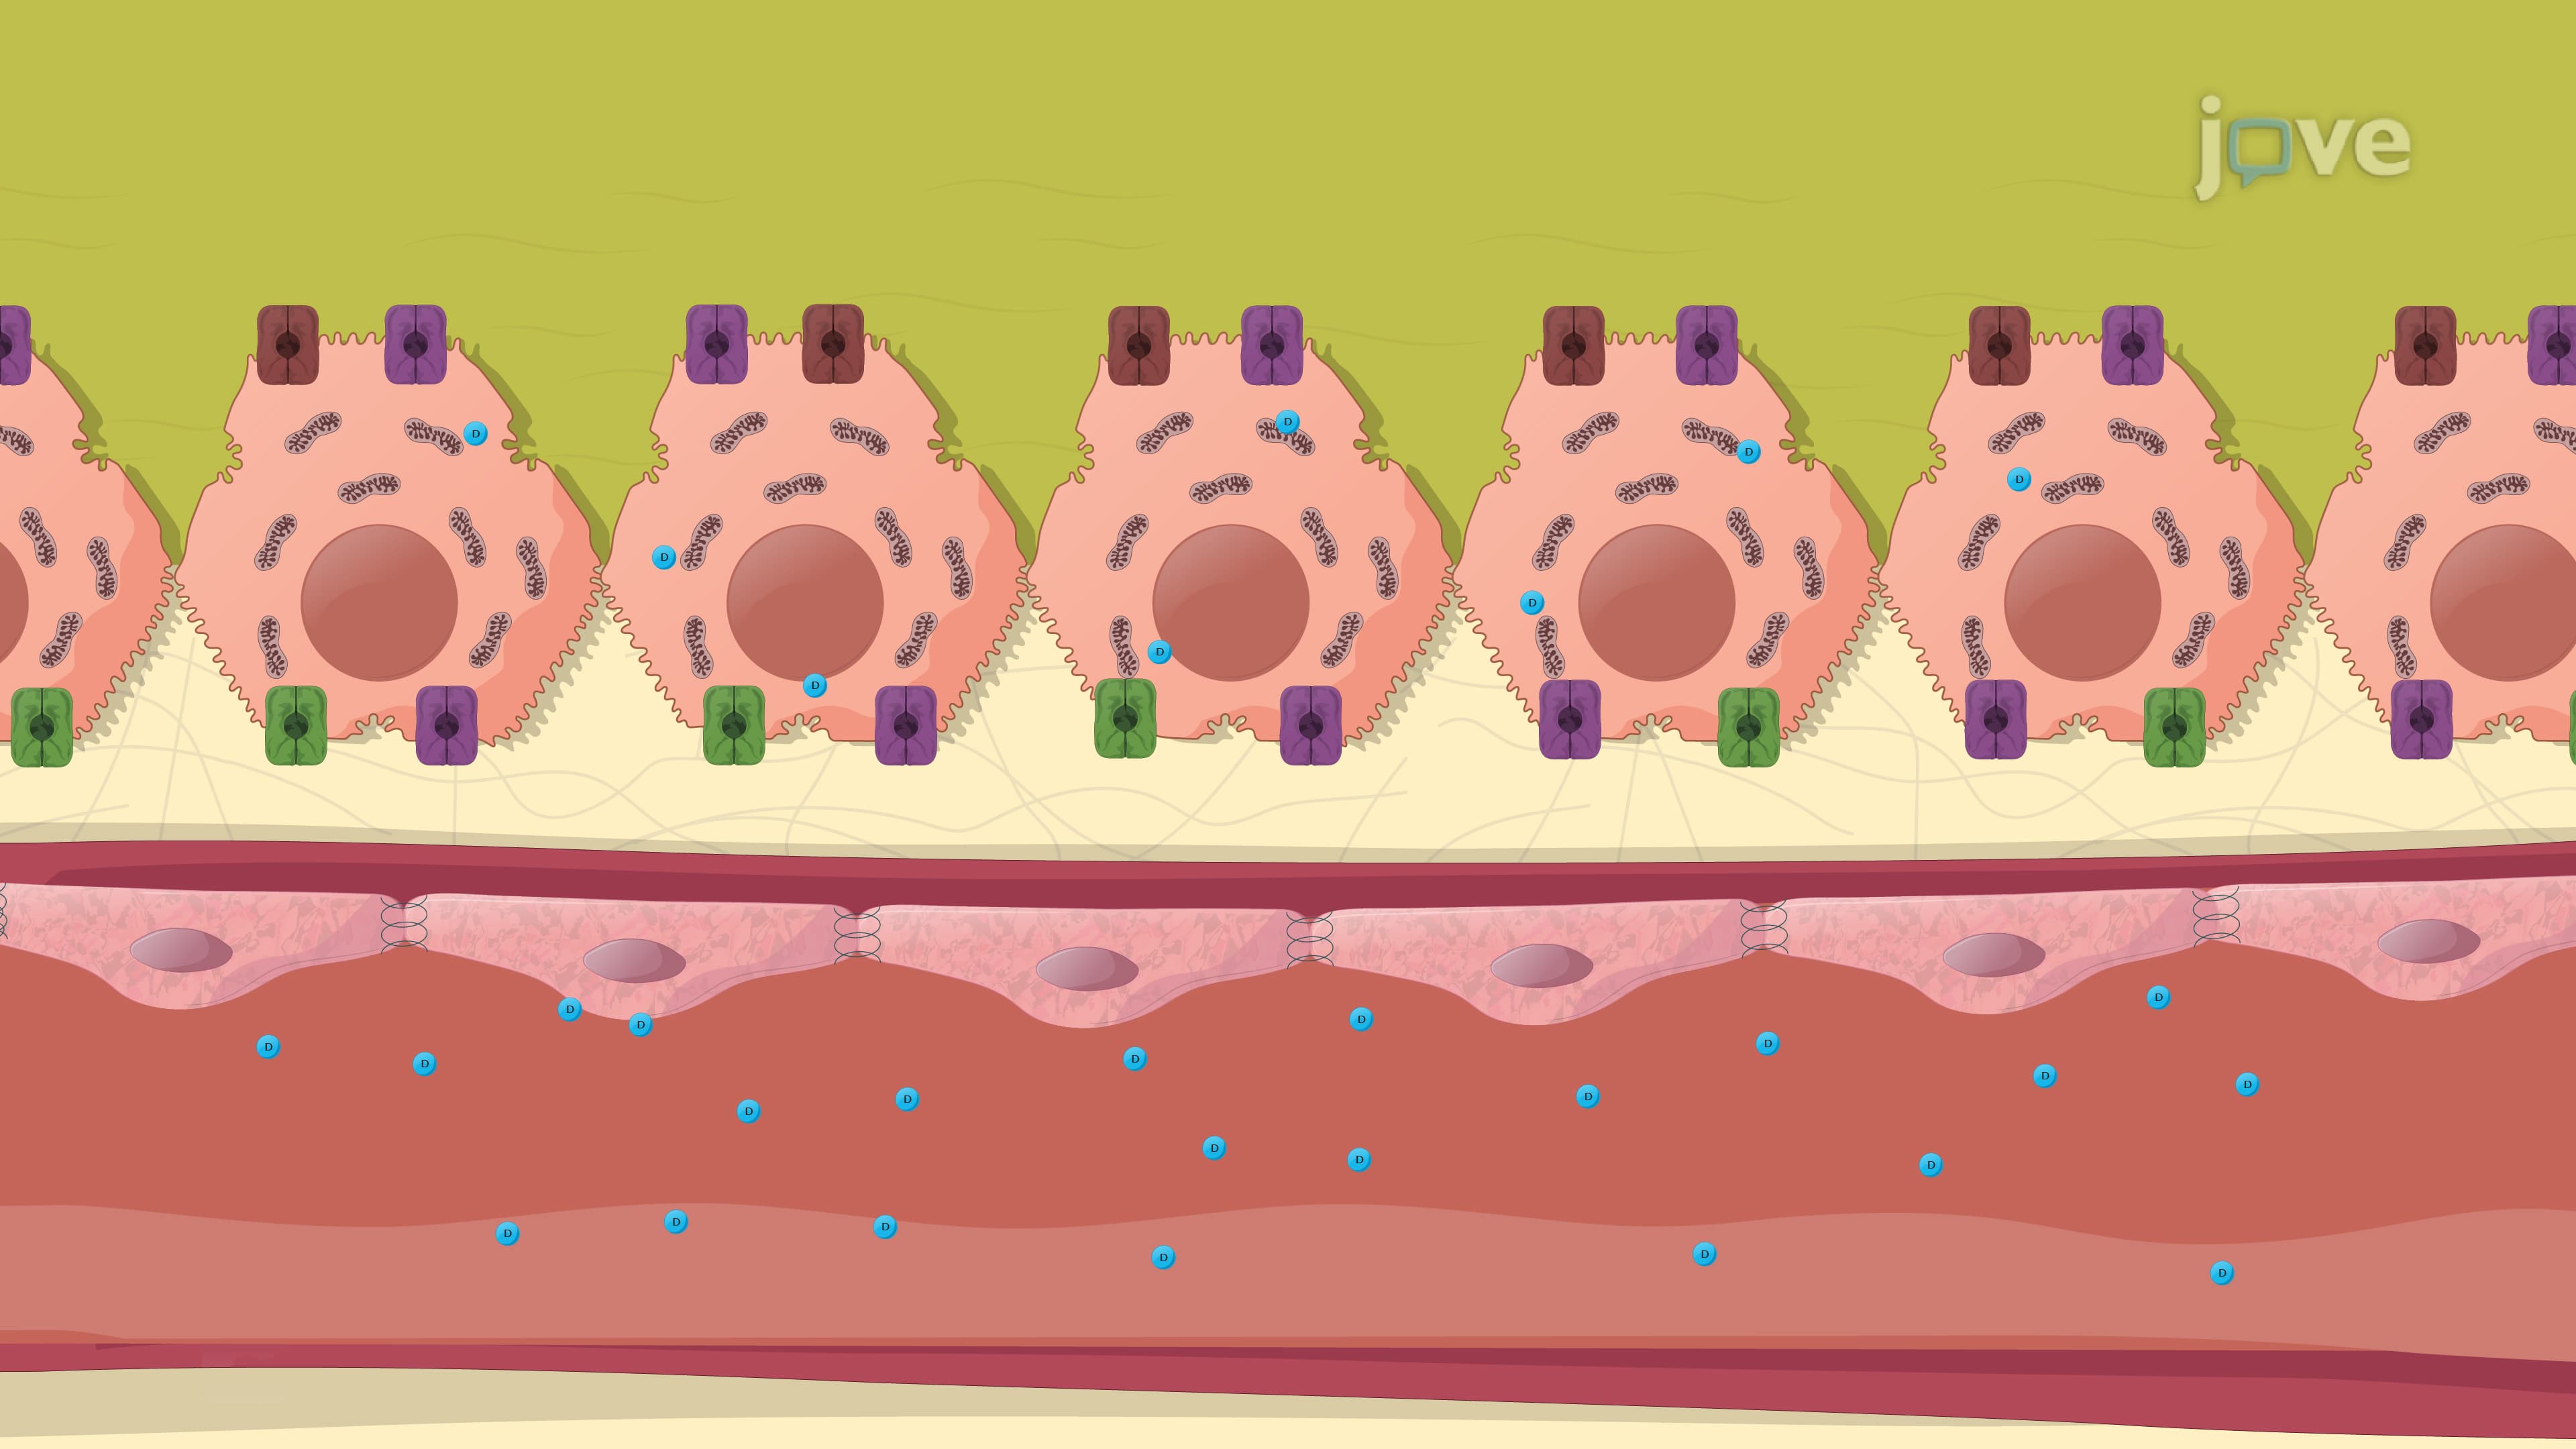 01:14
Hepatic Drug Clearance: Role of Transporters