Related Experiment Video
Updated: Jun 12, 2025


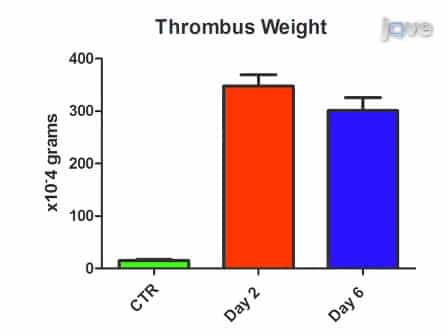
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
A composite risk assessment model for venous thromboembolism
Mary Sixian Lin1, Hilary Hayssen1, Minerva Mayorga-Carlin1
1Department of Surgery, University of Maryland School of Medicine, Baltimore, MD.

Objective:
Venous thromboembolism (VTE) is a preventable cause of hospitalization-related morbidity and mortality. VTE prevention requires accurate risk stratification. Federal agencies mandated VTE risk assessment for all hospital admissions. We have shown that the widely used Caprini (30 risk factors) and Padua (11 risk factors) VTE risk-assessment models (RAMs) have limited predictive ability for VTE when used for all general hospital admissions. Here, we test whether combining the risk factors from all 23 available VTE RAMs improves VTE risk prediction.
Methods:
We analyzed data from the first hospitalizations of 1,282,014 surgical and non-surgical patients admitted to 1298 Veterans Affairs facilities nationwide between January 2016 and December 2021. We used logistic regression to predict VTE within 90 days of admission using risk factors from all 23 available VTE RAMs. Area under the receiver operating characteristic curves (AUC), sensitivity, specificity, and positive (PPV) and negative predictive values (NPV) were used to quantify the predictive power of our models. The metrics were computed at two diagnostic thresholds that maximized (1) the value of sensitivity + specificity-1; and (2) PPV and were compared using McNemar's test. The Delong-Delong test was used to compare AUCs.
Results:
After excluding those with missing data, 1,185,633 patients (mean age, 66 years; 93% male; and 72% White) were analyzed, of whom 33,253 (2.8%) had a VTE (deep venous thrombosis [DVT], n = 19,218, 1.6%; pulmonary embolism [PE], n = 10,190, 0.9%; PE + DVT, n = 3845, 0.3%). Our composite RAM included 102 risk factors and improved prediction of VTE compared with the Caprini RAM risk factors (AUC composite model: 0.74; AUC Caprini risk-factor model: 0.63; P < .0001). When the sum of sensitivity and specificity-1 was maximized, the composite model demonstrated small improvements in sensitivity, specificity and PPV; NPV was high in both models. When PPV was maximized, the PPV of the composite model was improved but remained low. The nature of the relationship between NPV and PPV precluded any further gain in PPV by sacrificing NPV and sensitivity.
Conclusions:
Using a composite of 102 risk factors from all available VTE RAMs, we improved VTE prediction in a large, national cohort of >1 million general hospital admissions. However, neither model has a sensitivity or PPV that permits it to be a reliable predictor of VTE. We demonstrate the limits of currently available VTE risk prediction tools; no available RAM is ready for widespread use in the general hospital population.

Related Concept Videos
 01:04
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:29
Assessment of the Cardiovascular System II: Inspection
Head and Neck