Related Experiment Video
Updated: Jun 12, 2025
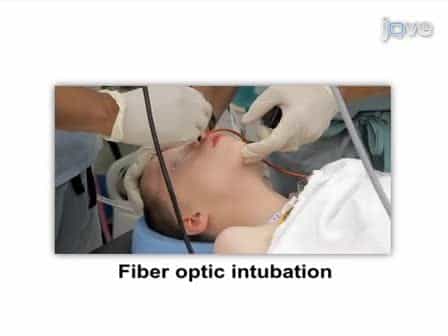

Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Vigilant Fiberoptic Orotracheal Intubation in a Patient With Severe Craniofacial Trauma During the Last Morocco
Mehdi Nabil1, Said Khallikane2, Abdeljalil Abouchadi3
1Anesthesiology and Reanimation, Military Hopital of Avicenne, Marrakech, MAR.

Abstract:
Maxillofacial trauma is prevalent, particularly among the young population, often stemming from assaults, road accidents, or sports-related mishaps. Traditional intubation methods for managing these injuries can be challenging, especially with occluso-facial fractures requiring intermaxillary blocking for dental articulation restoration. Effective management requires interdisciplinary collaboration between emergency physicians, anesthetists, and maxillofacial surgeons. Proficiency in techniques like the vigilant fiberoptic approach should be emphasized through specialized training courses. This collaborative approach ensures the best possible strategy for managing difficult airways, with input from all stakeholders including patients, students, and practitioners. In this case, we successfully conducted a rapid-sequence awake fiberoptic oral intubation on a trauma patient, during the last earthquake that hit Morocco, with severe craniofacial injuries and an unstable skull. The patient, a 40-year-old woman, presented with complex facial fractures, including hemi lefort III on the right and hemi lefort II on the left, along with minimal subarachnoid hemorrhage and frontal pneumocephalus. Due to the patient's compromised airway from diffuse facial bleeding and low oxygen saturation, we opted for awake fiberoptic intubation once immediate life-threatening issues were addressed. This approach allowed us to maintain the patient's spontaneous respirations and navigate around unstable craniofacial structures. The procedure was performed with meticulous care, considering the patient's unstable skull, and was successful without complications. Post-intubation, the patient was extubated, and her recovery was uneventful.


Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...