Related Experiment Video
Updated: Jul 31, 2026
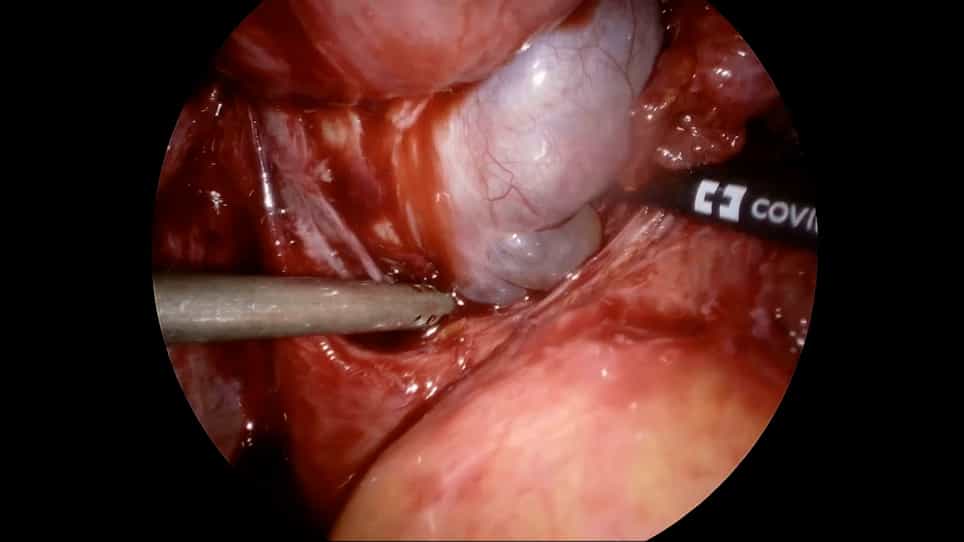
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Selected overview of nongynecologic surgical intra-abdominal infections. Prophylaxis and therapy

Abstract:
True prophylaxis of intra-abdominal nongynecologic infections is limited to elective, nonemergency surgery and is best shown in three clean-contaminated surgical procedures. All of these have an infection rate of approximately 10 to 20 percent and include all colon resection surgery, most gastric surgery, and about one third of the cholecystectomies for chronic calculous cholecystitis. Each of these three surgical procedures has a somewhat different pattern of bacterial pathogens. The most useful comparative studies of early preoperative therapy have been performed in cases of suspected appendicitis (50 percent of which usually show perforation or gangrene at the time of surgery) and penetrating abdominal wounds (80 percent of which usually enter some part of the bowel and theoretically soil the peritoneum). These procedures are usually classified as contaminated, with a 20 to 30 percent infection rate, or dirty, with a more than 30 percent infection rate, depending upon several factors. Comparative investigations of intraoperative and postoperative antibiotic therapy of established intra-abdominal infections are more difficult to obtain because of the heterogeneity of the sites, organisms, and medical and surgical therapy. The initial pathogens causing secondary peritonitis and hepatic, perirectal, diverticular, and most other types of intraperitoneal abscesses are mixed coliforms and anaerobes, with emphasis on the anaerobes. Retroperitoneal abscesses, pancreatic abscesses, and biliary tract infections are predominantly caused by coliforms. The organisms responsible for these early infections are usually community-acquired rather than more antibiotic-resistant hospital-acquired bacteria. Considering the availability of a large number of effective broad-spectrum antibacterial agents and therapeutic combinations, it has become increasingly difficult to assess the rightful place of any new prospective antimicrobial regimen unless it has quite unique characteristics. Most empiric therapy in established intra-abdominal infection studies have compared gentamicin and clindamycin, the most popular regimen in the United States over the past 15 years, with a cephalosporin, broad-spectrum penicillin, or aminoglycoside, either alone or together with clindamycin or metronidazole. Results have usually been considered similar in most studies, although in some studies, agents with limited Bacteroides fragilis activity, such as cefamandole or cefaperazone, have been considered inferior. Most new prophylactic regimens have been compared with the first-generation cephalosporins and, again, similar results have been obtained between the groups with two exceptions. Cepha
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:17
Urinary Tract Infection IV: Nursing Management
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:25
Urinary Tract Calculi VI: Surgical Management