Related Experiment Video
Updated: May 31, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Long-term respiratory consequences of prematurity
1Department of Pediatrics, Division of Respiratory Medicine and Allergology, Erasmus University Medical Center- Sophia Children's Hospital, Rotterdam, the Netherlands.

Insights
Preterm birth, affecting 10% of children globally, often leads to lasting respiratory issues and reduced lung function. Even moderate preterm birth impacts lung health, necessitating tailored, multidisciplinary care for affected children.
Area of Science:
- Pediatric Pulmonology
- Neonatology
- Public Health
Background:
- Preterm birth affects approximately 10% of children worldwide.
- Respiratory complications are common sequelae of preterm birth.
- Impaired lung function in preterm infants can persist into adulthood.
Purpose of the Study:
- To highlight the long-term respiratory consequences of preterm birth.
- To emphasize that lung function deficits are observed across the spectrum of prematurity.
- To advocate for phenotype-based management of prematurity-associated lung disease.
Main Methods:
- Review of existing literature on respiratory outcomes in preterm infants.
- Analysis of lung function data in preterm-born children.
- Discussion of the heterogeneity of lung disease in prematurity.
Main Results:
- Preterm birth is associated with increased respiratory symptoms and hospital admissions.
- Lower lung function Z-scores are found in preterm-born children, including those born moderate-late preterm.
- Lung function impairment can extend into adulthood.
Conclusions:
- Preterm birth has significant and lasting impacts on respiratory health.
- Lung function deficits are not limited to extremely preterm infants.
- Multidisciplinary, phenotype-based management is crucial for improving respiratory outcomes in preterm-born individuals.
Abstract:
Approximately 10% of all children worldwide are born preterm and respiratory consequences are amongst the most common sequelae of preterm birth. Except for a higher prevalence of respiratory symptoms and hospital admissions, preterm birth is associated with lower lung function that may track into adulthood. Lung function impairment is not restricted to extreme or very preterm-born subjects as also children born moderate-late preterm have lower Z-scores for lung function. Given the heterogeneity of prematurity-associated lung disease, phenotype-based, multidisciplinary management is needed to improve respiratory health in preterm-born subjects.


Related Concept Videos
 01:05
Breathing
 01:17
Pulmonary Cycle: Exhalation
 01:17
Other Pulmonary Disorders
 01:23
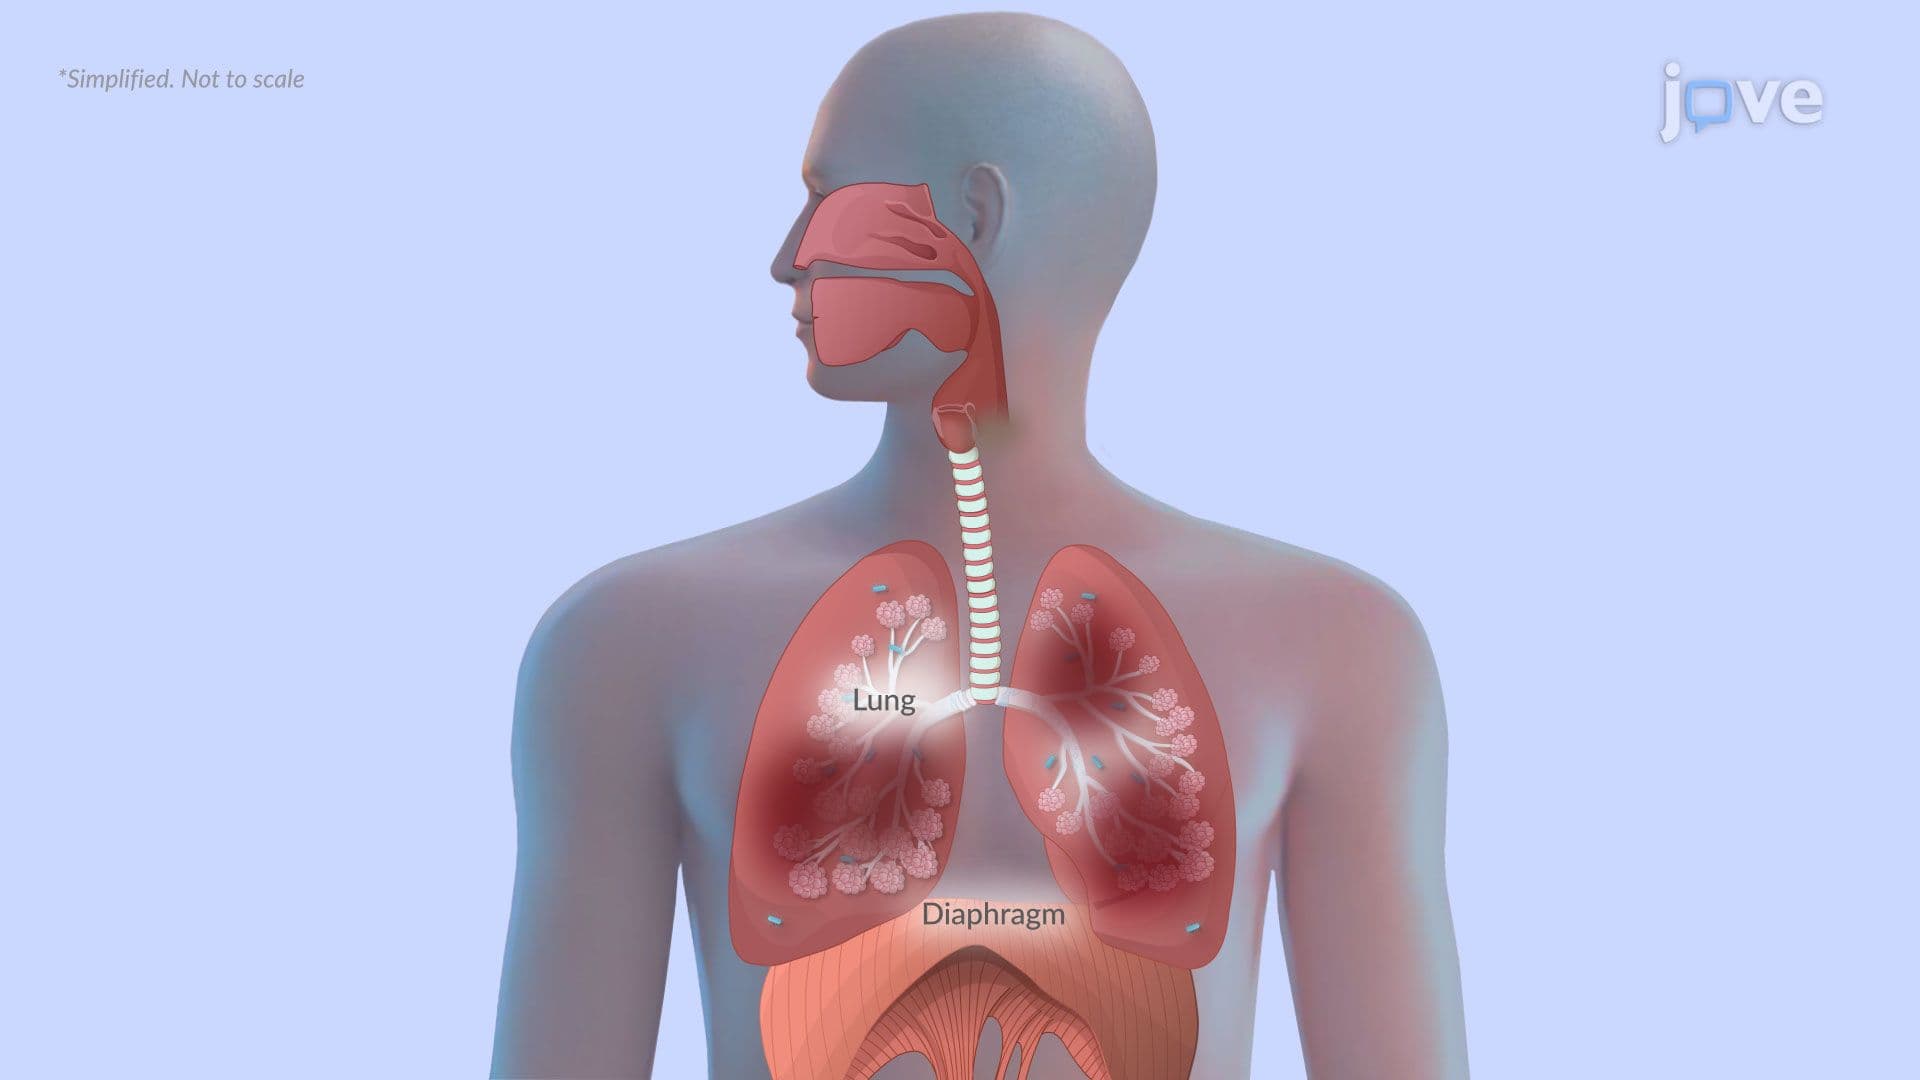
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features