Related Experiment Video
Updated: Jun 11, 2025
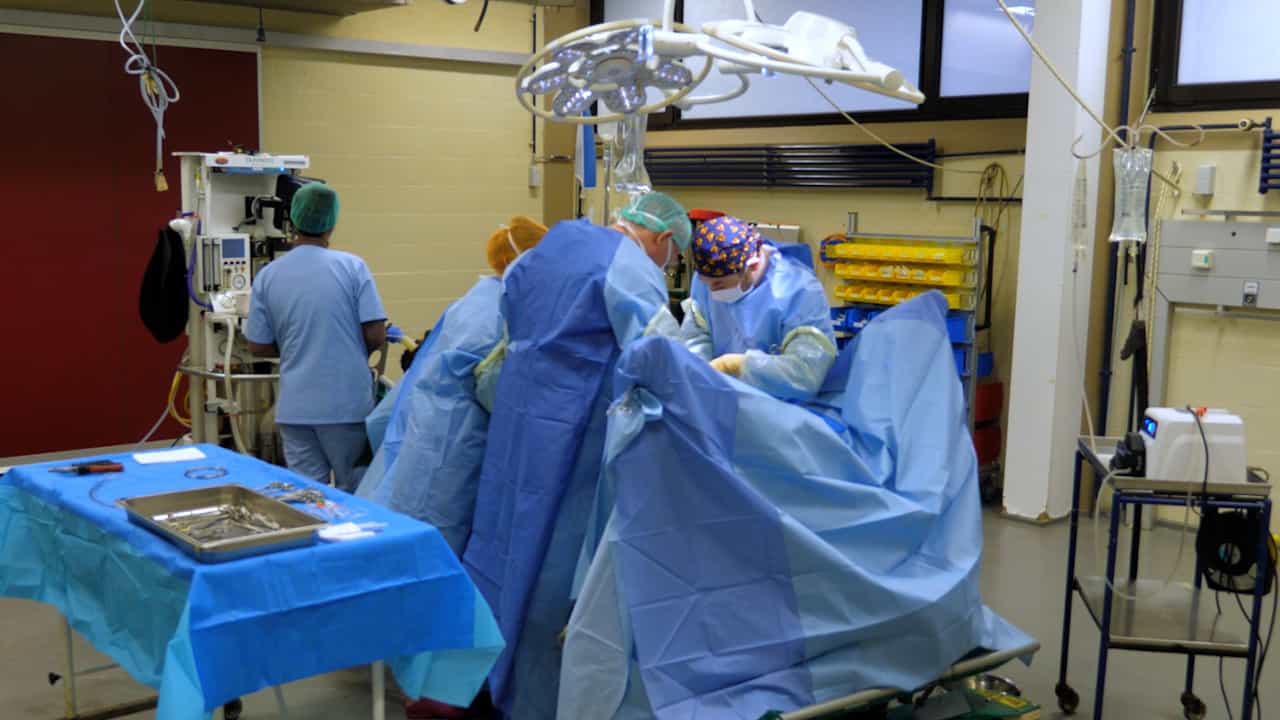
Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
Delayed primary skin closure reduce surgical site infection following surgery for gastrointestinal perforation: A
Cangyuan Zhang1, Jiajie Zhou2, Longhe Sun3,4
1Shandong Public Health Clinical Center , Shandong University, Jinan, 250013, China.

Background:
Following surgery for Gastrointestinal (GI) perforation, there is an increased occurrence of Surgical Site Infections (SSI). The beneficial effect of employing delayed primary skin closure (DPC) on severely contaminated incisions subsequent to surgery for GI perforation remains unverified.
Objective:
To systematically evaluate the advantages of the DPC management in surgery for GI perforation.
Methods:
A literature search was performed using ClinicalTrials.gov, Pubmed, Embase, Cocharane, and Web of Science identified all eligible English-language studies related to surgery for GI perforation through October 2023. Randomized clinical trials (RCTs) comparing DPC with primary skin closure (PC) in surgery for GI perforation were included. Two investigators independently performed the inclusion work, and a third investigator was consulted for resolving conflicts. Data were extracted by multiple independent investigators and pooled in a random-effects model. The primary outcome was SSI, defined in accordance with the original studies. The secondary outcome was the length of stay (LOS).
Results:
Final analysis included 12 RCTs which included a total of 903 patients were randomizing divided into either DPC or PC, including 289 patients with gastroduodenal perforation (32%), 144 patients with small intestine perforation (15.96%), 60 patients with colon perforation (6.64%), and 410 patients with appendix perforation (45.4%). The rates of SSI was significantly decreased after DPC management (OR:0.31, 95%CI:0.15-0.63, p < 0.01), no significant differences were observed between the DPC group and PC group in terms of LOS (MD: - 0.37, 95% CI: - 1.91-1.16, p = 0.63).
Conclusion:
These results point to the efficacy of DPC management in reducing SSI in patients under surgery for GI perforation, and this strategy did not increase the LOS. This systematic review and meta-analysis may contribute to informed decision-making in the management of severely contaminated wounds associated with GI perforation.
More Related Videos
 00:20
A Case Series of Successful Abdominal Closure Utilizing a Novel Technique Combining a Mechanical Closure System with a Biologic Xenograft that Accelerates Wound Healing
Published on: July 4, 2019
 09:00
Application of Straight-needle, Three-tailed, Knot-free, Peritoneal Sutures in Laparoscopic Transabdominal Preperitoneal Hernia Repair
Published on: November 12, 2021
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...