Related Experiment Video
Updated: Jun 11, 2025
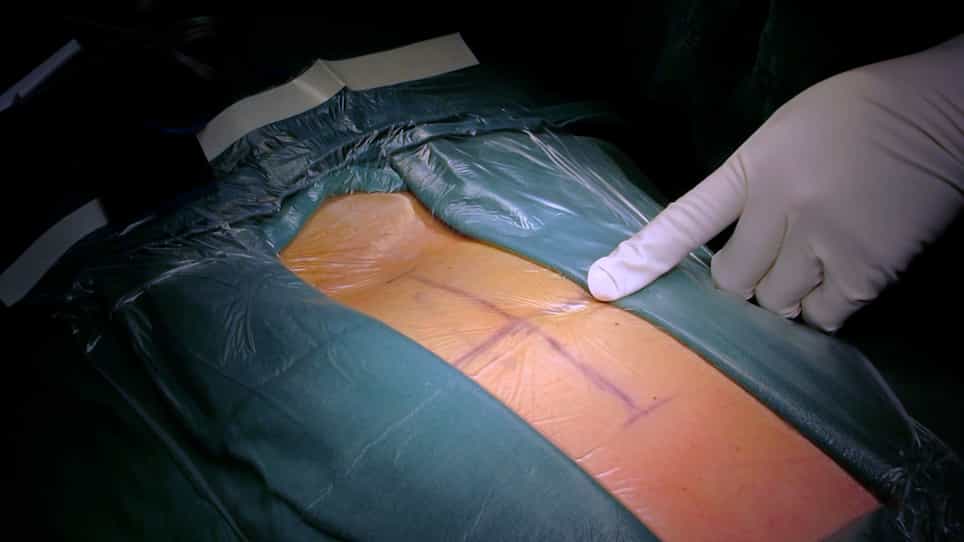

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Percutaneous kyphoplasty combined with pediculoplasty (PKCPP) augments and internally fixates the severe osteoporotic
Changming Xiao1, Haozhong Wang1, Yang Lei1
1Spinal Surgery Department, The Affiliated Traditional Chinese Medicine Hospital, Southwest Medical University, Luzhou, 646000, Sichuan, China.

Abstract:
A retrospective comparative study revealed that percutaneous kyphoplasty combined with pediculoplasty (PKCPP) offers more benefits in terms of pain relief, spinal stability, and complications compared to simple percutaneous kyphoplasty. Moreover, PKCPP can augment and internally fixate the severe osteoporotic vertebral fractures.
Purpose:
Vertebral augmentation (VA) has emerged as a satisfactory and minimally invasive surgical approach for severe osteoporotic vertebral fractures (OVFs). However, treating severe OVFs with advanced collapse, burst morphology with MC injury, posterior wall retropulsion, high degree of osseous fragmentation, pediculo-somatic junction fracture, and large vacuum cleft presents significant challenges. This study aimed to evaluate the effectiveness of percutaneous kyphoplasty combined with pediculoplasty (PKCPP) in reducing refracture, preventing further collapse and bone cement displacement, reconstructing vertebral body (VB) stability, and providing internal fixation of the anterior column (AC), middle column (MC), and the bilateral pedicles.
Methods:
The current study was designed as a retrospective review of clinical and radiologic parameters. From July 2018 to September 2021, ninety-six patients with severe OVFs and without neurological deficit were treated either with simple percutaneous kyphoplasty (simple PKP group, n = 54) or with percutaneous kyphoplasty combined with pediculoplasty (PKCPP group, n = 42). All patients were followed up for at least 1 year, and clinical and radiological outcomes were assessed. Surgery duration and bone cement volume were compared between the two groups, as well as analgesic dosage and hospital stay. Anterior wall height (AWH), posterior wall height (PWH), and Cobb angle (CA) were measured and analyzed before and after surgery.
Results:
The simple PKP group had significantly shorter surgery duration and lower bone cement volume compared to the PKCPP group (P < 0.05). Conversely, the simple PKP group had significantly higher analgesic dosage and longer hospital stay than the PKCPP group (P < 0.05). Both groups showed significant improvements in AWH, PWH, and CA after surgery (P < 0.05). At the final follow-up, the PWH in the simple PKP group was significantly lower than the preoperative measurement (P < 0.05), and the difference in PWH between the two groups was statistically significant (P > 0.05). Moreover, both groups demonstrated a significant reduction in CA after surgery, with the PKCPP group showing a greater reduction compared to the simple PKP group throughout the postoperative period to the final follow-up (P < 0.05). VAS and ODI scores significantly decreased in both groups after surgery (P < 0.05), with no significant difference between the groups at the final follow-up (P > 0.05). However, the PKCPP group achieved better VAS scores than the simple PKP group at postoperative 1 day, 1 month, and 3 months (P < 0.05), and the ODI in the PKCPP group was lower than the simple PKP group at 1 month after surgery (P < 0.05). Furthermore, the overall complication rate in the PKCPP group was significantly lower than that in the simple PKP group (P < 0.05).
Conclusion:
If performed by appropriately trained surgeons, both PKP and PKCPP are safe and effective treatments for patients with severe OVFs. However, PKCPP offers additional benefits in the setting of bothersome fractures, including rapid pain relief, improved spinal stability, satisfactory restoration of vertebral body height, and better correction of kyphotic deformity. These promising results have been tested in a single center but require further confirmation in multiple centers.
More Related Videos


Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care