Related Experiment Video
Updated: May 5, 2026

New Tools to Expand Regulatory T Cells from HIV-1-infected Individuals
Published on: May 30, 2013
Risk of Tuberculosis After Achieving HIV Virological Suppression on Antiretroviral Therapy: A Danish Nationwide
Amrit Kaur Virdee1,2, Fredrikke Christie Knudtzen1,2, Josep M Llibre3
1Department of Infectious Diseases, Odense University Hospital, Odense, Denmark.

Background:
In countries with low tuberculosis burden, the risk of tuberculosis in people with human immunodeficiency virus (HIV; PWH) once HIV virological suppression is achieved is not fully understood.
Methods:
In a nationwide cohort, we included all adult PWH from the Danish HIV Cohort initiating antiretroviral therapy (ART) (1995-2017) without prior tuberculosis disease. We used Kaplan-Meier estimation and Poisson regression to calculate the tuberculosis incidence rate (IR) after 6 months of ART, along with associated risk factors and mortality rates.
Results:
Among 6849 PWH initiating ART (median follow-up, 7.4 years), 84 developed tuberculosis (IR, 1.4/1000 person-years [PY]), 54 of them >6 months after ART initiation (IR, 0.97/1000 PY [95% confidence interval [CI]: 1.17-1.79); 1.95/1000 PY [1.34-2.76] in non-Danish born, 0.36/1000 PY [.21-.62] in Danish born without injection drug use (IDU), and 2.95/1000 PY [1.53-5.66] in Danish born with IDU). Danish-born individuals with suppressed viremia and no IDU or known tuberculosis exposures had the lowest risk (IR, 0.05/1000 PY). In the adjusted analysis, being non-Danish born (adjusted IR ratio, 4.27 [95% CI: 2.36-7.72]), IDU (4.95 [2.55-9.62]), and previous AIDS-defining events (2.05 [1.06-3.94]) raised the tuberculosis risk, while suppressed HIV RNA levels (0.58 [.34-.99]) reduced it. The overall mortality rate for HIV/tuberculosis coinfected after ART was high, at 48.9/1000 PY (95% CI: 30.4-78.7).
Conclusions:
The tuberculosis risk remains elevated in PWH beyond 6 months after ART initiation, especially among migrants, those with IDU, those without suppressed HIV RNA, and those exposed to areas highly endemic for tuberculosis or with social risk determinants of health. Conversely, PWH without these risk factors have a tuberculosis risk similar to the general population and would not require targeted tuberculosis screening strategies.
More Related Videos
 07:21
Processing of Bronchoalveolar Lavage Fluid and Matched Blood for Alveolar Macrophage and CD4+ T-cell Immunophenotyping and HIV Reservoir Assessment
Published on: June 23, 2019
 10:29
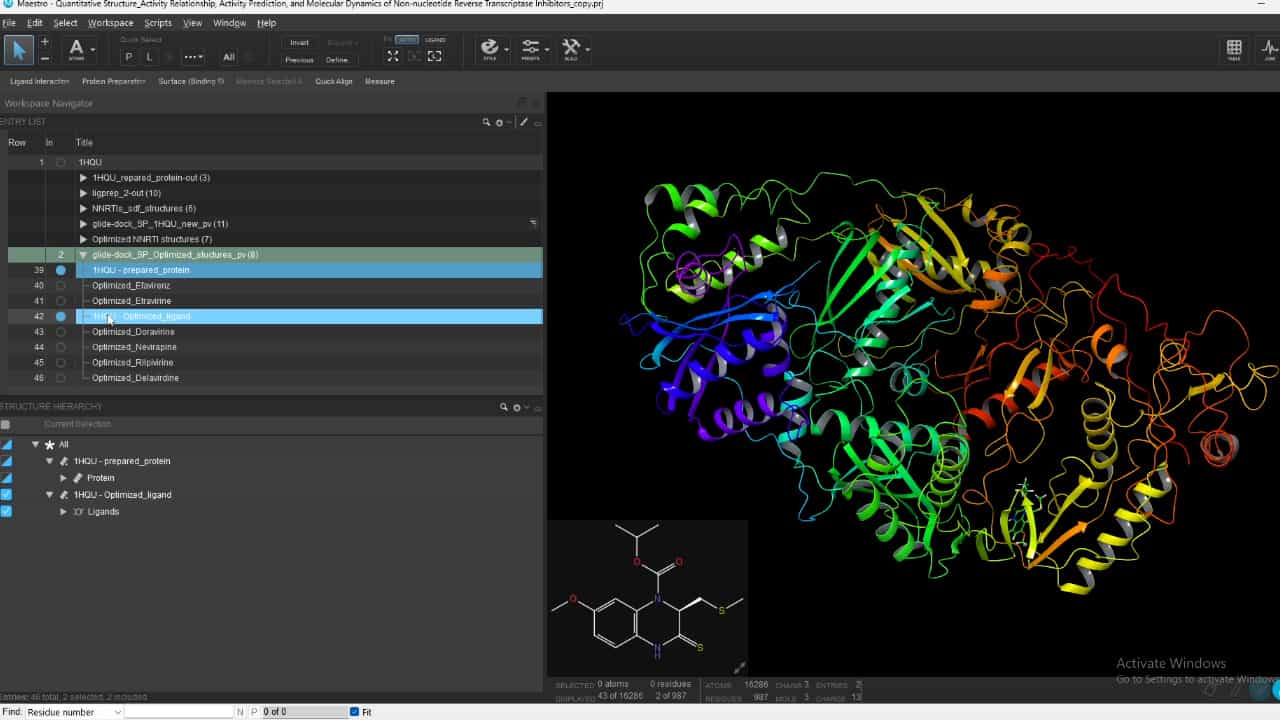
Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Related Concept Videos
 01:10
Retrovirus Life Cycles
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...