Related Experiment Video
Updated: Jun 11, 2025
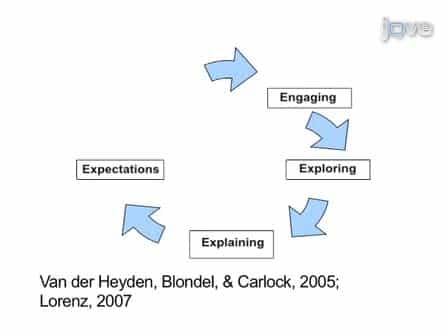
Using Visual and Narrative Methods to Achieve Fair Process in Clinical Care
Published on: February 16, 2011
A model to increase care delivery in nursing homes: The role of Institutional Special Needs Plans
Amanda C Chen1,2, David C Grabowski1
1Department of Health Care Policy, Harvard Medical School, Boston, Massachusetts, USA.

Objective:
To estimate differences in facility-level outcomes between nursing homes which reached Institutional Special Needs Plan (I-SNP) maturity and those which never cared for I-SNP enrollees.
Study Setting And Design:
We used a difference-in-differences design to estimate the effect of I-SNP maturity, defined as having at least 33.75% of Medicare long-stayers in the nursing home enrolled in any I-SNP. Our main outcome was the hospitalization rate in each nursing home-year. Secondary outcomes included the share of residents with medication use, fall, urinary tract infection, catheter insertion, pressure ulcer, physical restraint use, increased need for help with activities of daily living (ADLs), and mortality.
Data Sources And Analytic Sample:
This repeated cross-sectional study used 100% Medicare claims, Minimum Data Set assessments, and publicly available Medicare Advantage (MA) plan characteristics data (2004-2021). We included all MA beneficiaries who resided in US nursing homes which reached I-SNP maturity and those without I-SNP enrollees.
Principal Findings:
We identified 2530 nursing homes which reached I-SNP maturity (treated) and 9830 nursing homes without I-SNP enrollees (untreated). There were some differences observed between these nursing homes, including shares of residents who were White (76.42% vs. 84.84%) and on Medicaid (66.94% vs. 55.45%). These nursing homes were also larger on average (141.76 beds vs. 87.56 beds). From the difference-in-differences model, nursing homes which reached I-SNP maturity experienced declines of 4.1 percentage points (pp) for hospitalizations, 1.0 pp for pressure ulcers, 1.3 pp for urinary tract infections (p < 0.001) alongside increases in the need for help with ADLs, use of antipsychotics, falls, and physical restraints.
Conclusions:
Nursing homes which reached I-SNP maturity experienced fewer hospitalizations and pressure ulcers but a decline in function and increase in other negative outcomes. I-SNPs may be a promising model to improve care for long-stay residents, but more research is needed to understand potential adverse consequences.

Related Concept Videos
 01:29
Planning Nursing Care II
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:21
Planning Nursing Care I
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:19
Restorative Care