Related Experiment Video
Updated: Jun 11, 2025

Long Term Chronic Pseudomonas aeruginosa Airway Infection in Mice
Published on: March 17, 2014
Epidemiology of bronchiectasis
Mattia Nigro1,2, Irena F Laska3, Letizia Traversi4
1Department of Biomedical Sciences, Humanitas University, Milan, Italy mattia.nigro@humanitas.it.

Abstract:
Bronchiectasis is a chronic respiratory disease characterised by permanent enlargement of the airways associated with cough, sputum production and a history of pulmonary exacerbations. In the past few years, incidence and prevalence of bronchiectasis have increased worldwide, possibly due to advances in imaging techniques and disease awareness, leading to increased socioeconomic burden and healthcare costs. Consistently, a mortality increase in bronchiectasis patient cohorts has been demonstrated in certain areas of the globe, with mortality rates of 16-24.8% over 4-5 years of follow-up. However, heterogeneity in epidemiological data is consistent, as reported prevalence in the general population ranges from 52.3 to more than 1000 per 100 000. Methodological flaws in the designs of available studies are likely to underestimate the proportion of people suffering from this condition worldwide and comparisons between different areas of the globe might be unreliable due to different assessment methods or local implementation of the same method in different contexts. Differences in disease severity associated with diverse geographical distribution of aetiologies, comorbidities and microbiology might explain an additional quota of heterogeneity. Finally, limited access to care in certain geographical areas is associated with both underestimation of the disease and increased severity and mortality. The aim of this review is to provide a snapshot of available real-world epidemiological data describing incidence and prevalence of bronchiectasis in the general population. Furthermore, data on mortality, healthcare burden and high-risk populations are provided. Finally, an analysis of the geographical distribution of determinants contributing to differences in bronchiectasis epidemiology is offered.
More Related Videos
 04:03
Author Spotlight: Evaluating the Therapeutic Efficacy of Moving Cupping Along Meridians for Acute Exacerbation of COPD
Published on: September 27, 2024
 06:57
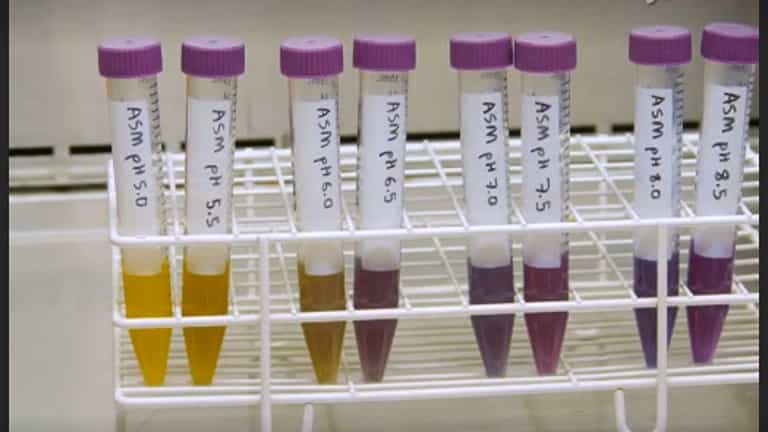
The WinCF Model - An Inexpensive and Tractable Microcosm of a Mucus Plugged Bronchiole to Study the Microbiology of Lung Infections
Published on: May 8, 2017
Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
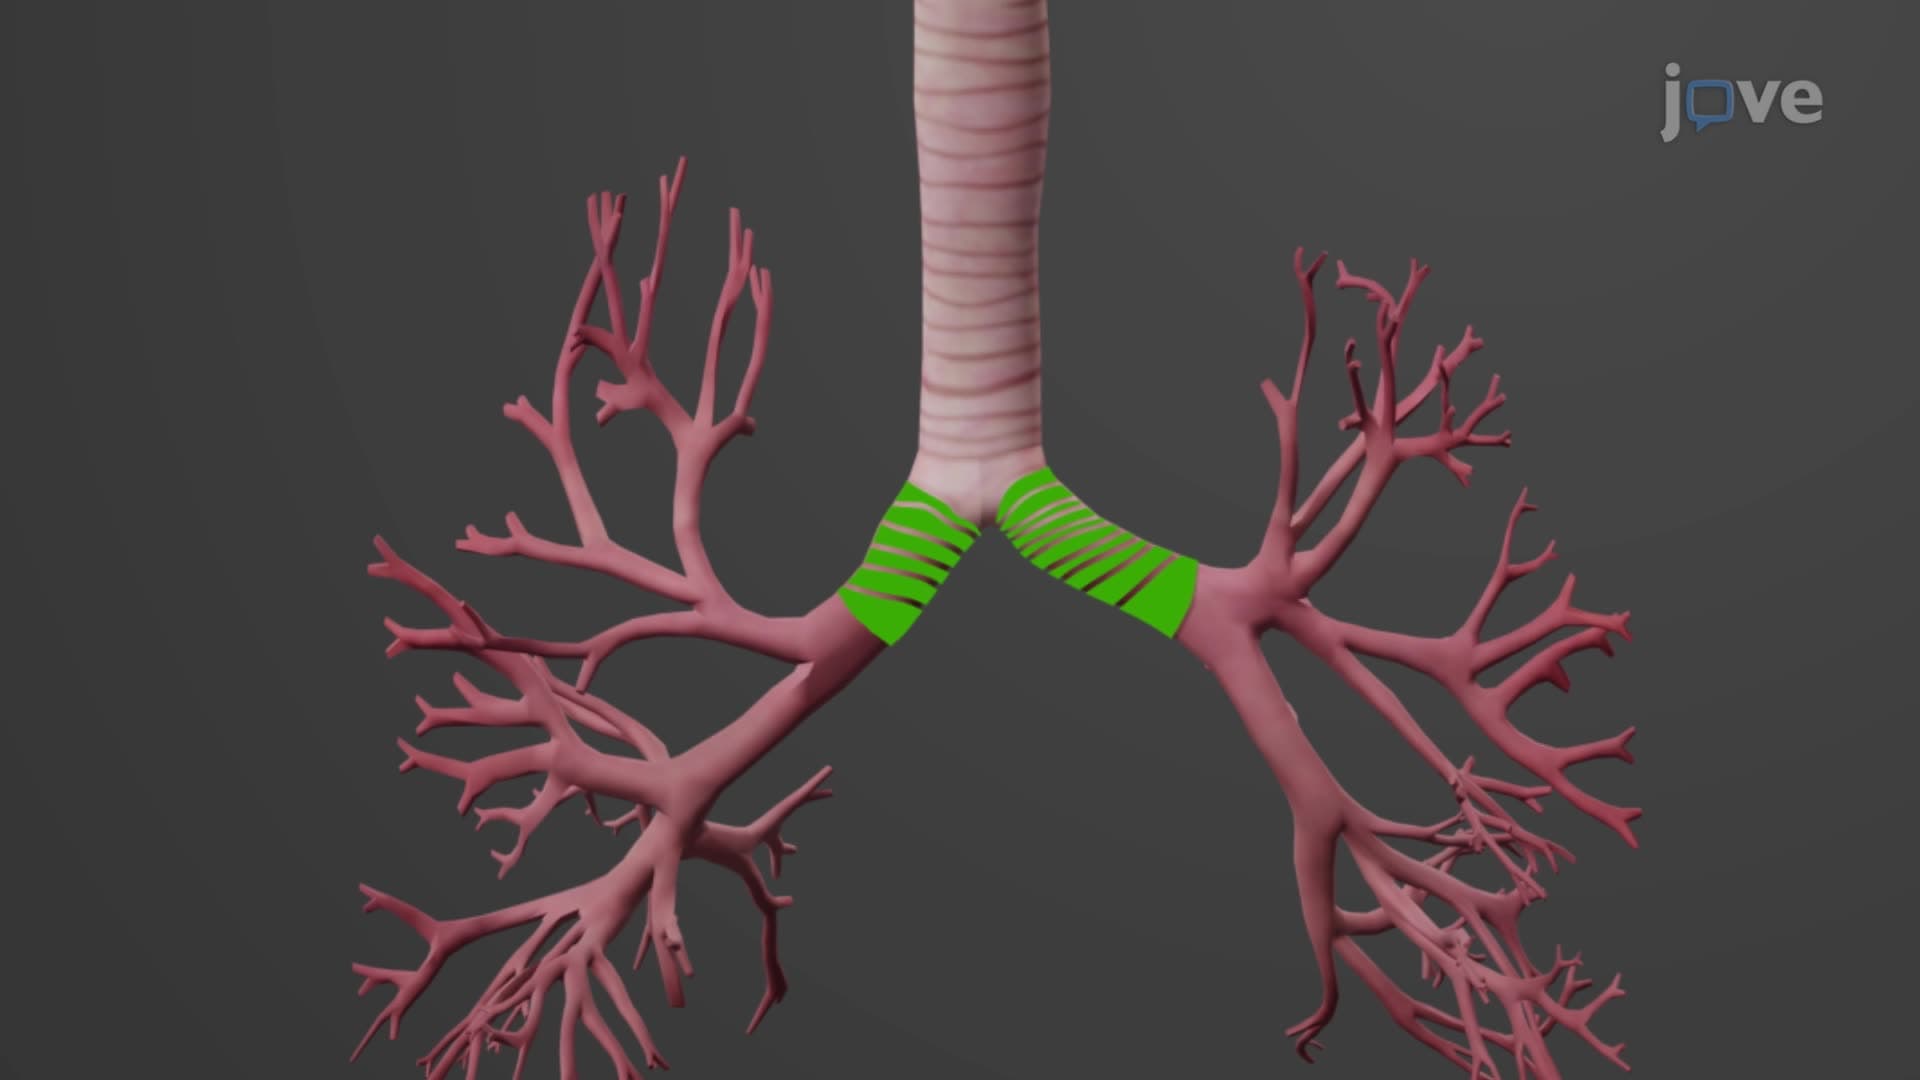
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...