Related Experiment Video
Updated: Jun 10, 2025


Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Blood pressure targets for hypertension in people with chronic renal disease
Juan Erviti1,2,3, Luis Carlos Saiz1,2, Leire Leache1,2
1Unit of Innovation and Organization, Navarre Health Service, Pamplona, Spain.

Insights
Lowering blood pressure targets for individuals with hypertension and chronic kidney disease (CKD) likely makes little to no difference in mortality and cardiovascular events. This meta-analysis found no significant benefits but noted a higher drug requirement for lower targets.
Area of Science:
- Nephrology and Cardiovascular Medicine
- Clinical Trials and Evidence Synthesis
Background:
- Chronic kidney disease (CKD) affects 10% of the global population and is a significant risk factor for cardiovascular disease and mortality.
- Hypertension prevalence in CKD patients ranges from 22% to 80%, with elevated blood pressure being a major risk factor for adverse cardiovascular events.
- The optimal blood pressure target for individuals with both hypertension and CKD remains undetermined.
Purpose of the Study:
- To compare the effects of standard versus lower-than-standard blood pressure targets on mortality and morbidity in hypertensive CKD patients.
- To assess blood pressure reductions, target achievement rates, and medication requirements associated with different blood pressure targets.
Main Methods:
- A systematic review and meta-analysis of six randomized controlled trials (RCTs) involving 7348 participants with hypertension and CKD.
- Interventions compared lower blood pressure targets (≤130/80 mmHg) against standard targets (140-160/90-100 mmHg) with a minimum follow-up of 12 months.
- Critical outcomes included total mortality, cardiovascular events, and progression to end-stage renal disease; GRADE methodology was used to assess evidence certainty.
Main Results:
- Lower blood pressure targets likely result in little to no difference in total mortality (RR 0.90), serious adverse events (RR 1.01), and cardiovascular events (RR 1.00) compared to standard targets.
- Evidence suggests little to no difference in cardiovascular mortality (RR 0.90) and progression to end-stage renal disease (RR 0.94) with lower targets, though certainty is low.
- Participants in lower target groups achieved lower blood pressure but required more antihypertensive medications; a higher proportion in standard groups met their assigned targets.
Conclusions:
- Lowering blood pressure targets in hypertensive CKD patients likely yields minimal to no significant benefits regarding mortality and major adverse events.
- Limitations include open study designs, office-based blood pressure measurement, and limited adverse event data, necessitating further high-quality research.
- Future studies should focus on adverse event reporting, subgroup analyses (e.g., by proteinuria levels), and out-of-office blood pressure monitoring.
Background:
Chronic kidney disease (CKD) is an independent risk factor for cardiovascular disease, development of end-stage renal disease, and all-cause mortality. It affects around 10% of the population worldwide. The prevalence of hypertension in people with CKD ranges from 22% in stage 1 to 80% in stage 4. Elevated arterial blood pressure is one of the major independent risk factors for adverse cardiovascular events. Thereby, reducing blood pressure to below standard targets may be beneficial but could also increase the risk of adverse events. The optimal blood pressure target in people with hypertension and CKD remains unknown.
Objectives:
Primary: to compare the effects of standard and lower-than-standard blood pressure targets for hypertension in people with chronic kidney disease on mortality and morbidity outcomes. Secondary: to assess the magnitude of reductions in systolic and diastolic blood pressure, the proportion of participants reaching blood pressure targets, and the number of drugs necessary to achieve the assigned target.
Search Methods:
We used standard, extensive Cochrane search methods. We searched the Cochrane Hypertension Specialized Register, CENTRAL, MEDLINE, Embase, one other database, and two trial registers up to 8 February 2023. We also contacted authors of relevant papers regarding further published and unpublished work. We applied no language restrictions.
Selection Criteria:
We included randomized controlled trials (RCTs) in people with hypertension and CKD that provided at least twelve months' follow-up. Eligible interventions compared lower targets for systolic/diastolic blood pressure (130/80 mmHg or lower) to standard targets for blood pressure (140 to 160/90 to 100 mmHg or lower). Participants were adults with CKD and elevated blood pressure documented in a standard way on at least two occasions, or already receiving treatment for elevated blood pressure.
Data Collection And Analysis:
We used standard Cochrane methods. Our critical outcomes were: total mortality, total serious adverse events, total cardiovascular events, cardiovascular mortality, and progression to end-stage renal disease. Important outcomes were: participant withdrawals due to adverse effects, and number of participants with a doubling of serum creatinine level or at least a 50% reduction in the glomerular filtration rate (GFR) at the end of the study. We used GRADE to assess the certainty of the evidence for the critical outcomes. This review received no funding.
Main Results:
We included six RCTs that contributed data for meta-analysis, involving 7348 participants overall (range 840 to 4733 people per study). The mean follow-up was 3.6 years (range 1.0 to 8.0 years). Three studies were publicly funded, two were privately funded, and one had both public and private funding. All RCTs provided individual participant data. None of the included studies blinded participants or clinicians because of the need to titrate antihypertensive drugs to reach a specific blood pressure target. However, an independent committee blinded to group allocation assessed clinical events in all studies. Critical outcomes. Compared with standard blood pressure targets, lower targets likely result in little to no difference in total mortality (risk ratio (RR) 0.90, 95% confidence interval (CI) 0.76 to 1.06; 6 studies, 7348 participants), total serious adverse events (RR 1.01, 95% CI 0.94 to 1.08; 6 studies, 7348 participants), and total cardiovascular events (RR 1.00, 95% CI 0.87 to 1.15; 5 studies, 6508 participants), all with moderate-certainty evidence. Compared with standard blood pressure targets, lower targets may result in little to no difference in cardiovascular mortality (RR 0.90, 95% CI 0.70 to 1.16; 6 studies, 7348 participants) and progression to end-stage renal disease (RR 0.94, 95% CI 0.80 to 1.11; 4 studies, 4788 participants), both with low-certainty evidence. Important outcomes. We found little to no differences in: participant withdrawals due to adverse effects; and the number of participants with a doubling of serum creatinine level, or at least a 50% reduction in GFR at the end of the study. Exploratory outcomes. Compared to the standard blood pressure target groups, participants in the lower target groups achieved lower systolic and diastolic blood pressure values after one year, and required a higher number of antihypertensive drugs at the end of the studies. A higher proportion of participants in the standard blood pressure target groups achieved the targets they were assigned than did participants in the intensive target groups.
Authors' Conclusions:
Compared to a standard blood pressure target, lower blood pressure targets probably result in little to no difference in total mortality, total serious adverse events, and total cardiovascular events, and may result in little to no difference in total cardiovascular mortality or in the progression to end-stage renal disease in people with hypertension and CKD. However, the evidence underpinning these conclusions has several limitations. All studies were open design, blood pressure measurement was performed at a medical office, and there was scant information about adverse events. Future research should include high-quality adverse event data, report results for people with different levels of proteinuria, and consider out-of-office blood pressure monitoring. Several studies are ongoing, and may provide new evidence for this topic in the near future.


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:28
Hypertension I: Introduction
 01:25
Chronic Kidney Disease I: Introduction
 01:30
Blood Pressure
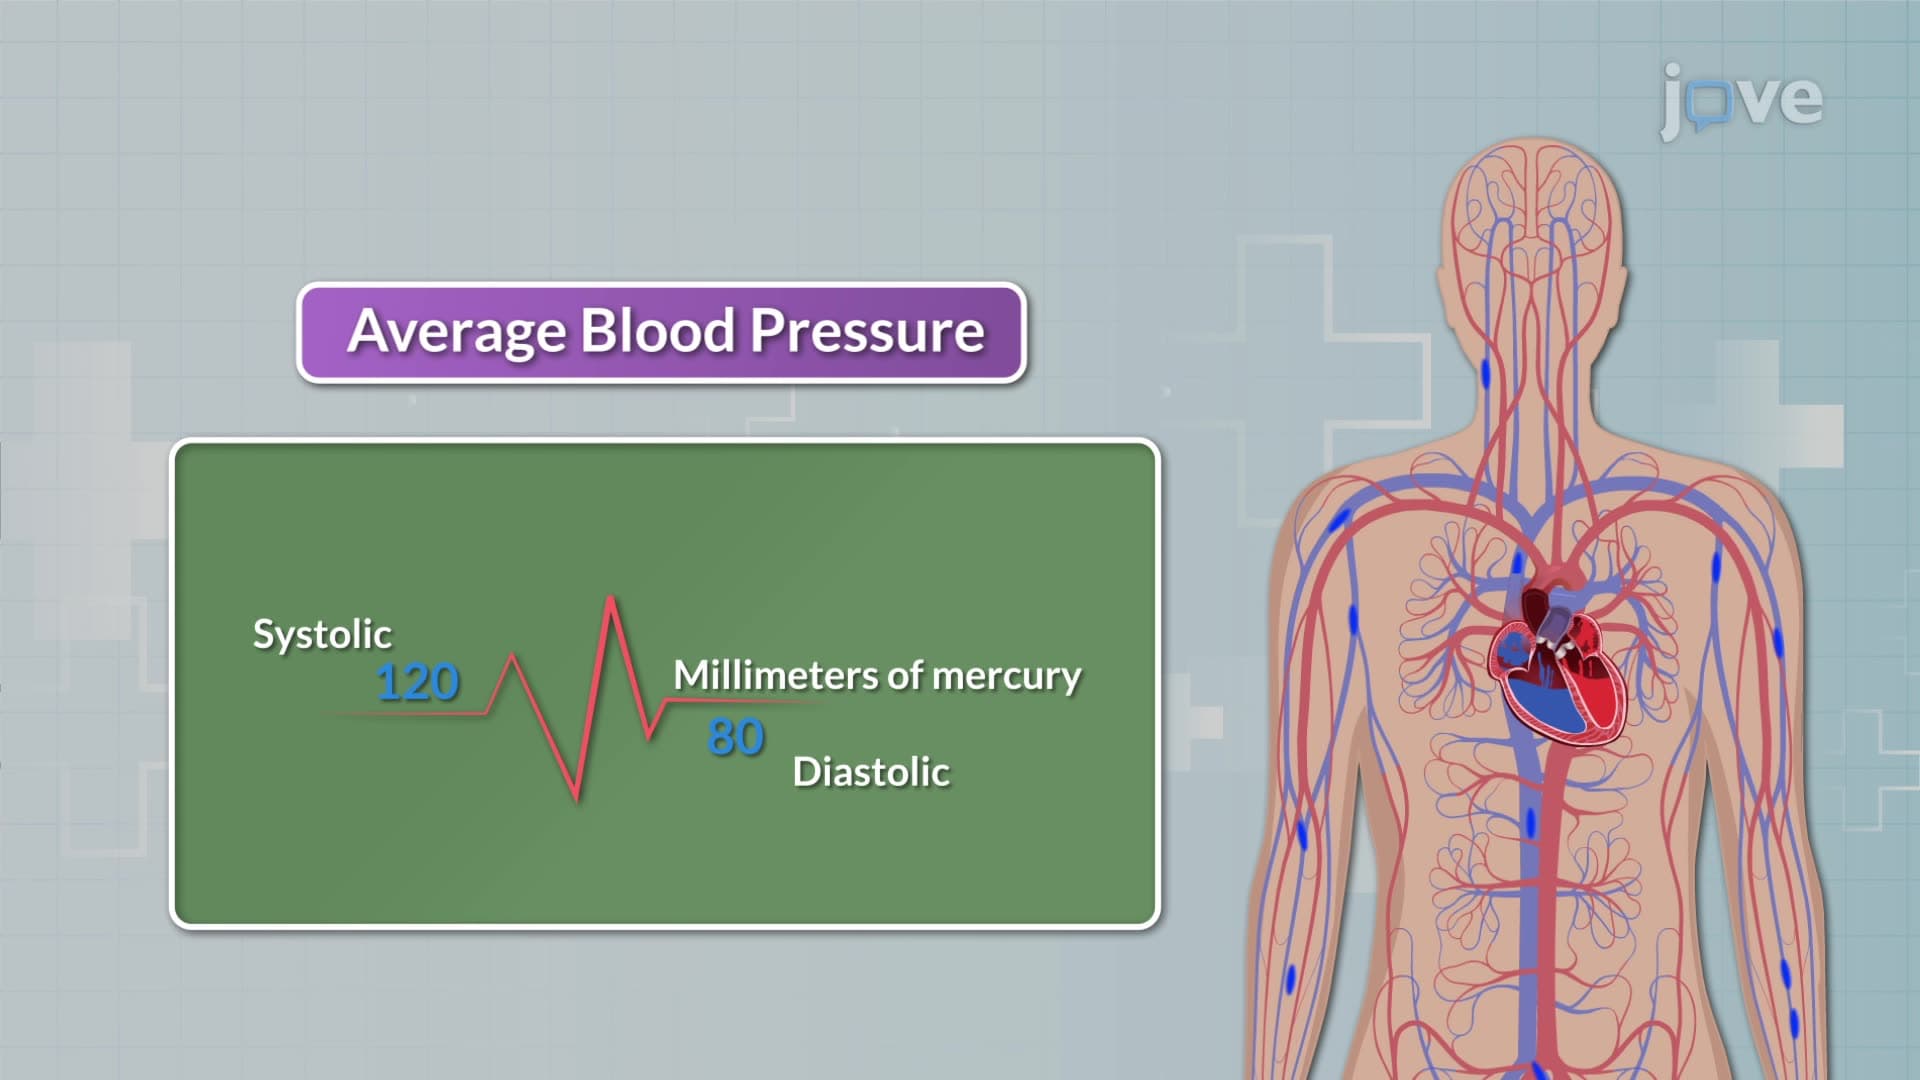
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...