Related Experiment Video
Updated: Jun 10, 2025
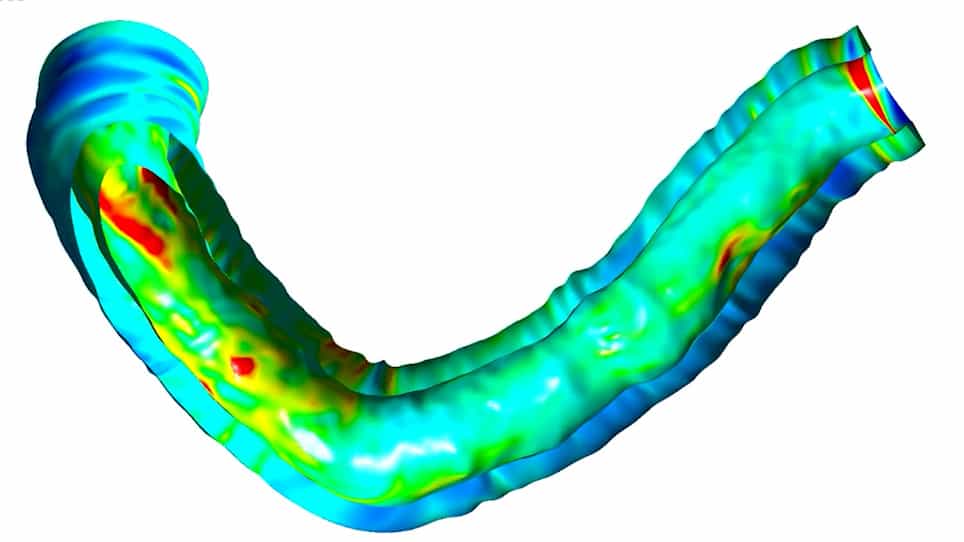
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Spatial patterns of high-risk biomechanical metrics in plaques with abnormal vs. normal physiological flow indices
Diaa Hakim1, Mona Ahmed2, Ahmet U Coskun3
1Cardiovascular Division, Brigham & Women's Hospital/Harvard Medical School, Boston, MA, USA.

Insights
The Instantaneous Wave-free Ratio (iFR) does not reliably identify high-risk coronary plaques. High-risk endothelial shear stress metrics are present in plaques regardless of iFR values, suggesting iFR may miss many plaques prone to causing major adverse cardiac events (MACE).
Area of Science:
- Cardiovascular research
- Biomedical engineering
- Medical imaging
Background:
- Percutaneous coronary intervention (PCI) is indicated for plaques with low physiological flow reserve.
- Recent trials show PCI does not reduce major adverse cardiac events (MACE) for ischemia-producing lesions.
- Low endothelial shear stress (ESS) or high ESS gradient (ESSG) are linked to MACE.
Purpose of the Study:
- To investigate the presence of high-risk ESS metrics in obstructive coronary plaques.
- To compare ESS metrics in plaques with high-risk (<0.80), borderline-risk (0.80-0.89), and normal (>0.89) Instantaneous Wave-free Ratio (iFR).
Main Methods:
- 50 coronary arteries with variable iFR values were analyzed using coronary angiography and optical coherence tomography (OCT).
- 3D reconstruction and computational fluid dynamics were used to calculate ESS and ESSG.
- The cohort was stratified into three iFR groups for comparison of high-risk ESS metrics and their spatial distribution.
Main Results:
- High-risk ESS features (Minimal ESS, Maximum ESSG) showed similar distribution and absolute values across all three iFR subgroups.
- Minimal ESS values were 0.5 ± 0.3 Pa, 0.4 ± 0.2 Pa, and 0.4 ± 0.2 Pa (p=0.60).
- Maximum ESSG values were 13.7 ± 9.4 Pa/mm, 10.4 ± 10.6 Pa/mm, and 10.0 ± 7.8 Pa/mm (p=0.30).
- ESS metrics extended up to ≥18 mm from the plaque minimal luminal area (MLA).
Conclusions:
- High-risk ESS metrics are present in plaques with both normal and abnormal iFR values.
- The spatial location of these metrics relative to the MLA is consistent across iFR groups.
- Relying solely on iFR to identify plaques likely to cause MACE may lead to overlooking a significant number of high-risk plaques.
Background:
Plaques associated with abnormally low physiological flow reserve indices are appropriate for percutaneous coronary intervention (PCI). However, recent trials demonstrate that PCI of ischemia-producing lesions does not reduce major adverse cardiac events (MACE). Low endothelial shear stress (ESS) or high ESS gradient (ESSG) are associated with MACE wherever they occur along the plaque. This study aims to determine the presence of high-risk ESS metrics in obstructive coronary plaques with high-risk (<0.80) vs. borderline-risk (0.80-0.89) vs. normal Instantaneous Wave-free Ratio (iFR) (>0.89).
Methods:
We included 50 coronary arteries (50 patients) with variable iFR values who underwent coronary angiography and optical coherence tomography (OCT), followed by 3D reconstruction and computational fluid dynamics calculations of ESS/ESSG. The cohort was divided into 3 groups: iFR < 0.80, iFR 0.80-0.89, and iFR > 0.89. Spatial distribution of ESS metrics was reported along the course of each plaque, and high-risk ESS metrics and their location were compared among the 3 iFR subgroups.
Results:
High-risk ESS features (Minimal ESS, Maximum ESSG) were similarly distributed along the course of the atherosclerotic plaque in the three iFR subgroups, both in absolute value and in location: Min ESS: 0.5 ± 0.3 vs. 0.4 ± 0.2 vs. 0.4 ± 0.2 Pa respectively (p = 0.60); Max ESSG any direction: 13.7 ± 9.4 vs. 10.4 ± 10.6 vs. 10.0 ± 7.8 Pa/mm respectively (p = 0.30). ESS metrics were spatially located up to ≥18 mm from the plaque minimal luminal area (MLA) in both directions.
Conclusion:
High-risk ESS metrics are similarly observed in plaques with normal or abnormal iFR, both in absolute value and spatial location in reference to the MLA. Utilizing iFR to identify plaques likely to cause MACE would miss the majority of plaques mechanistically at high-risk to destabilize and cause future adverse cardiac events.


