Related Experiment Video
Updated: Jun 10, 2025
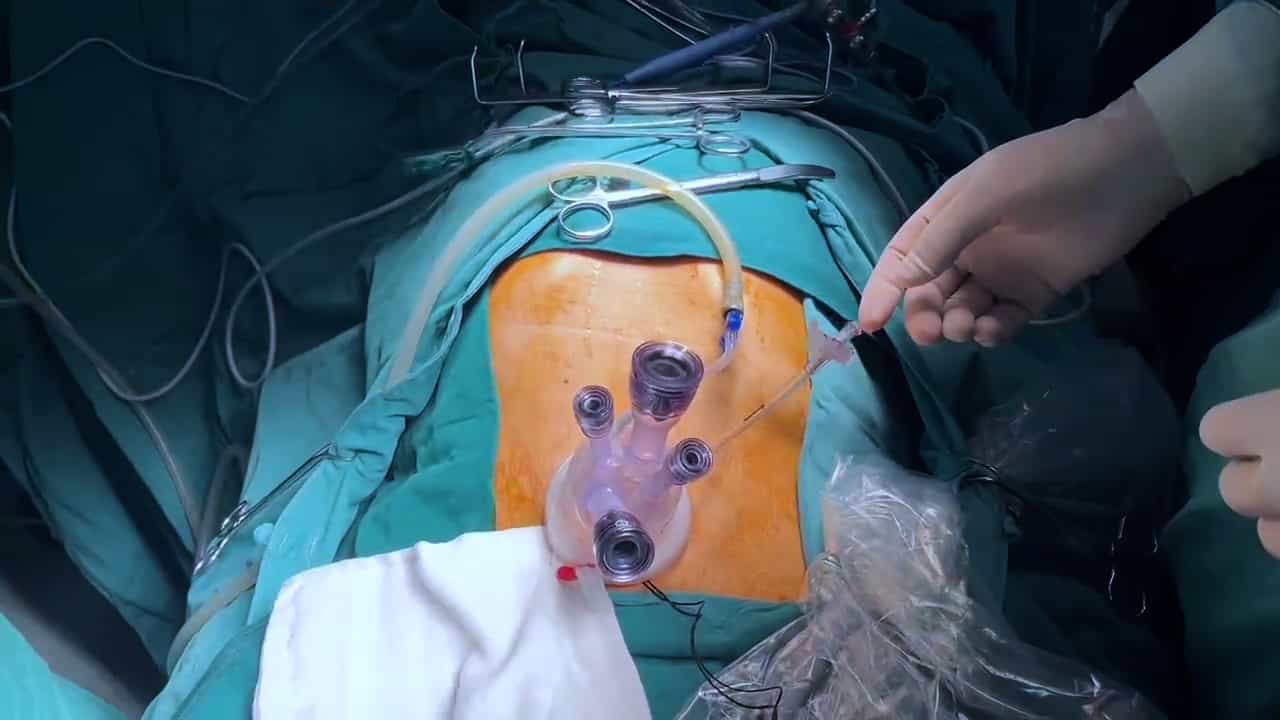
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
[Efficacy and feasibility of tunnel esophagogastrostomy to perform proximal gastrectomy]
1Department of General Surgery, Jiangsu Cancer Hospital, Jiangsu Institute of Cancer Research, the Affiliated Cancer Hospital of Nanjing Medical University, Nanjing 210009, China.

Abstract:
Objective: To analyze the efficacy and feasibility of performing a new surgical procedure, tunnel esophagogastrostomy, to perform proximal gastrectomy. Methods: The study cohort comprised 10 consecutive patients who had undergone esophagogastrostomy by the tunnel technique in Jiangsu Cancer Hospital between October 2019 and July 2022. All patients were male. Their average age was (64.2±8.1) years and body mass index (25.5±3.2) kg/m2. Nine had upper gastric body adenocarcinoma, the remaining one having signet ring cell carcinoma. TNM staging of the tumors showed that seven were Stage IA, one Stage IB, one Stage IIA, and one Stage IIIA. Briefly, tunnel esophagogastrostomy is performed as follows: After performing a proximal gastrectomy, a rectangular seromuscular flap (3.0 cm × 3.5 cm) is created. The posterior esophageal wall is sutured to the gastric wall at the orad end of the seromuscular flap 5 cm from the stump with three to four stitches. Next, the stump of the esophagus is opened, the posterior esophageal wall is sutured to the gastric mucosa and submucosa, and the anterior esophageal wall is sutured to the full layer of the stomach. Finally, the caudad end of the seromuscular flap is closed. Data on surgical safety, postoperative morbidity, and postoperative reflux esophagitis were analyzed. All enrolled patients completed endoscopic follow-up 1 year and 2 years after surgery. Results: All procedures were completed. They comprised four cases of laparoscopic assisted surgery, four of DaVinci robotic surgery, and two of open surgery. The mean operation time was 212.7±33.2 mins, mean anastomosis time (51.6±5.3) minutes, mean tunnel preparation time (20.0±3.5) minutes, and mean operative blood loss (90.0±51.6) mL. The time to first postoperative passage of flatus was (64.8±11.5) hours. The mean hospital stay after surgery was (9.2±1.7) days. There were no postoperative complications above Clavien-Dindo Grade II. The mean preoperative Reflux Disease Questionnaire score was (3.3± 0.4) before the surgery, (3.8±1.0) 1 month postoperatively, and (3.3±0.4) 12 months postoperatively. All patients underwent endoscopic follow-up; no anastomotic stenoses were found. However, one patient had Grade A reflux esophagitis 1 year after surgery and another Grade B reflux esophagitis 2 years after surgery. Conclusion: Esophagogastrostomy by the tunnel technique is a safe and feasible means of performing proximal gastrectomy.

Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...