Accuracy of Real-Time Data Provided by Mechanical Insufflation-Exsufflation Devices
Related Experiment Video
Updated: Jun 9, 2025
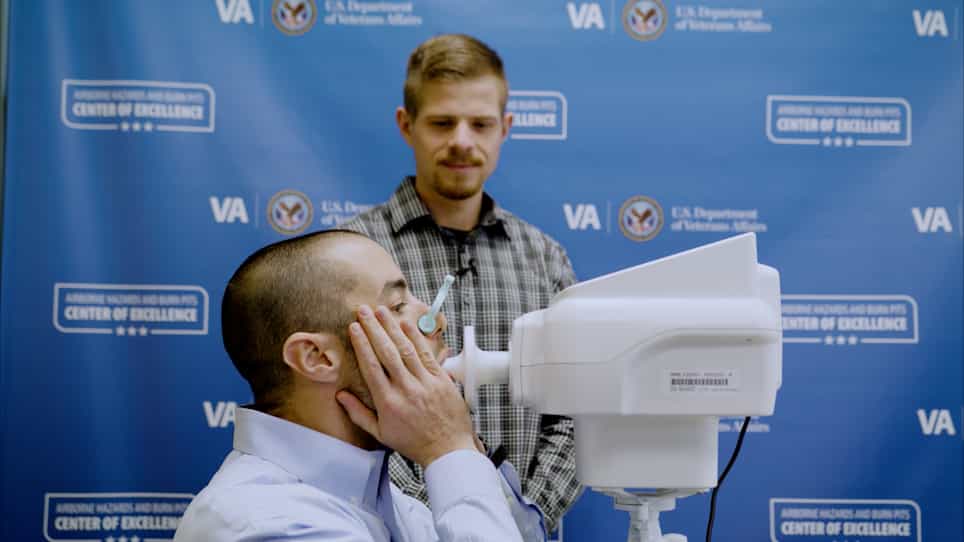
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Roberto Martínez-Alejos1,2,3, Emeline Fresnel1, Alice Vuillermoz4
1Drs. Martínez-Alejos, Fresnel, and Lebret are affiliated with the Kernel Biomedical. Rouen, France.

Abstract:
Background: Mechanical insufflation-exsufflation (MI-E) is crucial to assist patients with impaired cough, especially those with neuromuscular diseases. Despite recent advancements that enable real-time display of peak expiratory flow (PEF) and inspiratory volume, accurately monitoring these parameters with MI-E devices during treatment can still present challenges. Methods: A bench study that used a mechanical lung connected to 3 MI-E devices (EOVE-70; E-70 and Comfort Cough II) was conducted to evaluate PEF and inspiratory volume monitoring accuracy. Two clinical conditions were tested, low and normal compliance, with 6 different MI-E settings tested: +20/-20, +30/-30, +40/-40, +40/-50, +40/-60, and +40/-70 cm H2O. PEF (L/min) and inspiratory volume (mL) displayed on the screen were recorded cycle by cycle, while a pneumotachograph connected to the mechanical lung was used to measure the actual PEF and inspiratory volume for data comparison. Flow bias was assessed by calculating the difference (PEF - peak inspiratory flow) and ratio (PEF to peak inspiratory flow) between flows. Results: All devices systematically underestimated PEF, with device A showing the smallest estimation error (-7.4 [-10.1; -6] %). Devices B and C exhibited larger errors (-26.5 [-29.2; -25.6] and (-29.9 [-30.7; -28.7] %, respectively). All the devices underestimated inspiratory volume, with device B showing the smallest estimation error (-15.1 [-21.2; -12.3] %). Device A exhibited a significantly larger error (-26.9 [-30.3; -24.8] %). The error from device C (-17.7 [-34.5; -13.8] %) was not statistically different from device B. Device type, high pressure settings (>+40/-40 cm H2O), and a lung model compliance of 60 mL/cm H2O were the main contributors to error in estimating PEF and inspiratory volume. Finally, we observed differences of PEF-to-peak inspiratory flow ratio and PEF minus peak inspiratory flow differences achieved. Conclusions: Our study highlighted consistent underestimation of PEF and inspiratory volume across MI-E devices. Improving device monitoring is essential for guiding MI-E therapy and ensuring patient safety.
More Related Videos


Related Concept Videos
 01:30
Equipments Used To Measure Blood Pressure
This invasive approach involves cannulating a peripheral artery. During each cardiac contraction, pressure generates mechanical motion within the catheter, transmitted through rigid, fluid-filled tubing to a transducer. This transducer converts mechanical motion into electrical signals displayed as waveforms on a monitor. An automatic flushing system prevents blood backflow. Due to the potential risk of unexpected arterial blood loss, this method is primarily used in intensive...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:25
Errors occurring during blood pressure monitoring
Several factors...