Related Experiment Video
Updated: Jun 8, 2025
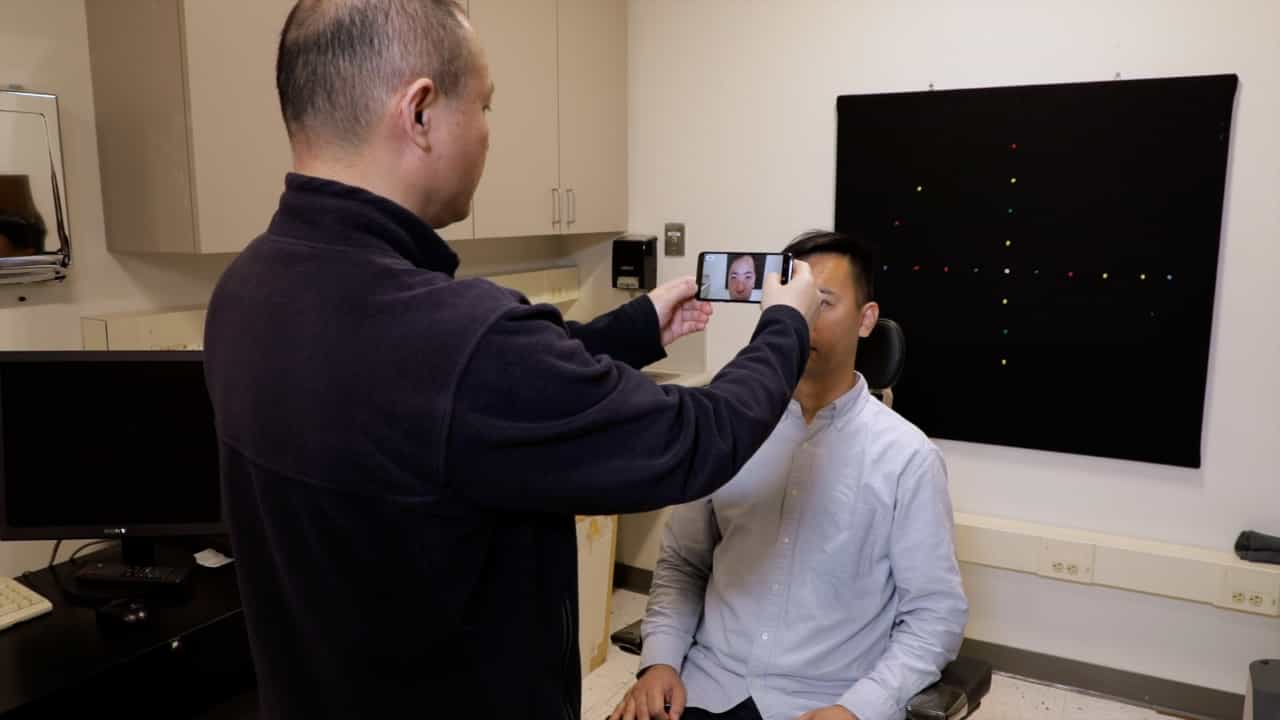

Subjective Refraction Test Using a Smartphone for Vision Screening
Published on: October 18, 2024
Cost-effectiveness and cost-utility of community-based blinding fundus diseases screening with artificial
Senlin Lin1, Yingyan Ma2, Liping Li3
1Shanghai Eye Diseases Prevention &Treatment Center/ Shanghai Eye Hospital, School of Medicine, Tongji University, No. 1440, Hongqiao Road, Shanghai, China; National Clinical Research Center for Eye Diseases, No. 1440, Hongqiao Road, Shanghai, China; Shanghai Engineering Research Center of Precise Diagnosis and Treatment of Eye Diseases, No. 1440, Hongqiao Road, Shanghai, China.

Background:
With application of artificial intelligence (AI) in the disease screening, process reengineering occurred simultaneously. Whether process reengineering deserves special emphasis in AI implementation in the community-based blinding fundus diseases screening is not clear.
Method:
Cost-effectiveness and cost-utility analyses were performed employing decision-analytic Markov models. A hypothetical cohort of community residents was followed in the model over a period of 30 1-year Markov cycles, starting from the age of 60. The simulated cohort was based on work data of the Shanghai Digital Eye Disease Screening program (SDEDS). Three scenarios were compared: centralized screening with manual grading-based telemedicine systems (Scenario 1), centralized screening with an AI-assisted screening system (Scenario 2), and process reengineered screening with an AI-assisted screening system (Scenario 3). The main outcomes were incremental cost-effectiveness ratio (ICER) and incremental cost-utility ratio (ICUR).
Results:
Compared with Scenario 1, Scenario 2 results in incremental 187.03 years of blindness avoided and incremental 106.78 QALYs at an additional cost of $ 490010.62 per 10,000 people screened, with an ICER of $2619.98 per year of blindness avoided and an ICUR of $4589.13 per QALY. Compared with Scenario 1, Scenario 3 results in incremental 187.03 years of blindness avoided and incremental 106.78 QALYs at an additional cost of $242313.23 per 10,000 people screened, with an ICER of $1295.60 per year of blindness avoided and an ICUR of $2269.35 per QALY. Although Scenario 2 and 3 could be considered cost-effective, the screening cost of Scenario 3 was 27.6 % and the total cost was 1.1 % lower, with the same expected effectiveness and utility. The probabilistic sensitivity analyses show that Scenario 3 dominated 69.1 % and 70.3 % of simulations under one and three times the local GDP per capita thresholds.
Conclusions:
AI can improve the cost-effectiveness and cost-utility of screenings, especially when process reengineering is performed. Therefore, process reengineering is strongly recommended when AI is implemented.