Immune-related toxic epidermal necrolysis affecting trachea mucosal epithelium: a case report and literature review
Related Experiment Video
Updated: Jun 8, 2025
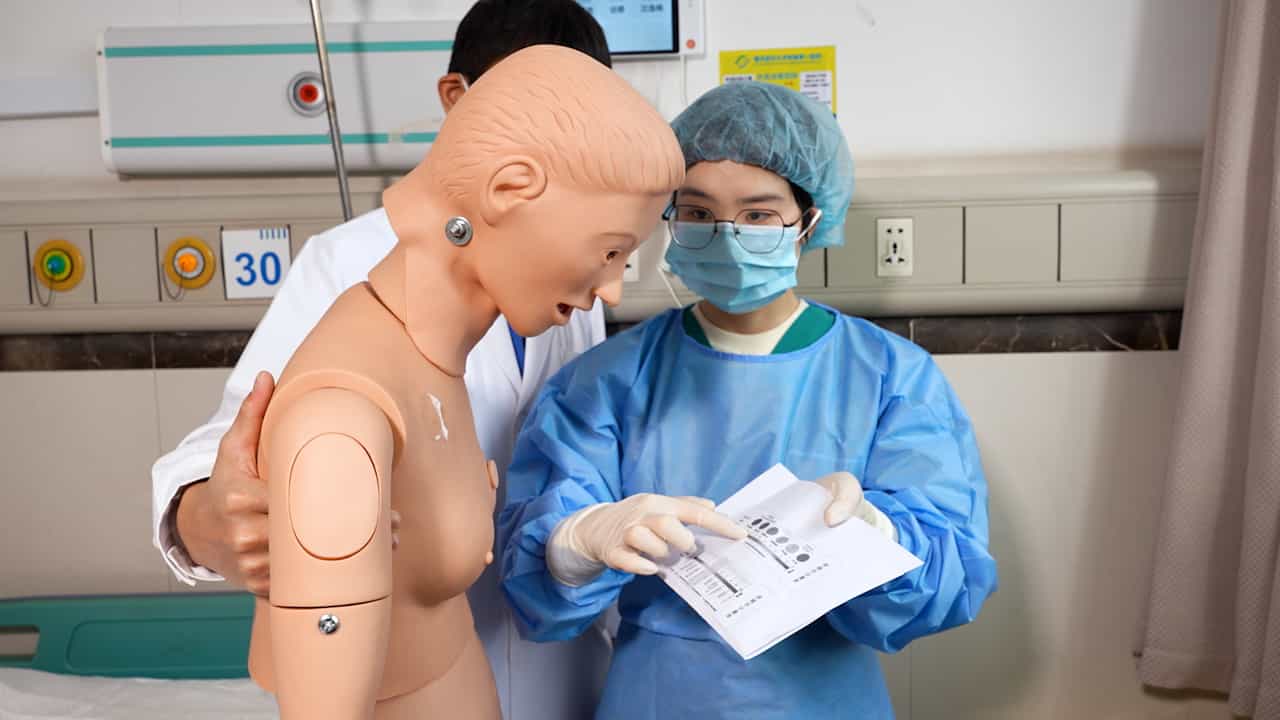
A Standardized Procedure of Dressing Management for Toxic Epidermal Necrolysis
Published on: March 14, 2025
Mingbo Zhang1, Yang Fu2, Yuxiao Song1
1Cancer Center, Renmin Hospital of Wuhan University, Wuhan, China.

Background:
Monoclonal antibodies against programmed cell death protein-1 (PD-1)/programmed death-ligand-1 (PD-L1) have emerged as critical tools in cancer treatment. However, concerns regarding their potential cutaneous and mucosal toxicity, along with severe complications, have drawn clinical attention. Further research is warranted to investigate the adverse reactions and treatment strategies associated with PD-1 monoclonal antibodies.
Methods:
We present a detailed case report of a laryngeal cancer patient who developed toxic epidermal necrolysis (TEN) after treatment with PD-1 monoclonal antibody. We analyzed the etiology, diagnosis, and treatment approaches by integrating clinical manifestations, pathological examinations, and literature research.
Results:
After PD-1 monoclonal antibody therapy, the patient exhibited systemic rash, bullae, and epidermal detachment, which subsequently involved the tracheal and bronchial mucosa, resulting in dyspnea. The patient recovered after treatments with steroids, macrolides, immunoglobulins, and etanercept, along with repeated removal of scabs via bronchoscopy. Literature reviewing suggests a potential association between PD-1 monoclonal antibodies and the pathogenesis of Steven Johnson's Syndrome (SJS) and Toxic epidermal necrolysis (TEN), possibly due to immune dysregulation. Treatment consists of immediate discontinuation of suspicious drugs, essential supportive therapy, and systemic corticosteroid administration, with the addition of immunosuppressants and/or immunoglobulins needed.
Conclusion:
The mucocutaneous toxicity induced by PD-1 monoclonal antibodies is not limited to the surface of the skin but also in deep mucosal layers, potentially leading to life-threatening complications. Therefore, when using PD-1 monoclonal antibodies, clinicians should closely monitor adverse events and apply appropriate treatments as soon as possible to prevent severe complications.
Insights
Programmed cell death protein-1 (PD-1) antibody therapy can cause severe mucocutaneous toxicity, including toxic epidermal necrolysis (TEN). Early recognition and prompt treatment are crucial for managing these life-threatening immune-related adverse events.
Area of Science:
- Oncology
- Immunology
- Dermatology
Background:
- Programmed cell death protein-1 (PD-1)/programmed death-ligand-1 (PD-L1) inhibitors are vital cancer immunotherapies.
- These therapies carry risks of cutaneous and mucosal toxicities, necessitating further investigation.
Observation:
- A laryngeal cancer patient developed toxic epidermal necrolysis (TEN) following PD-1 inhibitor treatment.
- The patient presented with systemic rash, bullae, epidermal detachment, and respiratory distress due to mucosal involvement.
Findings:
- Treatment involved steroids, macrolides, immunoglobulins, etanercept, and bronchoscopic interventions.
- Literature suggests PD-1 inhibitors may trigger Steven Johnson's Syndrome (SJS) and TEN via immune dysregulation.
Implications:
- PD-1 inhibitor-induced mucocutaneous toxicity can be severe and life-threatening.
- Close monitoring for adverse events and prompt, appropriate treatment are essential for patient safety.

Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 02:06
Allergic Reactions