Related Experiment Video
Updated: Jun 8, 2025


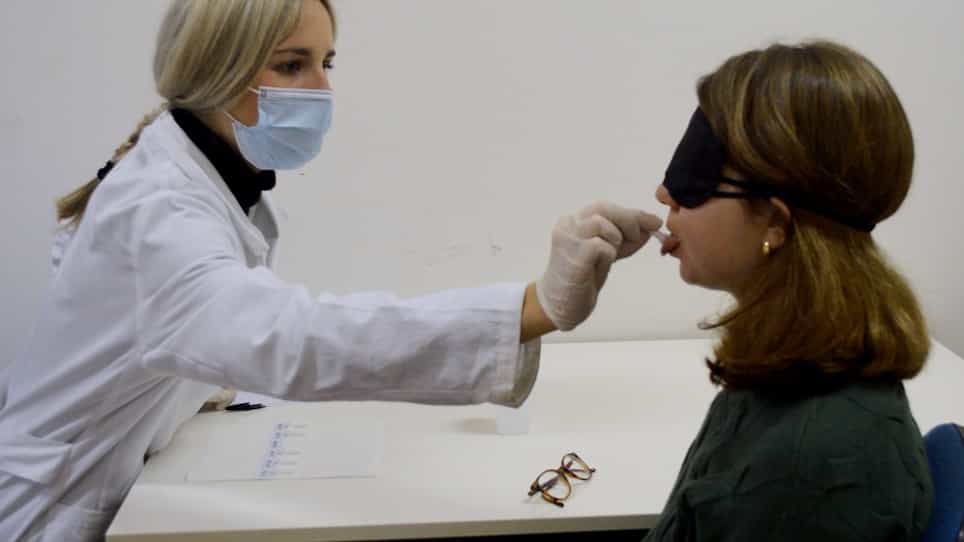
Assessment of Midline Lingual Point-Pressure Somatosensation Using Von Frey Hair Monofilaments
Published on: February 21, 2020
Effect of Lingual Nerve Block and Localised Somatosensory Abnormalities in Patients With Burning Mouth Syndrome-A
Guangju Yang1, Jianqiu Jin2,3, Kelun Wang4,5
1Department of Prosthodontics and Center for Oral Functional Diagnosis, Treatment and Research, Peking University School and Hospital of Stomatology, National Engineering Laboratory for Digital and Material Technology of Stomatology, Key Laboratory of Digital Stomatology, Beijing, China.

Aims:
To investigate the effect of a lingual nerve block on spontaneous pain in patients with burning mouth syndrome (BMS) and to estimate associated somatosensory abnormalities by quantitative sensory testing (QST).
Protocol And Methods:
A standardised QST battery including cold detection threshold (CDT), warmth detection threshold (WDT), thermal sensory limen (TSL), paradoxical heat sensation (PHS), cold pain threshold (CPT), heat pain threshold (HPT), mechanical pain threshold (MPT), wind-up ratio (WUR) and pressure pain threshold (PPT) was performed at the oral mucosa of the most painful site and intraoral control site in 20 BMS patients, and at the tongue and cheek mucosa in 22 age- and gender-matched healthy controls. The effect of a lingual nerve block on spontaneous burning pain reported by the BMS patients on a 0-10 cm visual analogue scale (VAS) was investigated in a randomised double-blind crossover design using (1 mL) lidocaine (lido) or saline (sal) with an interval of 1 week. The BMS patients were grouped into 'central' and 'peripheral' mechanisms based on the effect of the lingual nerve injections. For each BMS patient, Z-scores and Loss/Gain scores were computed. Differences among groups and sites were analysed using a two-way ANOVA. Differences within group were assessed by paired t-test.
Results:
The 20 BMS patients were characterised on the basis of VAS changes (ΔLido-ΔSal) as a peripheral BMS subgroup (n = 9) with pain relief more than 1 cm on the VAS and a central BMS subgroup (n = 11) with pain relief less than 1 cm. BMS patients (n = 20) had lower sensitivity to thermal stimuli (i.e., CDT, WDT, TSL, CPT, HPT and PPT) and higher sensitivity to mechanical stimuli (i.e., PPT) compared with controls (p ≤ 0.007). Based on Loss/Gain coding, L1G0 (loss of thermal somatosensory function with no somatosensory gain, 55.0%) was the most frequent coding in the BMS group, which was higher than 11.4% in the control group (p < 0.001). Surprisingly, there was no significant difference between the peripheral and central BMS subgroups with regard to the Z-scores of any of the nine QST parameters (p > 0.097).
Conclusions:
The results of the lingual nerve blocks demonstrated two distinct phenotypes with either peripheral or central mechanisms but no direct impact on somatosensory function. Overall, somatosensory function in BMS patients seems abnormal in the painful areas compared to matched controls with a conspicuous loss of thermosensory function.

Related Concept Videos
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia
 01:12
Local Anesthetics: Adverse Effects
Once absorbed into the systemic circulation, local anesthetics can affect the organs that depend on the functioning of sodium...
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:23
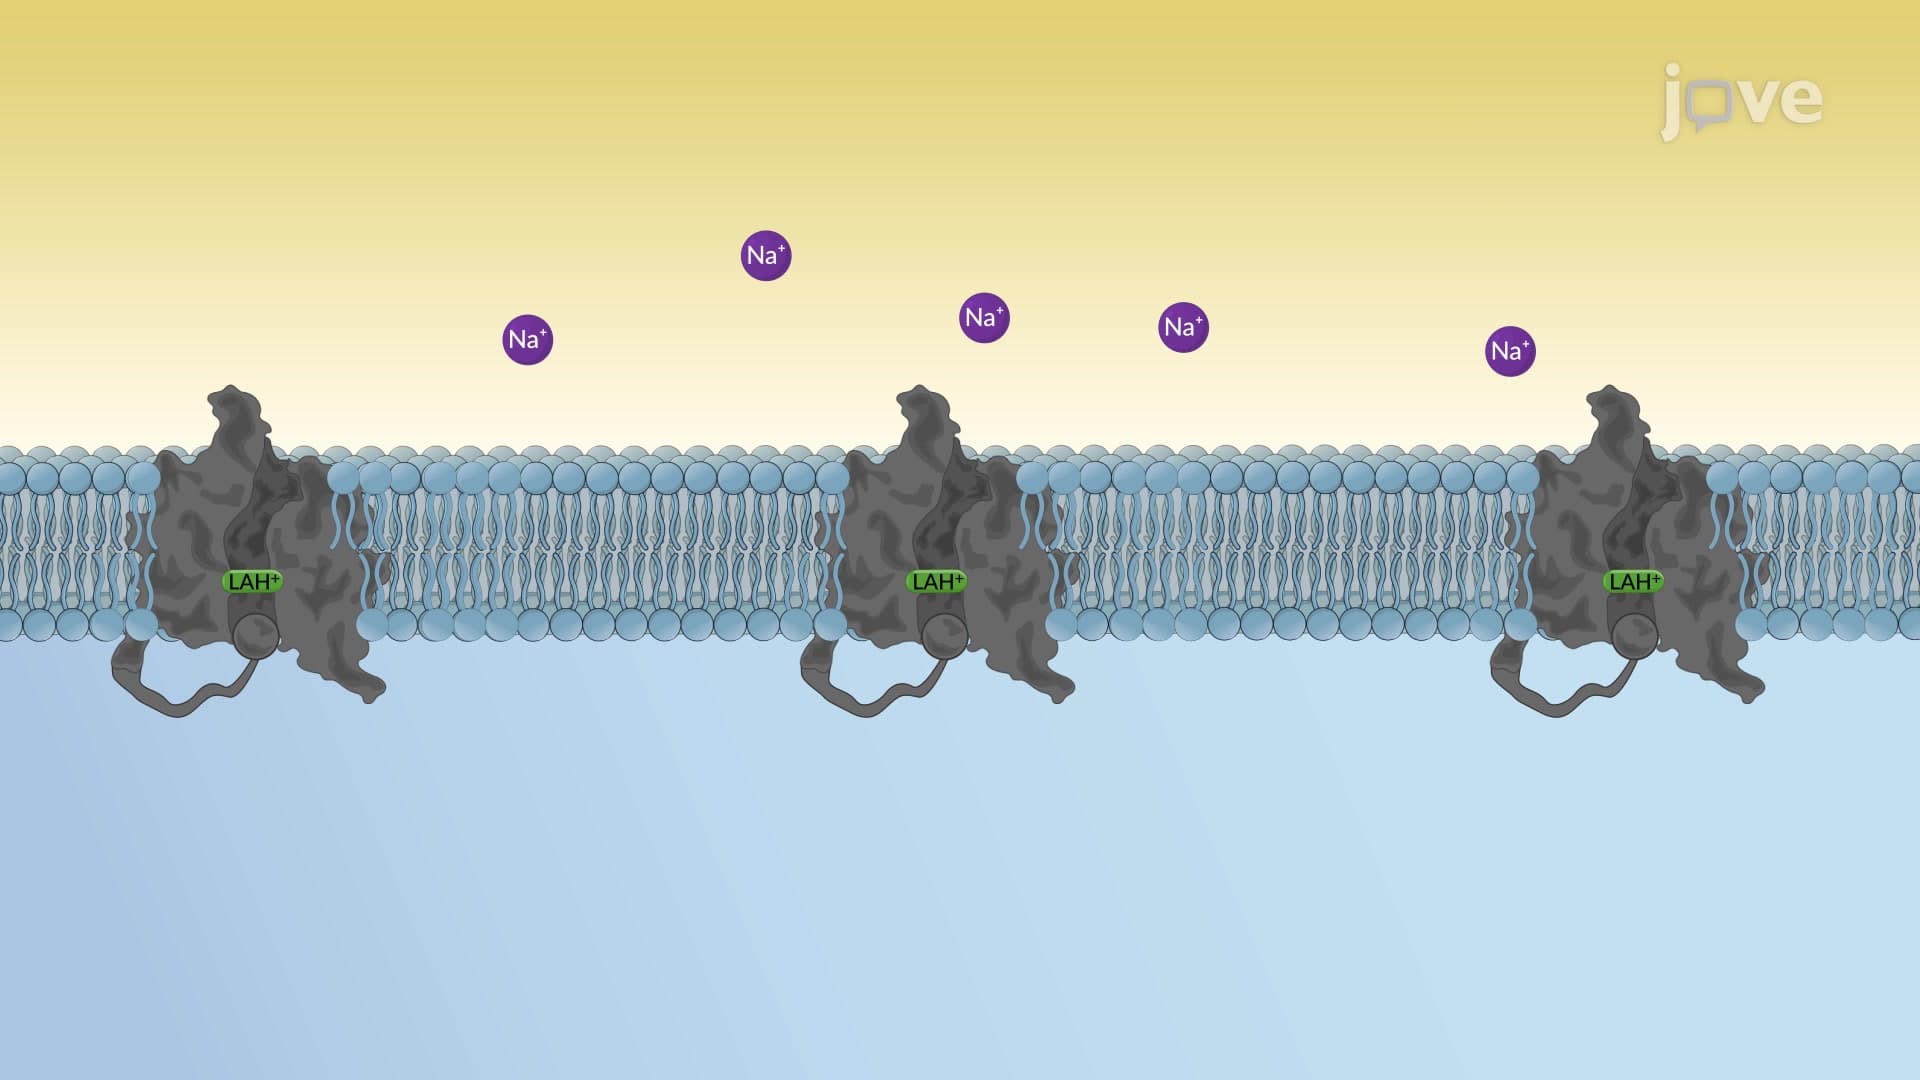
Local Anesthetics: Mechanism of Action
Local anesthetics are amphiphilic molecules consisting of a hydrophobic aromatic part linked to a hydrophilic group by an ester or amide linkage. They are weak bases and are usually available as salts, which increases their solubility and stability. Once administered, LAs exist in the body either...