Related Experiment Video
Updated: Jun 8, 2025
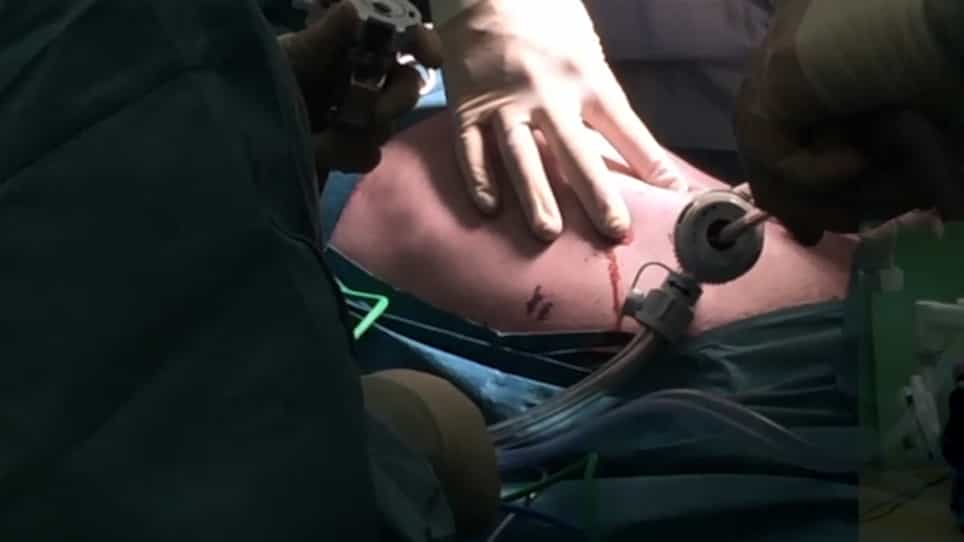

Robotic Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: December 14, 2019
Preventive Measures and Risk Factors for Post-ERCP Pancreatitis: A Systematic Review and Individual Patient Data
Christina J Sperna Weiland1, Venkata S Akshintala2, Anmol Singh2
1Department of Gastroenterology and Hepatology, Radboud University Medical Center, Geert Grooteplein Zuid 10, 6525 GM, Nijmegen, Netherlands. Christa.spernaweiland@radboudumc.nl.

Background:
Post-endoscopic retrograde cholangiopancreatography (ERCP) pancreatitis (PEP) is the most common complication of ERCP, with limited studies comparing combined prophylactic measures and their efficacy relative to individual patient risk profiles. This study aims to perform an individual patient data meta-analysis (IPDMA) to evaluate the contribution of patient and ERCP-related risk factors to PEP development and to identify the best prophylaxis strategies according to the patient's risk profile.
Methods:
We systematically searched MEDLINE, Embase, and Cochrane databases until November 2022 for randomized controlled PEP prophylaxis trials. We invited authors to share individual patient data, including PEP risk profile and prophylaxes used. PEP incidence rates for different prophylaxis were calculated. Efficacy was compared using multilevel logistic regression and expressed as relative risk (RR). Subgroup analysis evaluated the role of patient and ERCP-related risk factors in developing PEP.
Results:
Data from 11 studies, including 6430 patients, were analyzed. After adjusting for risk factors, rectal NSAIDs (RR 0.69, 95%CI 0.54-0.88) and peri-procedural high-volume intravenous fluid (IVF) (RR 0.40, 95%CI 0.21-0.79) were effective in reducing PEP incidence, while no benefit was noted with pancreatic duct (PD) stents (RR 1.25, 95%CI 0.91-1.73). In patients receiving rectal NSAIDs (n = 2617), difficult cannulation (RR 1.99, 1.45-2.73), contrast injection into the pancreatic duct (PD) (RR2.37, 1.68-3.32), and prior history of PEP (RR 1.90, 1.06-3.41) were associated with increased PEP risk.
Conclusion:
This IPDMA confirms that rectal NSAIDs and peri-procedural IVF are effective PEP prophylactic strategies. Further studies focusing on combination therapy or the development of personalized PEP risk calculators are needed to improve prophylactic strategies.


Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...