Related Experiment Video
Updated: Jun 7, 2025
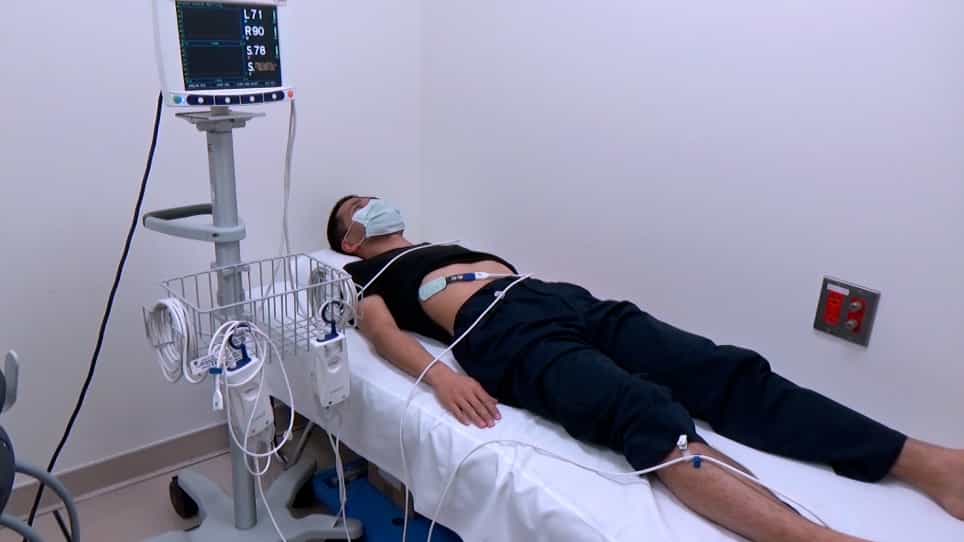

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Inborn errors of metabolism in neonates and pediatrics on varying dialysis modalities: a systematic review and
Manan Raina1, Kush Doshi2, Archana Myneni2
1Hawken High School, Cleveland, OH, USA.

Insights
Continuous kidney replacement therapy (CKRT) may offer better survival rates for children with inborn errors of metabolism (IEMs) compared to hemodialysis (HD) or peritoneal dialysis (PD). CKRT also shows potential for improved ammonia control in pediatric IEM patients.
Area of Science:
- Pediatric Nephrology
- Metabolic Disorders
- Critical Care Medicine
Background:
- Inborn errors of metabolism (IEMs) can cause dangerous elevations in blood leucine and ammonia levels.
- Kidney replacement therapy (KRT) is a critical treatment for pediatric IEMs, necessitating prompt intervention to prevent neurological damage.
Purpose of the Study:
- To systematically review and compare the efficacy of different KRT modalities (CKRT, HD, PD) in neonates and pediatric patients with IEMs.
- To evaluate survival rates and the reduction of ammonia and leucine levels across various KRT methods.
Main Methods:
- A comprehensive literature search was performed across PubMed, Web of Science, and Embase.
- Included studies reported survival rates and toxic metabolite clearance data in pediatric IEM patients undergoing KRT.
- Data on mortality and ammonia reduction were analyzed using statistical methods, with bias assessed via the Newcastle Ottawa scale.
Main Results:
- The review included 37 studies with 642 pediatric patients.
- Pooled mortality rates were 24.84% for CKRT, 34.42% for PD, and 34.14% for HD.
- CKRT demonstrated a trend towards faster ammonia reduction compared to PD, and higher pre-KRT ammonia levels correlated with increased mortality.
Conclusions:
- CKRT may be associated with lower mortality rates and better hemodynamic control in pediatric IEM patients compared to HD and PD.
- All KRT modalities showed efficacy in reducing ammonia and leucine levels, though HD trended towards faster ammonia reduction.
- Further research is warranted due to sample size limitations, but CKRT shows promise for managing hyperammonemia in IEMs.
Background:
Some inborn errors of metabolism (IEMs) resulting in aberrations to blood leucine and ammonia levels are commonly treated with kidney replacement therapy (KRT). Children with IEMs require prompt treatment, as delayed treatment results in increased neurological and developmental morbidity.
Objectives:
Our systematic review in neonates and pediatrics evaluates survival rates and reductions in ammonia and leucine levels across different KRT modalities (continuous KRT (CKRT), hemodialysis (HD), peritoneal dialysis (PD)).
Data Sources:
A literature search was conducted through PubMed, Web of Science, and Embase databases for articles including survival rate and toxic metabolite clearance data in pediatric patients with IEM undergoing KRT.
Study Eligibility Criteria:
Cross-sectional, prospective, and retrospective studies with survival rates reported in patients with IEM with an intervention of CKRT, PD, or HD were included. Studies with patients receiving unclear or multiple KRT modalities were excluded.
Study Appraisal And Synthesis Methods:
Analysis variables included efficacy outcomes [% reduction in ammonia (RIA) from pre- to post-dialysis and time to 50% RIA] and mortality. The Newcastle Ottawa Risk of Bias quality assessment was used to assess bias. All statistical analyses were performed with MedCalc Statistical Software version 19.2.6.
Results:
A total of 37 studies (n = 642) were included. The pooled proportion (95% CI) of mortality on CKRT was 24.84% (20.93-29.08), PD was 34.42% (26.24-43.33), and HD 34.14% (24.19-45.23). A lower trend of pooled (95% CI) time to 50% RIA was observed with CKRT [6.5 (5.1-7.8)] vs. PD [14.4 (13.3-15.5)]. A higher mortality was observed with greater plasma ammonia level before CKRT (31.94% for ≥ 1000 µmol/L vs. 15.04% for < 1000 µmol/L).
Conclusions And Implications Of Key Findings:
Despite the limitations in sample size, trends emerged suggesting that CKRT may be associated with lower mortality rates compared to HD or PD, with potential benefits including prevention of rebound hyperammonemia and improved hemodynamic control. While HD showed a trend towards faster achievement of 50% RIA, all modalities demonstrated comparable efficacy in reducing ammonia and leucine levels.
Prospero Registration:
CRD42023418842.
More Related Videos


Related Concept Videos
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...