Related Experiment Video
Updated: Jun 7, 2025


5/6th Nephrectomy in Combination with High Salt Diet and Nitric Oxide Synthase Inhibition to Induce Chronic Kidney Disease in the Lewis Rat
Published on: July 3, 2013
Sodium-chloride difference is not strongly correlated with base excess in chronic kidney disease: an anion gap
Moritz Kerbl-Knapp1, Gregor Lindner2, Georg-Christian Funk3,4
1Department of Internal Medicine 1, Pyhrn-Eisenwurzenklinikum Steyr, Steyr, Austria. Moritz.Kerbl-Knapp@ooeg.at.

Introduction:
The prevalence of metabolic acidosis is high in patients with chronic kidney disease (CKD). For the diagnosis, a blood gas analysis is necessary, but not always available. The aim of the study was to evaluate the base excess (BE) of the sodium-chloride difference (BENa-Cl = Na+-Cl--34 mmol/l) as a screening parameter for hyperchloremic metabolic acidosis.
Methods And Statistical Analysis:
We retrospectively performed acid-base analyses of 168 non-dialysed patients with CKD according to the physiologic and to the Stewart's approach. We performed linear regression analysis, Bland-Altman plot and receiver operating characteristics (ROC) analysis of BENa-Cl and BE to evaluate the accuracy of BENa-Cl predicting the BE. We further investigated possible confounding factors.
Results:
The corrected R2 for the correlation of BENa-Cl and BE was 0.60 (p < 0.001). The Bland-Altman plot showed a good overall agreement. The bias was negligible, but the 95%-limits of agreement showed a wide interval (10.4 mmol/l). For BE ≤ 2 mmol/l, the ROC analysis yielded an AUC of 0.89 and moderate sensitivity (0.75) and specificity (0.86) for the optimal BENa-Cl threshold (≤ 2 mmol/l). Subgroup analysis showed similar results. The main factor for the imprecision of BENa-Cl predicting the BE across all stages of CKD is the variability of the serum anion gap (SAG).
Conclusions:
The BENa-Cl is not an adequate parameter for screening of hyperchloremic acidosis because of the high variability of the SAG. Only, if the BENa-Cl is ≤ 5 mmol/l, a hyperchloremic acidosis should be suspected. Therefore, a complete blood gas analysis is necessary for the correct diagnosis of acid-base disorders in patients with chronic kidney disease.
More Related Videos
 09:47
Standardized Measurement of Nasal Membrane Transepithelial Potential Difference NPD
Published on: September 13, 2018
 07:38
Functional Characterization of Na+/H+ Exchangers of Intracellular Compartments Using Proton-killing Selection to Express Them at the Plasma Membrane
Published on: March 30, 2015
Related Concept Videos
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...
 01:29
Renal Regulation of Acid-Base Balance
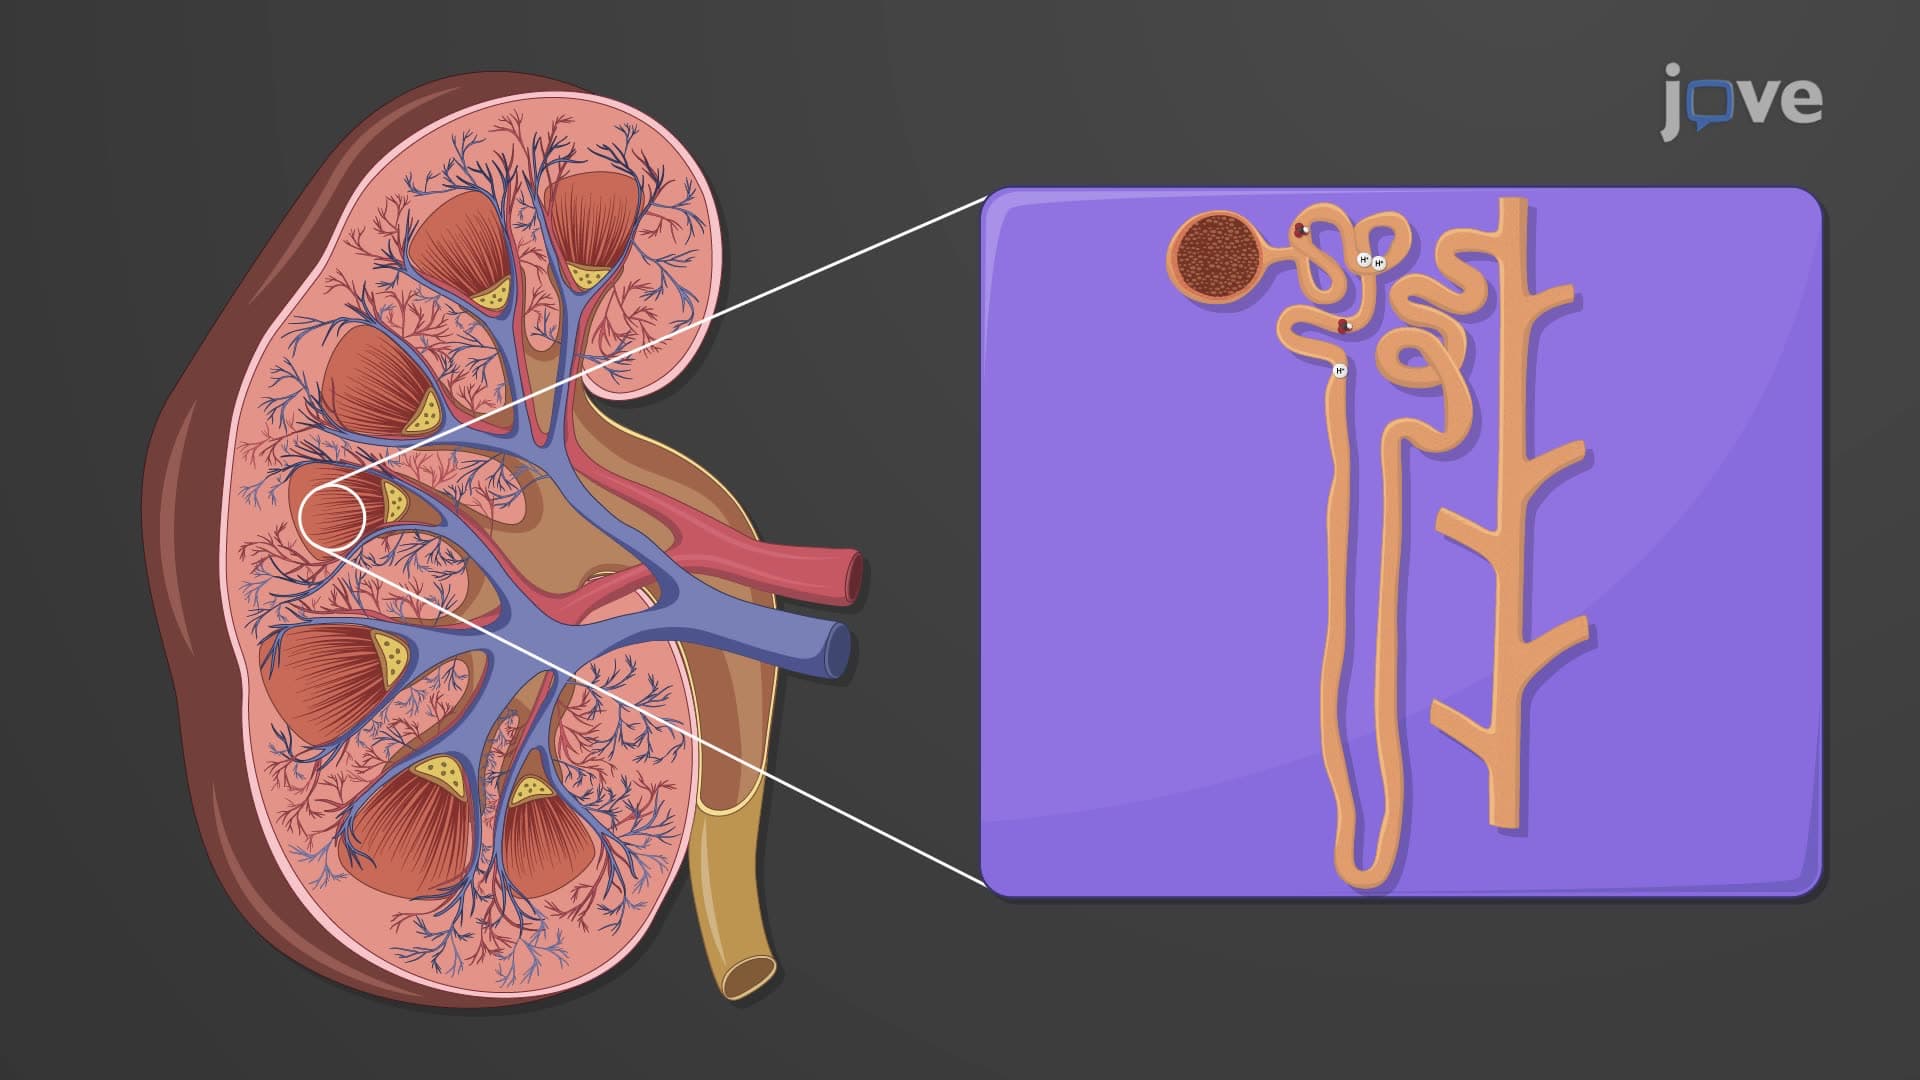
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
Renal Tubule and Collecting Duct
Proximal Convoluted Tubule (PCT):
The PCT is the initial segment of the renal tubule, extending from the Bowman's capsule that encloses the glomerulus. Its convoluted structure and microvilli-lined cells increase the surface area for reabsorption. The PCT reabsorbs glucose, amino acids, sodium, and water from the filtrate, ensuring essential...
 01:24
Roles of Electrolytes: Sodium and Potassium