Related Experiment Video
Updated: Jun 7, 2025


Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Echocardiographic Markers of Early Left Ventricular Dysfunction in Asymptomatic Aortic Regurgitation: Is It Time to
Vidhu Anand1, Hector I Michelena1, Christopher G Scott2
1Department of Cardiovascular Medicine, Mayo Clinic, Rochester, Minnesota, USA.

Background:
The ideal timing for surgery in asymptomatic chronic aortic regurgitation (AR) remains unclear. New thresholds for left ventricular ejection fraction (LVEF), left ventricular (LV) indexed end-systolic volume (iESV), and global longitudinal strain (GLS) have been associated with mortality in these patients. These represent markers of early LV dysfunction.
Objectives:
The authors sought to assess the relationship between these markers (LVEF <60%, iESV ≥45 mL/m2, and GLS worse than -15%) and mortality, comparing them to Class I/IIa American College of Cardiology/American Heart Association guideline recommendations and absence of any of these.
Methods:
A total of 673 asymptomatic patients with chronic clinically significant (≥ moderate-severe) AR between 2004 and 2019 at a single referral center were retrospectively analyzed. The primary study outcome was all-cause mortality.
Results:
Mean age was 57 ± 17 years, 97 (14%) were female, 293 (45%) had hypertension, and 273 (41%) had an abnormal number of valve cusps. Aortic valve replacement was performed in 281 (48%) patients, and 69 (10%) died while under surveillance (without aortic valve replacement). LVEF <60% was present in 296 (44%) patients, 122 (25%) of 482 had GLS worse than -15%, and 261 (39%) had iESV ≥45 mL/m2. Mortality under surveillance was highest when Class I/IIa recommendations were present (HR: 4.22; 95% CI: 2.15-8.29), followed by the presence of 1 or more markers of early LV dysfunction (HR: 2.18; 95% CI: 1.21-3.92); no markers was used as the reference (all, P < 0.05). LVEF showed the strongest association with mortality, statistically slightly better than GLS and iESV. In the absence of Class I/IIa recommendations, 1 marker of early LV dysfunction was associated with higher, although not statistically significant, mortality compared with no markers (P = 0.063), followed by 2 markers; highest mortality was when all 3 markers were present (HR: 5.46 [95% CI: 2.51-11.90]; P < 0.001).
Conclusions:
Patients with asymptomatic clinically significant chronic AR incur a survival penalty when Class I/IIa guideline recommendations are attained. In patients without these recommendations, at least 2 markers of early LV dysfunction identify those with higher mortality risk who may benefit from early surgery.

Related Concept Videos
 01:15
Aortic Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical features and Diagnostic Tests
 01:20
Mitral Regurgitation I: Introduction
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:17
Aortic Regurgitation IV: Nursing Management
 01:25
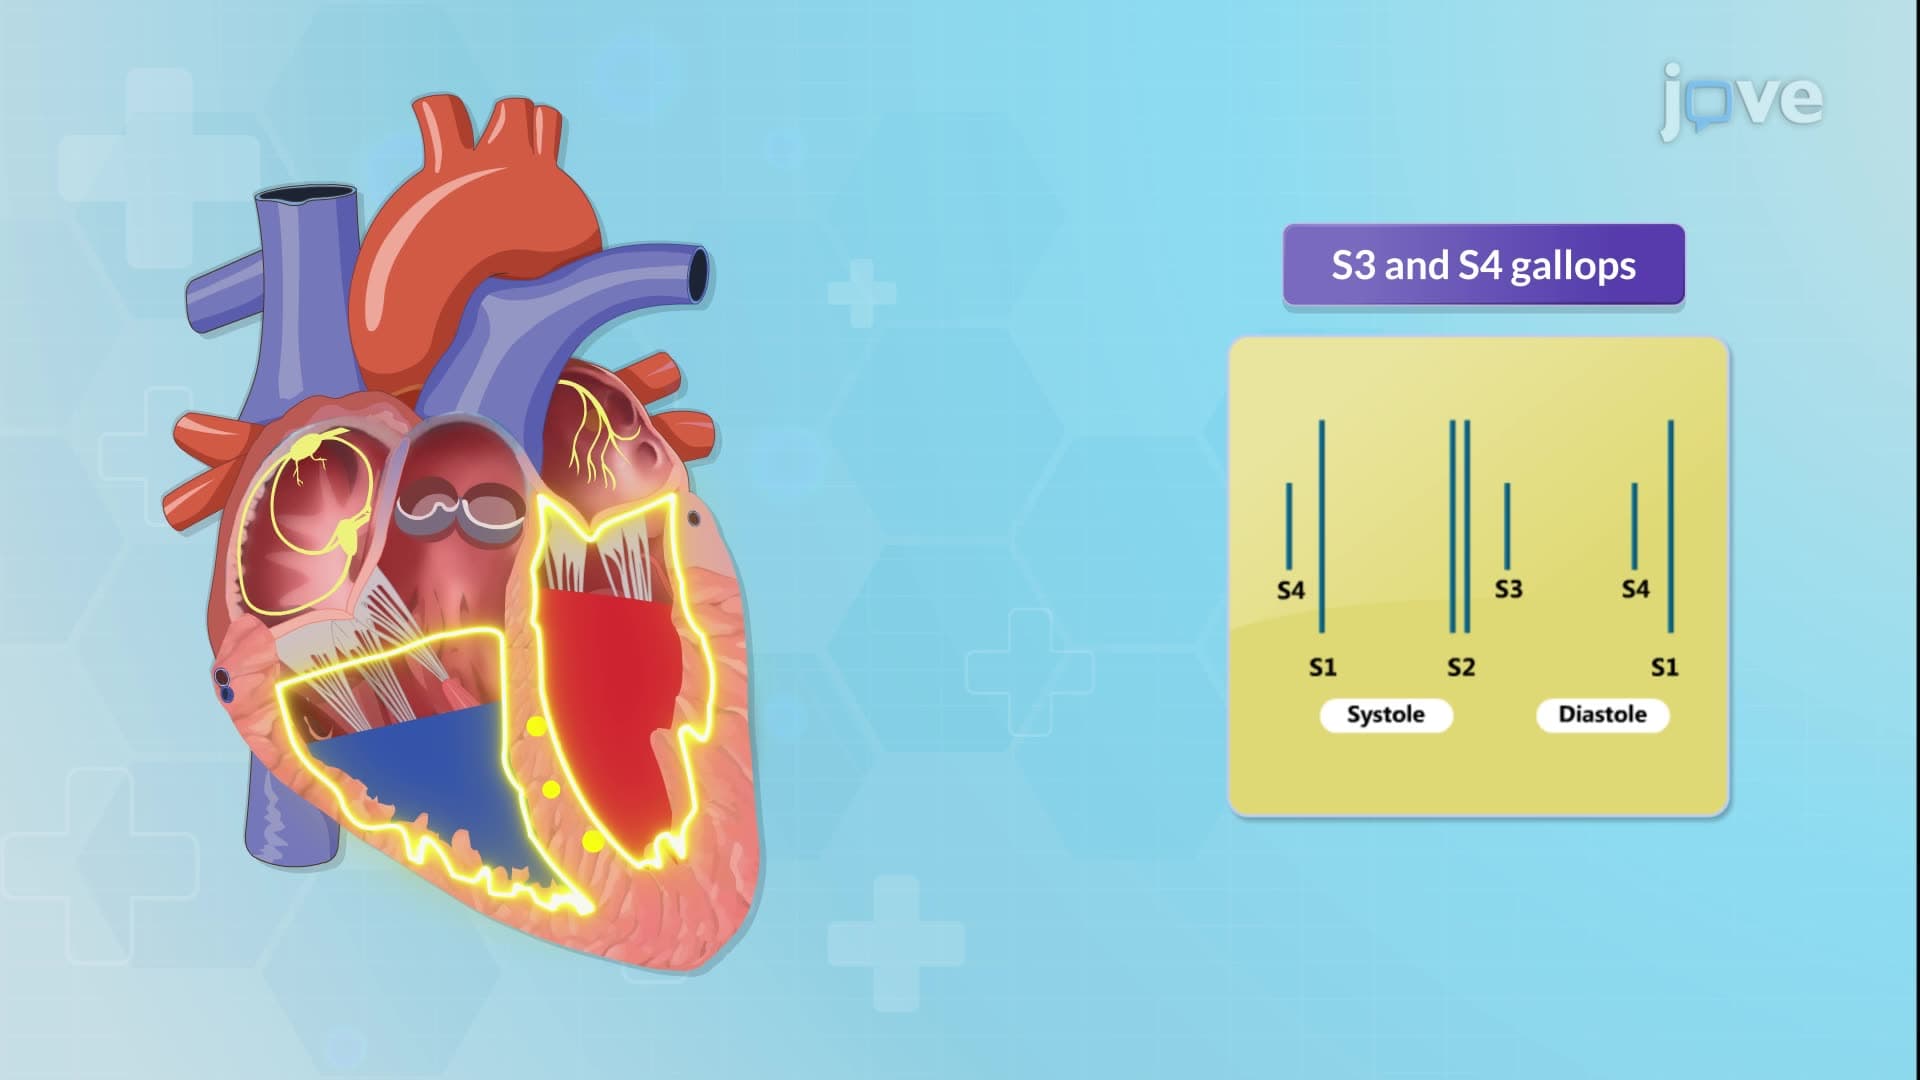
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops: