Related Experiment Video For Carpal tunnel
Updated: Jun 7, 2025
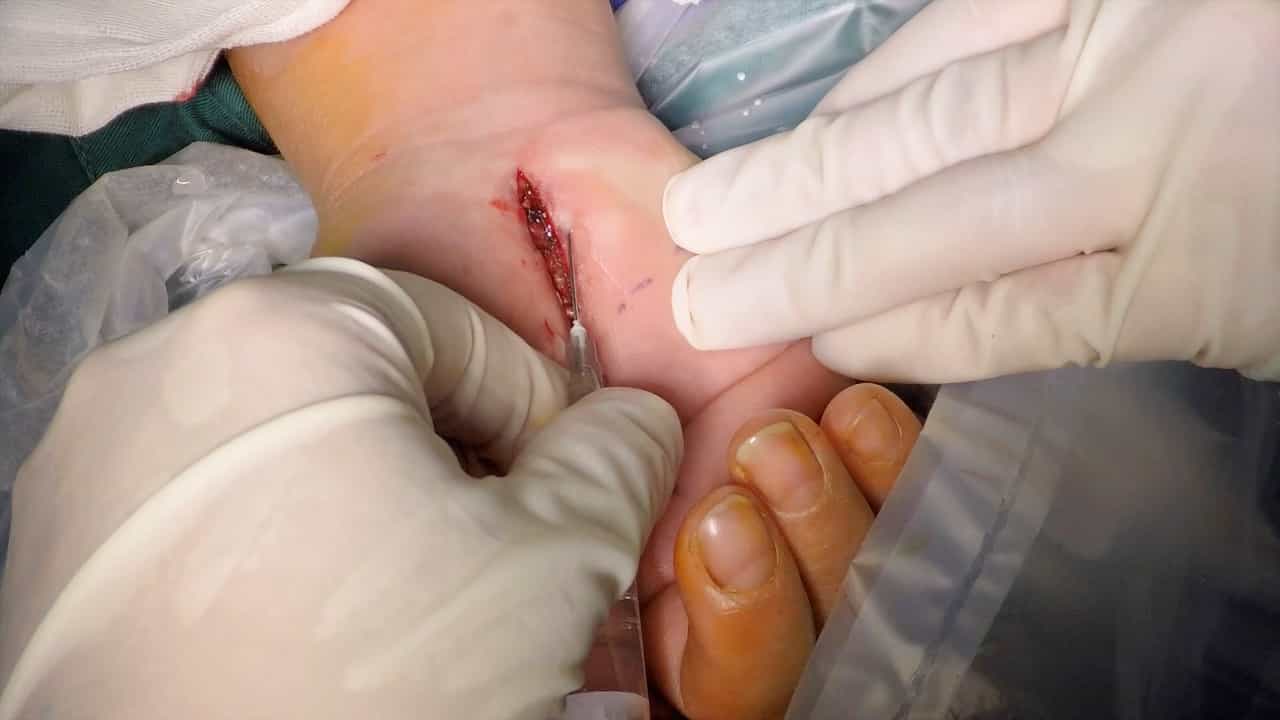

Metacarpal Small Incision for Carpal Tunnel Syndrome
Published on: April 5, 2024
Predictive Factors for Converting Endoscopic to Open Carpal Tunnel Release
Loretta Coady-Fariborzian1,2, Christy Anstead1,2
1Surgical Services, Plastic Surgery Section, Malcom Randall VA Medical Center, Gainesville, FL, USA.

Abstract:
Introduction: Both open and endoscopic methods of carpal tunnel release are accepted treatments for carpal tunnel syndrome. The objective was to determine the endoscopic to open conversion rate of all carpal tunnel surgeries. We evaluated potential predictive factors for an increased rate of conversion. Methods: The IRB/IRBnet approved (#20210613/1639264) a retrospective chart review of all attempted endoscopic carpal tunnel surgeries performed from July 1, 2012 through June 30, 2021. Charts were reviewed for procedure, age, sex, body mass index (BMI), electromyograph (EMG) reading, wrist arthritis on x-ray, preoperative steroid injections, trainee as surgeon, diabetes, hand dominance, and operated side. Conversion rate was noted. A chi-square test using a P-value of <0.05 was used to determine the statistical significance of the patients' age, sex, BMI, EMG severity, the presence of wrist arthritis, preoperative steroid injections, resident as surgeon, diabetic status, and operated hand dominance as predictive factors for conversion. Results: The plastic surgery service attempted 1053 endoscopic carpal tunnel releases using the Chow dual port technique over a 9-year period. Forty-five cases converted to an open release. Median age (P = 0.54), sex (P = 0.43), median BMI (P = 0.76), EMG severity (P = 0.20), wrist arthritis (P = 1.0), preoperative steroid injections (P = 0.65), resident surgeon (P = 0.53), diabetes (P = 0.50), and operated hand dominance (P = 0.36) were not statistically significant predictive risk factors. Nineteen of 45 converted cases had a future successful contralateral endoscopic release. Conclusion: Our study found a 4.27% endoscopic to open conversion rate. No identifiable risk factors could predict conversion. Prior conversion does not determine a future contralateral conversion.