Related Experiment Video
Updated: Jun 7, 2025
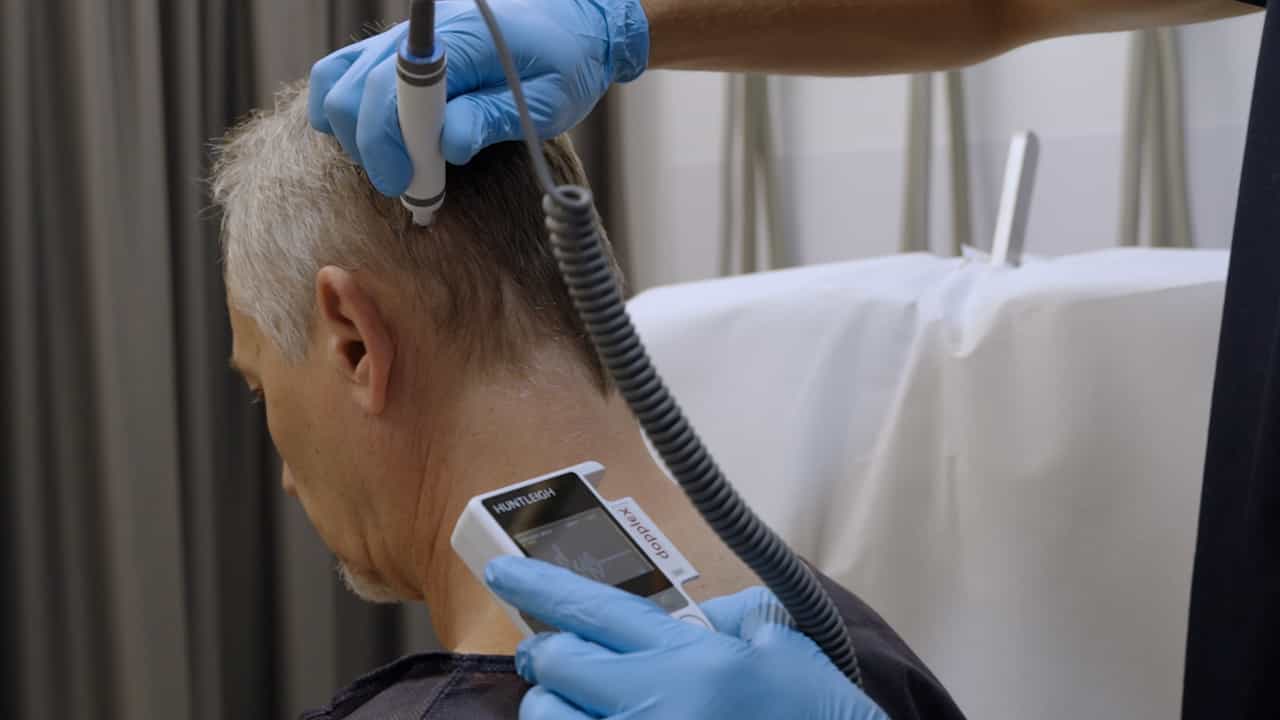
Author Spotlight: Minimally Invasive Relief for Occipital Neuralgia at the Nuchal Line
Published on: September 13, 2024
A Randomized Controlled Non-Inferiority Trial Evaluating Opioid-Free versus Opioid-Sparing Analgesia for Orbital
Rui Zhang1, Yongjian Mai1, Huijing Ye2
1Department of Anesthesiology, State Key Laboratory of Ophthalmology, Zhongshan Ophthalmic Center, Sun Yat-sen University, Guangdong Provincial Key Laboratory of Ophthalmology Visual Science, Guangdong Provincial Clinical Research Center for Ocular Diseases, Guangzhou, 510060, People's Republic of China.

Background And Objectives:
Opioid-minimizing strategies are making their appearance in enhanced recovery after surgery. This study is aimed to explore the potential advantages of opioid-free analgesia (OFA) compared to opioid-sparing analgesia (OSA) in patients undergoing orbital fracture reconstruction.
Methods:
In this prospective, single-center, randomized controlled study, we randomly recruited 122 patients undergoing orbital fracture reconstruction under general anesthesia. Patients received total intravenous anesthesia with a flexible laryngeal mask airway, and multimodal analgesia with either OSA or OFA methods. The OSA group (n = 61) received low doses of fentanyl and nonsteroidal anti-inflammatory drugs (NSAIDs), and the OFA group (n = 61) received medial canthus peribulbar block (MCPB) combined with NSAIDs. The primary outcomes consisted of area-under-the-curve (AUC) of the numerical rating scale (NRS) pain score, and the incidence of postoperative nausea and vomiting (PONV) through the first 24h.
Results:
Compared to the OSA group, the OFA group demonstrated non-inferiority in postoperative analgesia through the first 24 postoperative hours (difference of the medians, -6; 95% confidence interval [CI], -12 to 6), but failed to meet the non-inferiority criterion in the incidence of PONV (difference ratio, 3%; 95% CI, -7% to 14%). The Quality of Recovery-40 questionnaire (QoR-40) scores on postoperative day 1 was significantly higher in group OFA compared to group OSA (188 [178 to 196] vs 181 [169 to 191], respectively; P = 0.005).
Conclusion:
In orbital fracture reconstruction, both OFA and OSA strategies provide effective postoperative pain relief, but OFA using MCPB combined NSAIDs enhances the quality of early postoperative recovery.
Registered:
Chinese Clinical Trial Registry ChiCTR1900028088.

