Related Experiment Video
Updated: Sep 15, 2026


Evaluation of Zebrafish Kidney Function Using a Fluorescent Clearance Assay
Published on: February 20, 2015
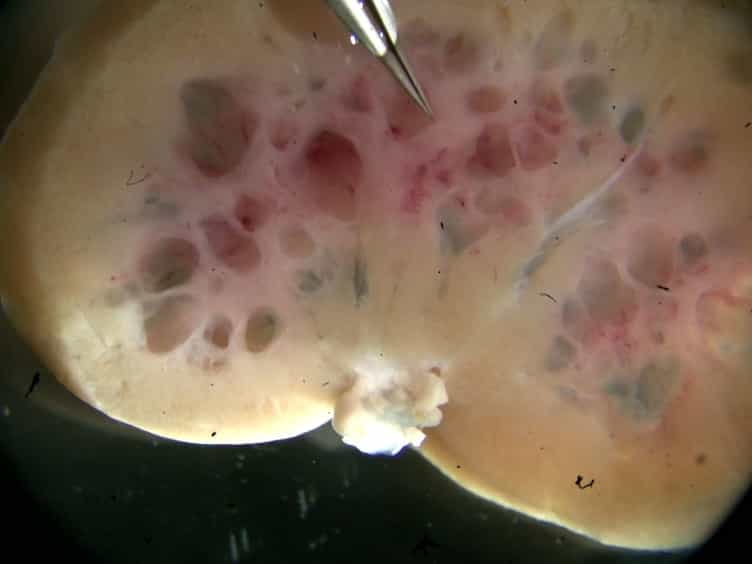
Infantile polycystic disease of the liver and kidneys

Insights
Infantile polycystic kidney disease (IPKD) shows varied severity. Early and extensive kidney cysts indicate poor survival, while less severe cases allow long-term survival, highlighting the need for individual patient evaluation.
Area of Science:
- Pediatric Nephrology
- Medical Genetics
- Hepatology
Background:
- Recessively inherited infantile polycystic disease (IPCD) presents a significant challenge in pediatric healthcare.
- Understanding the phenotypic spectrum is crucial for accurate diagnosis and prognosis.
Purpose of the Study:
- To document renal tubular cyst formation and hepatic fibrosis in infantile polycystic disease (IPCD).
- To assess survival rates in relation to disease severity.
- To evaluate the utility of current IPCD classification systems.
Main Methods:
- Histopathological examination of kidney and liver tissue from eleven IPCD patients.
- Correlation of pathological findings with clinical outcomes and survival data.
Main Results:
- Infants with >90% cystic renal change did not survive past 20 days.
- Patients with 20-75% cystic renal change showed survival rates of 6-21 years.
- All patients exhibited hamartomatous bile duct proliferation; portal fibrosis was most severe in the oldest patient.
- Sibling cases displayed dissimilar clinical courses and pathological expressions of renal disease.
Conclusions:
- Infantile polycystic disease (IPCD) exhibits a spectrum of phenotypic expression.
- Tissue diagnosis in individual patients has prognostic implications.
- Current classifications may not adequately represent the diverse genetic and clinical presentations of IPCD.
- Each child with IPCD requires separate evaluation due to variable disease progression.
Abstract:
Kidney and liver tissue from eleven patients with recessively inherited infantile polycystic disease (IPCD) were examined to document the extent of renal tubular cyst formation and hepatic fibrosis, to assess survival, and to examine the usefulness of current classifications. Four infants with 90% or more cystic renal change did not survive beyond twenty days. In contrast five of the seven less severely diseased patients with a 20-75% range of cystic change are still alive at six to twenty-one years of age. Liver samples showed hamartomatous bile duct proliferation in all patients studied with the most prominent portal fibrosis in the oldest patient. In both families with two affected siblings, the clinical course and pathological expression of renal disease were dissimilar. Tissue analysis from these cases is consistent with the idea that IPCD has a spectrum of phenotypic expression with prognostic implications from tissue diagnosis in the individual patient, but not necessarily as four genetically determined rigidly defined subgroups. It is concluded that each affected child with IPCD must be evaluated separately.
More Related Videos
 07:35
Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
 08:46
Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not related to...
 01:10
Nephrons
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous capillaries...
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:24
Nephrotic Syndrome I : Introduction