
LOCAlizaTion and clinical corrElation of Left Bundle Branch Pacing lead: Insights from a computed tomographic
Shunmuga Sundaram Ponnusamy1, Nicki Barka2, Zhongping Yang2
1Department of Cardiology, Velammal Medical College Hospital and Research Institute, Madurai, India.

Background:
Left bundle branch pacing (LBBP) provides physiological activation with stable pacing parameters. However, there is a paucity of data on direct assessment of lead stability.
Objectives:
The purpose of this study was to assess the stability of an LBBP lead using computed tomographic angiography (CTA) during medium-term follow-up and to correlate the anatomic location of the lead and electrophysiological characteristics of LBBP.
Methods:
Consecutive patients with successful LBBP using a lumenless lead were included. Patients without LBB capture, contrast allergy, and renal dysfunction were excluded. CTA was performed postimplantation and at 6 months. Primary endpoint was defined as consistent left bundle branch (LBB) capture with helix tip separated from the left ventricular (LV) blood pool by <2 mm by CTA at 6 months. Secondary endpoints were defined as loss of conduction system capture (LOCSC) or perforation with complete capture loss at 6 months.
Results:
Overall, 67 of 105 patients who underwent CTA after successful LBBP were included. Mean follow-up was 33.8 ± 4.4 months. Nonselective to selective capture transition was noted in 82% (n = 55). The lead remained stable at 6 months, with no difference in mean distance between LV blood pool and helix tip (-0.5 ± 1.8 mm vs -0.1 ± 2.1 mm; P = .23). Primary endpoint was achieved in 89.5% (n = 60). Consistent LBB capture (group I) at 6 months was noted in 94% (n = 63). LOCSC (group 2) was noted in 6% (n = 4) at 6 months. No perforation into the LV cavity with complete loss of capture was seen. Lead displacement by >2 mm away from the LV blood pool (sensitivity 100%; specificity 95%) and lack of nonselective to selective capture transition during implantation (odds ratio 18.0; 95% confidence interval 1.7-192.7; P = .01) were LOCSC predictors.
Conclusion:
Deep septal deployment of the lead in the LV subendocardium for LBB capture is safe, with 94% of patients showing consistent conduction system capture during follow-up.
More Related Videos
 09:57
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
 06:59
Improved Registration of 3D CT Angiography with X-ray Fluoroscopy for Image Fusion During Transcatheter Aortic Valve Implantation
Published on: June 3, 2018
Related Concept Videos
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:28
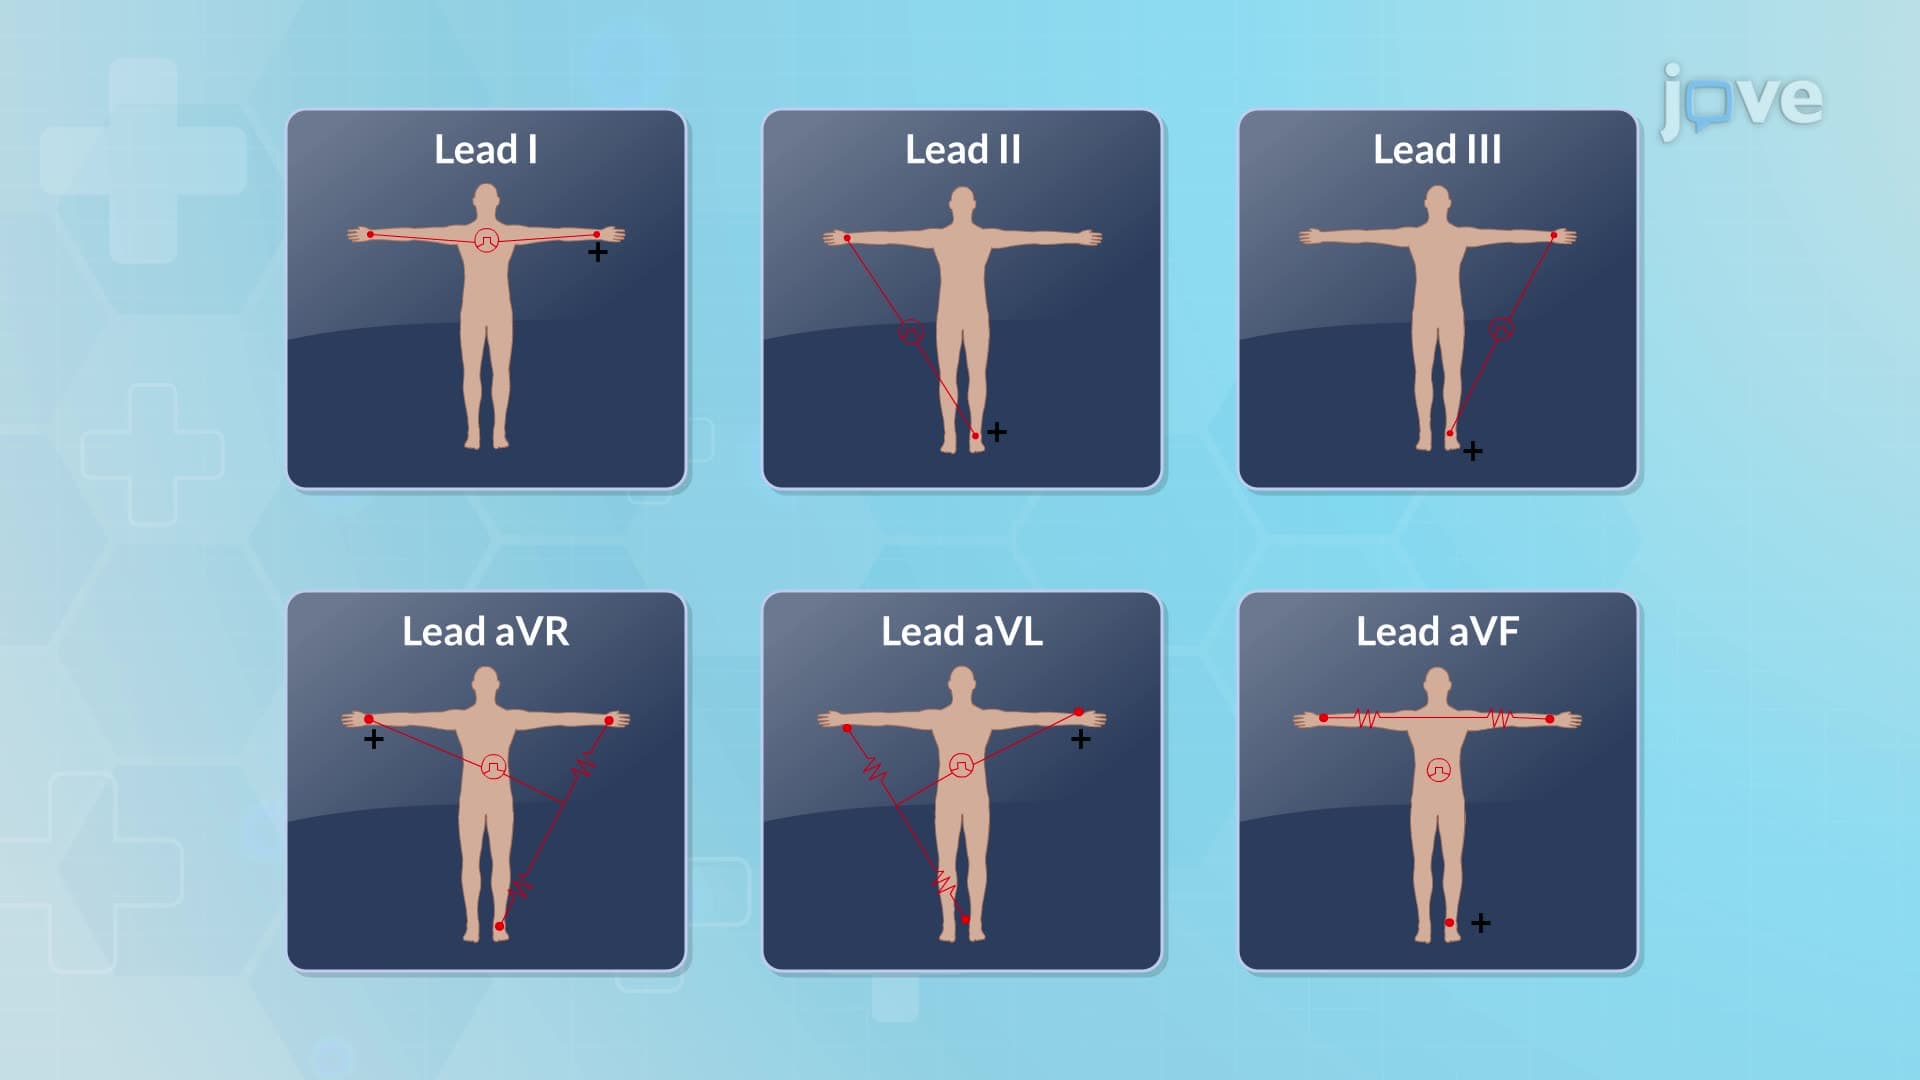
Electrocardiogram Fundamentals
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...