
Associations of iron deficiency with cardiac function, congestion, exercise capacity and prognosis in heart failure
Nicolò De Biase1, Lavinia Del Punta1, Wouter L'Hoyes2
1Department of Clinical and Experimental Medicine, University of Pisa, Pisa, Italy.

Insights
Transferrin saturation (TSAT) <20% best defines iron deficiency in heart failure (HF) patients, linking to congestion and poor exercise capacity. This definition, along with low iron levels, predicts worse HF prognosis.
Area of Science:
- Cardiology
- Iron Metabolism
- Heart Failure Pathophysiology
Background:
- Defining iron deficiency (ID) in heart failure (HF) patients remains unclear.
- Different ID definitions may impact understanding of HF patient characteristics and outcomes.
Purpose of the Study:
- To assess the relationship between various ID definitions and cardiac structure/function, congestion, exercise capacity, and prognosis in HF outpatients.
Main Methods:
- Compared guideline-defined ID (G-ID) with alternative definitions (TSAT <20%, iron ≤13 μmol/L, ferritin thresholds).
- Assessed relationships with echocardiographic measures, exercise intolerance, and adverse outcomes (HF hospitalization or mortality).
- Analyzed 1502 HF outpatients, including those with preserved and reduced ejection fraction.
Main Results:
- TSAT <20% and G-ID were associated with increased left atrial volume, but not altered LVEF.
- Lower TSAT and iron levels correlated with increased ultrasound-detected congestion.
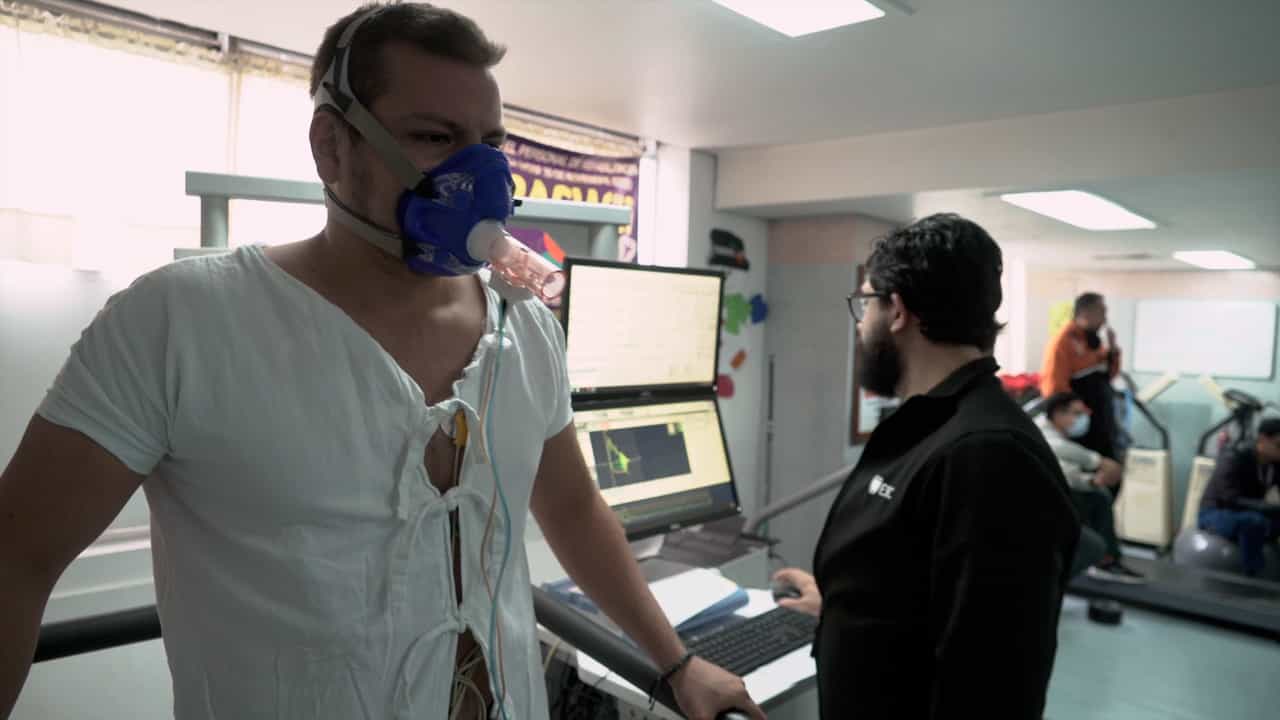
- TSAT <20% was directly associated with peak oxygen uptake, unlike ferritin.
- TSAT <20% and iron ≤13 μmol/L predicted worse prognosis, while G-ID and ferritin-based definitions did not.
Conclusions:
- TSAT <20% is a more reliable indicator of congestion and reduced functional capacity in HF patients than other ID definitions.
- TSAT <20% and low iron levels are significant predictors of adverse prognosis in HF, regardless of LVEF.
- Current guideline-based ID definitions may not accurately reflect HF patient outcomes.
Aims:
Uncertainty exists about defining true iron deficiency (ID) in heart failure (HF) patients. We assessed the relationship of different ID definitions with cardiac structure and function, congestion, exercise capacity, and prognosis in HF outpatients.
Methods And Results:
Iron deficiency was defined according to guidelines (G-ID: ferritin <100 ng/ml or ferritin 100-299 ng/ml with transferrin saturation [TSAT] <20%). Alternative ID definitions based on TSAT (<20%), iron (≤13 μmol/L), and ferritin (<100 or < 300 ng/ml) were explored. Relationships with rest/exercise measures of cardiac function and congestion using ultrasound, effort intolerance and adverse outcome (HF hospitalizations or all-cause mortality) were assessed. Of 1502 patients (72% with left ventricular ejection fraction [LVEF] ≥50%), 471 (31%) had TSAT <20%, while 728 (48%) had G-ID. Patients with TSAT <20% or G-ID had greater left atrial volume but similar LVEF. Lower TSAT, iron and haemoglobin, but not ferritin, were associated with more signs of congestion by ultrasound. After correcting for multiple clinical variables, including haemoglobin, TSAT was directly associated with peak oxygen uptake (standardized coefficient 0.069, p = 0.041), while ferritin was not. There was no interaction with HF phenotype (HF with preserved vs. reduced LVEF). During a median follow-up of 18 months, TSAT <20% and iron ≤13 μmol/L were associated with worse outcomes in models adjusted for clinical variables, including LVEF and N-terminal pro-B-type natriuretic peptide (hazard ratio 2.48, 95% confidence interval 1.88-3.17 and 1.93, 1.48-2.52, respectively), while G-ID or ferritin <100 or <300 ng/ml were not.
Conclusion:
In HF outpatients, TSAT <20% is more consistently associated with congestion by ultrasound and poorer functional capacity than other ID definitions, irrespective of LVEF. TSAT <20% and iron ≤13 μmol/L, but not G-ID or ferritin-based ID, predict a worse prognosis in HF outpatients with preserved and reduced LVEF.
More Related Videos


Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:17
Pathophysiology of Heart Failure
 01:29
Pathophysiology of Cardiac Performance
 01:21
Myocarditis I: Introduction
 01:20
Rheumatic Heart Disease IV: Nursing Management
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...