Related Experiment Video
Updated: Jun 6, 2025


3D-Neuronavigation In Vivo Through a Patient's Brain During a Spontaneous Migraine Headache
Published on: June 2, 2014
Spinal manipulations for migraine: an updated systematic review and meta-analysis of randomized clinical trials
Pawel Posadzki1,2, Andrzej T Klimek3, Edzard Ernst4
1Faculty of Rehabilitation, University of Physical Education in Kraków, Kraków, Poland. pawel.posadzki@awf.krakow.pl.

Objective:
This update of a systematic review evaluates the effectiveness of spinal manipulations as a treatment for migraine headaches.
Background:
Spinal manipulation therapy (SMT) is sometimes used to treat migraine headaches; however, the biological plausibility and safety of SMT have repeatedly been questioned.
Methods:
Amed, Embase, MEDLINE, CINAHL, Mantis, Index to Chiropractic Literature, and Cochrane Central were searched from inception to September 2023. Randomized clinical trials (RCTs) investigating spinal manipulations (performed by various healthcare professionals including physiotherapists, osteopaths, and chiropractors) for treating migraine headaches in human subjects were considered. Other types of manipulative therapy, i.e., cranial, visceral, and soft tissue were excluded. The Grading of Recommendations Assessment, Development, and Evaluation (GRADE) approach was used to evaluate the certainty of evidence.
Results:
Three more RCTs were published since our first review; amounting to a total of 6 studies with 645 migraineurs meeting the inclusion criteria. Meta-analysis of six trials showed that, compared with various controls (placebo, drug therapy, usual care), SMT (with or without usual care) has no effect on migraine intensity/severity measured with a range of instruments (standardized mean difference [SMD] - 0.22, 95% confidence intervals [CI] - 0.65 to 0.21, very low certainty evidence), migraine duration (SMD - 0.10; 95% CI - 0.33 to 0.12, 4 trials, low certainty evidence), or emotional quality of life (SMD - 14.47; 95% CI - 31.59 to 2.66, 2 trials, low certainty evidence) at post-intervention. A meta-analysis of two trials showed that compared with various controls, SMT (with or without usual care) increased the risk of AEs (risk ratio [RR] 2.06; 95% CI 1.24 to 3.41, numbers needed to harm = 6; very low certainty evidence). The main reasons for downgrading the evidence were study limitations (studies judged to be at an unclear or high risk of bias), inconsistency (for pain intensity/severity), imprecision (small sizes and wide confidence intervals around effect estimates) and indirectness (methodological and clinical heterogeneity of populations, interventions, and comparators).
Conclusions:
The effectiveness of SMT for the treatment of migraines remains unproven. Future, larger, more rigorous, and independently conducted studies might reduce the existing uncertainties.

Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...
 01:24
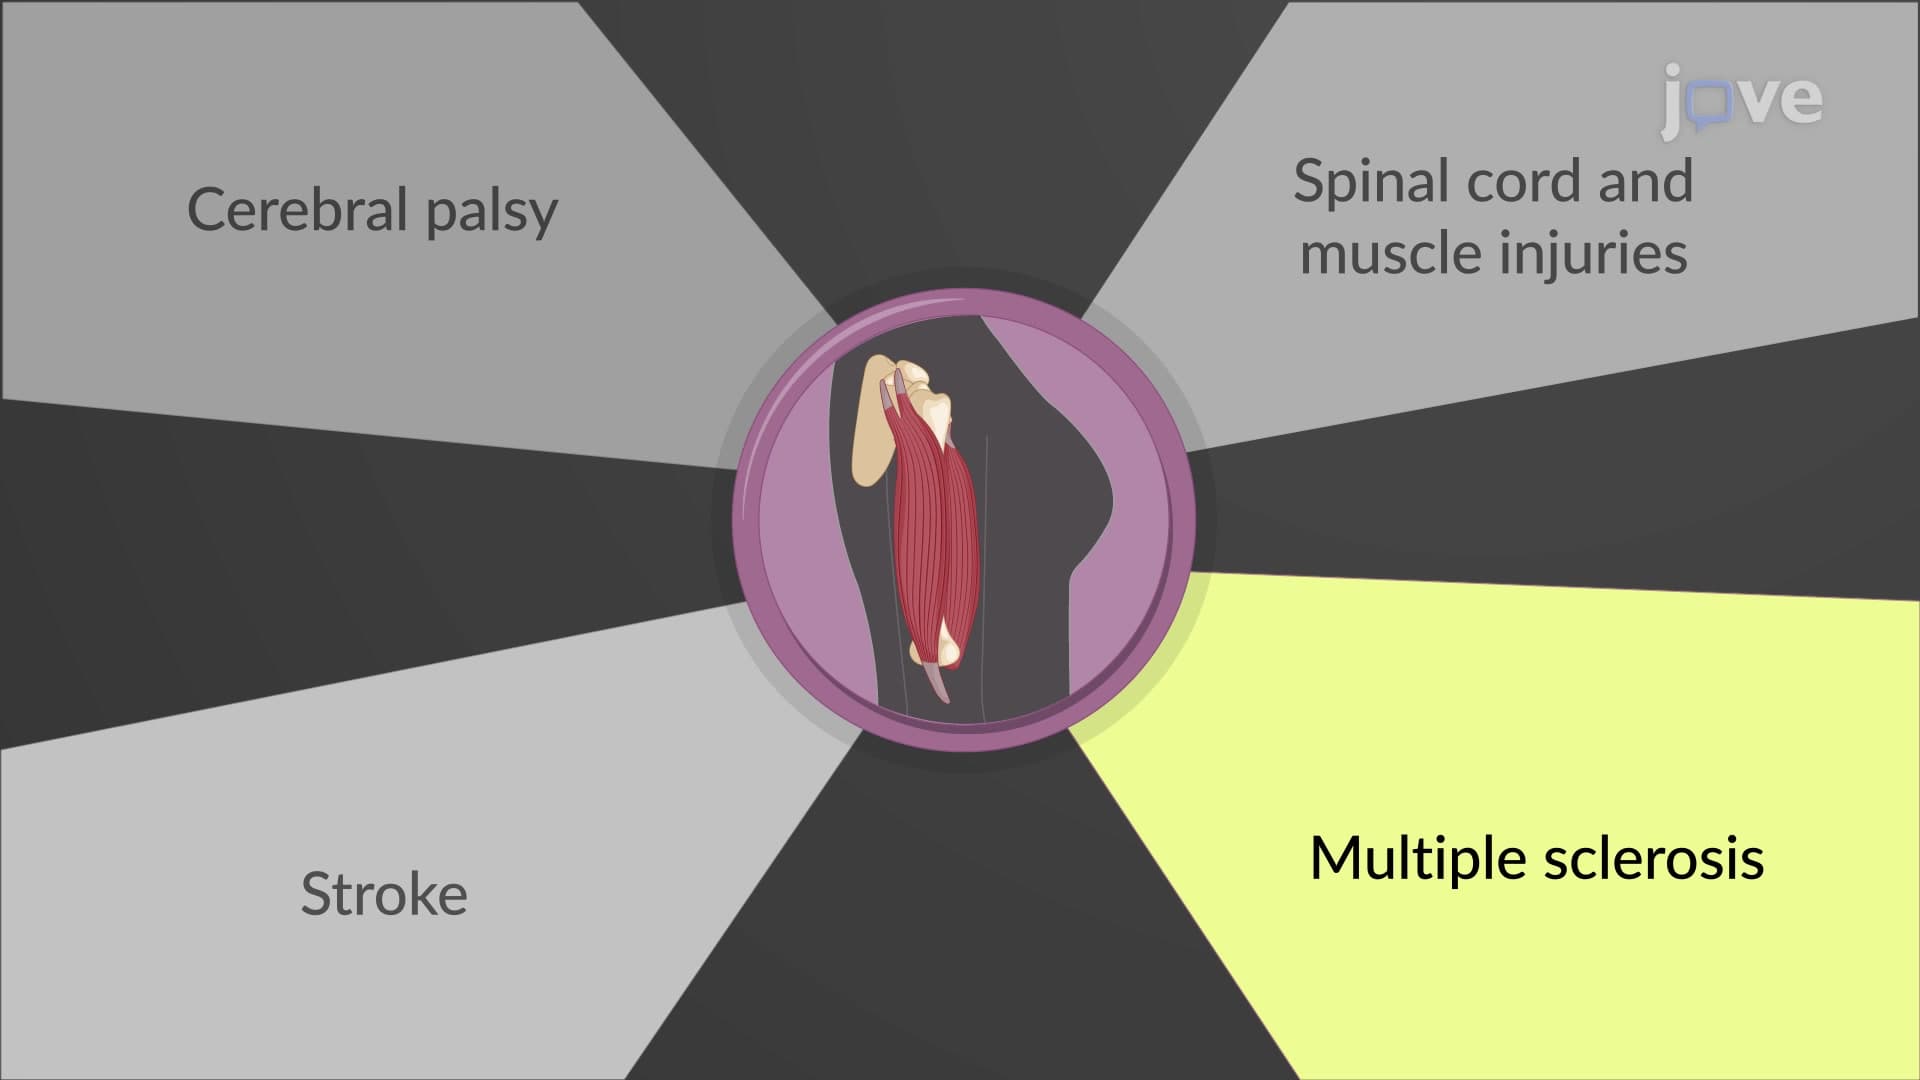
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:26
Cholinergic Antagonists: Therapeutic Uses
Respiratory Tract: Ipratropium, aclidinium, and tiotropium treat asthma, chronic bronchitis, and chronic obstructive pulmonary disease (COPD). They protect against bronchoconstriction caused by irritants like cigarette smoke, sulfur dioxide, and ozone. They also help reduce nasopharyngeal...