
Open Reduction and Internal Fixation of Distal Radius Fractures with Complete Intra-articular Involvement and
Chi-Hoon Oh1, Inseok Jang1, Cheungsoo Ha1
1Department of Orthopedic surgery, CHA Bundang Medical Center, CHA University School of Medicine, Seongnam, Korea.

Backgroud:
Distal radius fractures with complete intra-articular involvement and diaphyseal extension pose significant challenges for stable fixation. Treatment options vary, with no single method demonstrating superiority. This study analyzed the outcomes of fixing these type of fractures with volar locking plates, which are widely used worldwide, and the fracture length according to plate type to determine when an extra-long plate should be used.
Methods:
This retrospective review analyzed 89 consecutive patients surgically treated for Association of Osteosynthesis (AO) classification type C distal radius fractures with diaphyseal extension, excluding open fractures. The plate length was determined to be long enough accordingly to avoid placing screws in the fracture site. Radiographic evaluation and clinical outcomes were analyzed.
Results:
According to the AO system, C3 type fractures comprised 50%, C1 type 28%, and C2 type 22%. The average distance from the radiocarpal joint to the most proximal fracture line was 41.1 mm, with articular step off and gap of 1.7 mm and 3.7 mm, respectively. Concomitant distal ulna fractures were present in 81%. At final follow-up, the mean radial height was 10.9 mm, radial inclination was 22.8°, volar tilt was 5.7°, and ulnar variance was 0.6 mm. Fracture union occurred on average at 2.6 months. The average Disabilities of the Arm, Shoulder, and Hand score was 12.0 and the average Modified Mayo Wrist Score was 83.6. Regarding the average wrist range of motion, extension was 63.8°, flexion was 53.7°, ulnar deviation was 25.1°, and radial deviation was 16.7°. Complications included delayed wound healing in 3% and delayed union in 1 patient, who eventually achieved union at 10 months after surgery. APTUS Wrist Distal Radius Plates XL 2.5 and 2.4-mm Variable Angle LCP Two-Column Volar Distal Radius Plates showed a statistically significant difference in fracture length, with the former being longer than the latter (62 mm vs. 35 mm, p < 0.001).
Conclusions:
If the fracture length from the articular surface to the diaphysis exceeds 60 mm, we recommend preparing an extra-long distal radius plate. Volar plate fixation with appropriate length selection has yielded favorable functional outcomes and few minor complications in distal radius fractures with complete intra-articular involvement and diaphyseal extension.
More Related Videos
 08:20
A Reliable and Reproducible Critical-Sized Segmental Femoral Defect Model in Rats Stabilized with a Custom External Fixator
Published on: March 24, 2019
 05:34
A Mini-Invasive Internal Fixation Technique for Studying Immobilization-Induced Knee Flexion Contracture in Rats
Published on: May 20, 2019
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
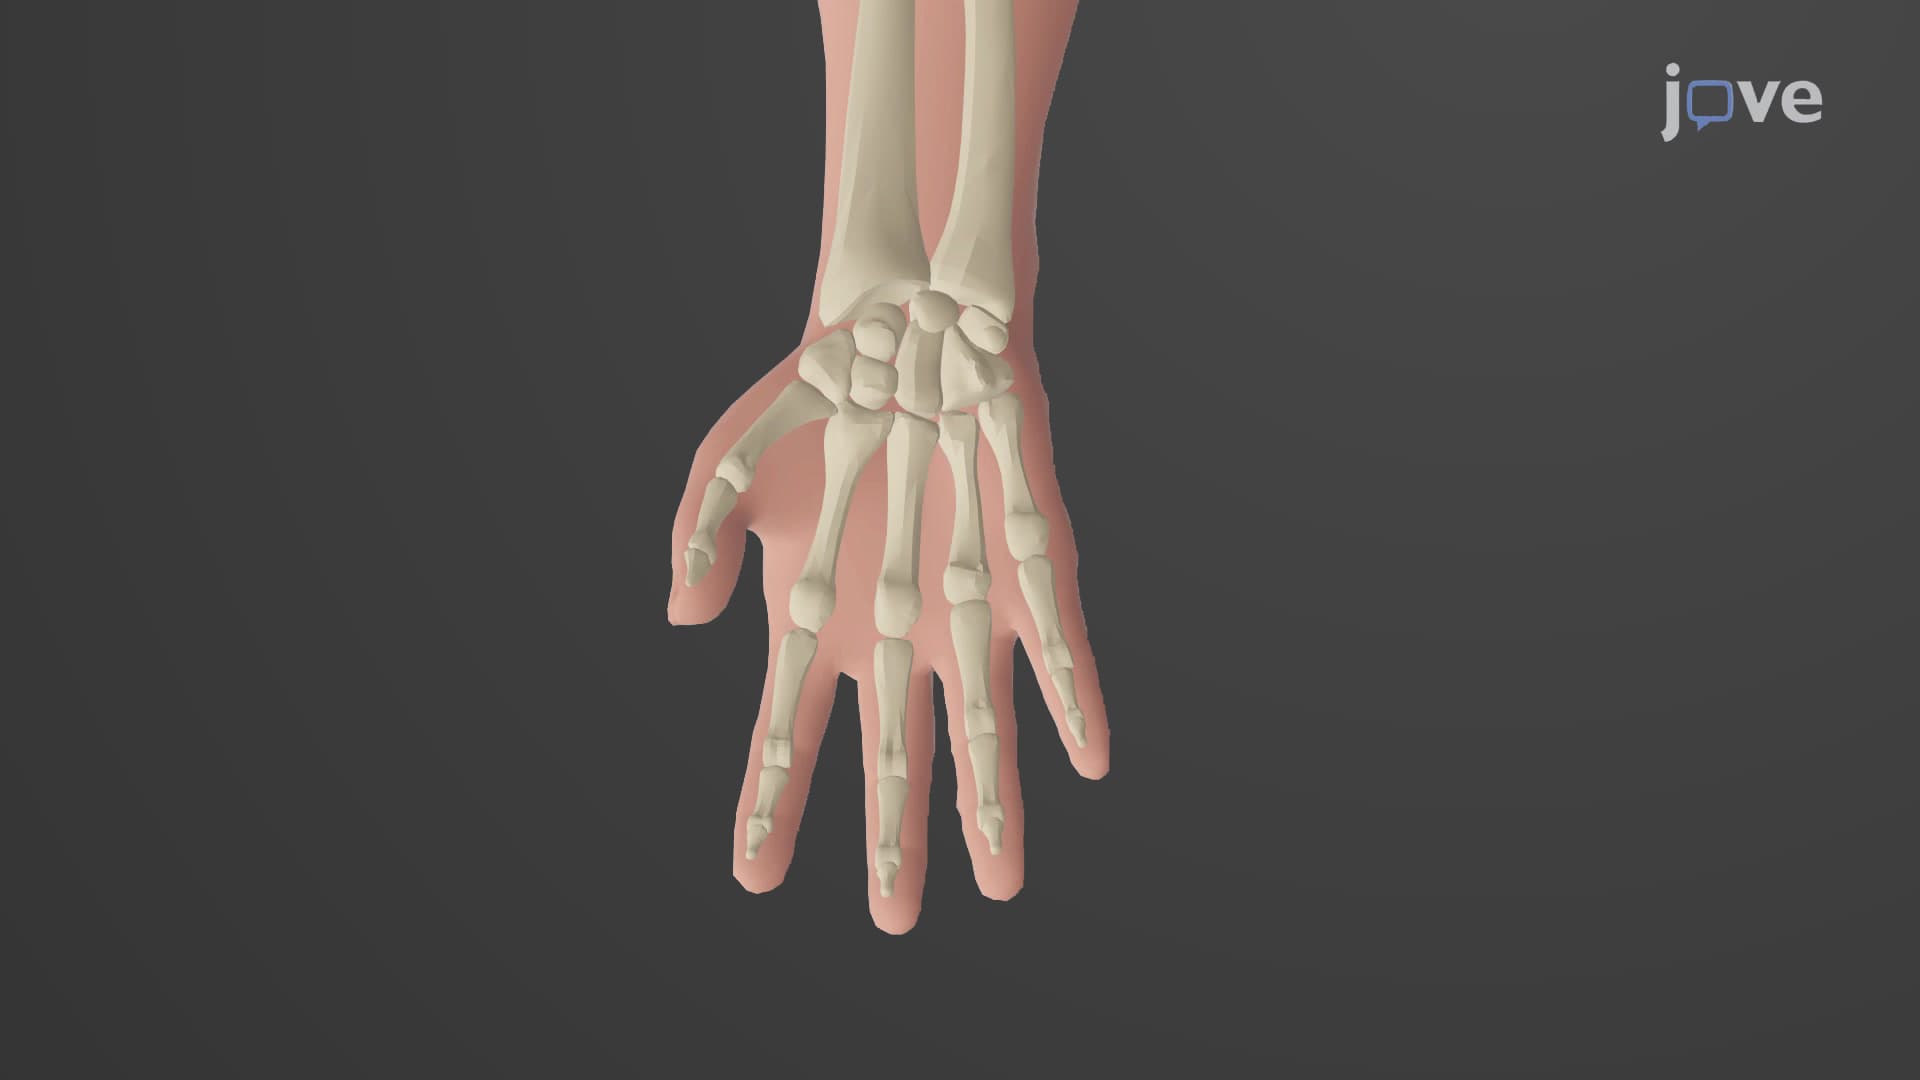
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...