Related Experiment Video
Updated: Jun 27, 2026
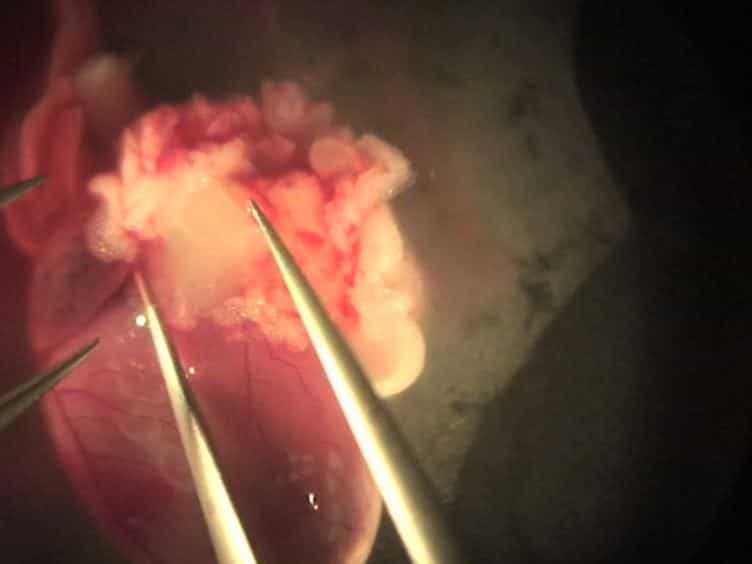

Isolation and Physiological Analysis of Mouse Cardiomyocytes
Published on: September 7, 2014
Mechanical loading reveals an intrinsic cardiomyocyte stiffness contribution to diastolic dysfunction in murine
Johannes V Janssens1,2, Antonia J A Raaijmakers1, Parisa Koutsifeli3
1Department of Anatomy & Physiology, University of Melbourne, Melbourne, Australia.

Insights
Cardiometabolic disease causes diastolic dysfunction due to increased cardiomyocyte stiffness. This stiffness, linked to calcium handling, impacts heart function and cannot be detected by unloaded shortening measurements.
Area of Science:
- Cardiology
- Physiology
- Biochemistry
Background:
- Cardiometabolic diseases like diabetes and obesity are linked to heart failure with diastolic dysfunction.
- Current treatments for diastolic dysfunction offer limited efficacy, highlighting the need for new therapeutic targets.
- Understanding the cellular mechanisms of diastolic dysfunction is crucial for developing novel treatments.
Purpose of the Study:
- To experimentally determine the in vitro stiffness properties of cardiomyocytes from rodent hearts with diet-induced cardiometabolic disease and diastolic dysfunction.
- To correlate in vitro cardiomyocyte stiffness with in vivo measures of diastolic dysfunction.
Main Methods:
- Male mice were fed a high-fat/sugar diet (HFSD) or control diet, and diastolic dysfunction was assessed via echocardiography (E/e' Doppler ratio).
- Isolated cardiomyocytes were functionally evaluated under non-loaded, loaded, and stretched conditions during pacing.
- Cardiomyocyte stiffness (stress/strain) was measured, along with sarcomere lengthening rate, Ca2+ transient decay, and diastolic Ca2+ levels.
Main Results:
- HFSD mice exhibited diastolic dysfunction (elevated E/e') and significantly higher cardiomyocyte stiffness (70% increase) compared to controls.
- A strong correlation was found between in vitro cardiomyocyte stiffness and in vivo diastolic dysfunction severity.
- HFSD cardiomyocytes showed more pronounced decrements in maximal sarcomere lengthening under load, prolonged Ca2+ transient decay with stretch, and attenuated diastolic Ca2+ elevation with increased pacing.
Conclusions:
- Cardiomyocyte stiffness is a significant contributor to diastolic dysfunction in cardiometabolic disease.
- Standard assessment of non-loaded cardiomyocyte shortening is insufficient to detect mechanical dysfunction.
- Altered myofilament-calcium interactions, particularly stretch-dependent responses, contribute to intrinsic cardiomyocyte stiffness and diastolic dysfunction in this disease model.
Abstract:
Cardiometabolic syndromes including diabetes and obesity are associated with occurrence of heart failure with diastolic dysfunction. There are no specific treatments for diastolic dysfunction, and therapies to manage symptoms have limited efficacy. Understanding of the cardiomyocyte origins of diastolic dysfunction is an important priority to identify new therapeutics. The investigative goal was to experimentally define in vitro stiffness properties of isolated cardiomyocytes derived from rodent hearts exhibiting diastolic dysfunction in vivo in response to dietary induction of cardiometabolic disease. Male mice fed a high fat/sugar diet (HFSD vs. control) exhibited diastolic dysfunction (echo E/e' Doppler ratio). Intact paced cardiomyocytes were functionally investigated in three conditions: non-loaded, loaded and stretched. Mean stiffness of HFSD cardiomyocytes was 70% higher than control. E/e' for the HFSD hearts was elevated by 35%. A significant relationship was identified between in vitro cardiomyocyte stiffness and in vivo dysfunction severity. With conversion from the non-loaded to loaded condition, the decrement in maximal sarcomere lengthening rate was more accentuated in HFSD cardiomyocytes (vs. control). With stretch, the Ca2+ transient decay time course was prolonged. With increased pacing, cardiomyocyte stiffness was elevated, yet diastolic Ca2+ elevation was attenuated. Our findings show unequivocally that cardiomyocyte mechanical dysfunction cannot be detected by analysis of non-loaded shortening. Collectively, these findings demonstrate that a component of cardiac diastolic dysfunction in cardiometabolic disease is derived from cardiomyocyte stiffness. Differential responses to load, stretch and pacing suggest that a previously undescribed alteration in myofilament-Ca2+ interaction contributes to intrinsic cardiomyocyte stiffness in cardiometabolic disease. KEY POINTS: Understanding cardiomyocyte stiffness components is an important priority for identifying new therapeutics for diastolic dysfunction, a key feature of cardiometabolic disease. In this study cardiac function was measured in vivo (echocardiography) for mice fed a high-fat/sugar diet (HFSD, ≥25 weeks). Performance of intact isolated cardiomyocytes derived from the same hearts was measured during pacing under non-loaded, loaded and stretched conditions in vitro. Calibrated cardiomyocyte stretches demonstrated that stiffness (stress/strain) was elevated in HFSD cardiomyocytes in vitro and correlated with diastolic dysfunction (E/e') in vivo. HFSD cardiomyocyte Ca2+ transient decay was prolonged in response to stretch. Stiffness was accentuated with pacing increase while the elevation in diastolic Ca2+ was attenuated. Data show unequivocally that cardiomyocyte mechanical dysfunction cannot be detected by analysis of non-loaded shortening. These findings suggest that stretch-dependent augmentation of the myofilament-Ca2+ response during diastole partially underlies elevated cardiomyocyte stiffness and diastolic dysfunction of hearts of animals with cardiometabolic disease.


