Related Experiment Video
Updated: Jun 5, 2025
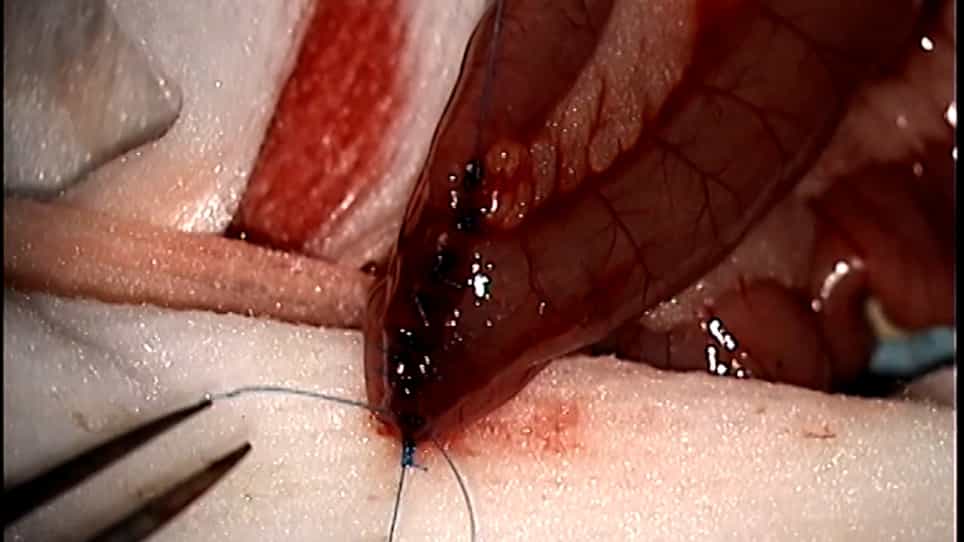

A Protocol for Roux-en-Y Gastric Bypass in Rats using Linear Staplers
Published on: August 21, 2021
Surgical management of candy cane syndrome after Roux-en-Y bypass
Nafiye Busra Celik1, Jorge Cornejo1, Lorna A Evans1
1Department of Surgery, Mayo Clinic Florida, Jacksonville, Florida.

Background:
Candy cane (CC) syndrome is a complication that occurs following Roux-en-Y bypass (RYGB), implicated as a long, small-bowel blind limb at gastrojejunostomy possibly caused using circular staplers.
Objectives:
We aimed to report our experience with CC resection and improving outcomes following RYGB.
Setting:
University hospital.
Methods:
We performed a retrospective analysis of patients who underwent CC resection at our institution from 2017 to 2023. Patient's charts were then reviewed to evaluate for symptoms, operative, and weight data. Only patients with an afferent blind limb in the most direct outlet from the gastroesophageal junction (GJ) visualized in upper gastrointestinal (GI) study and endoscopy were included.
Results:
Twenty-nine patients had presented with symptoms of and underwent surgery of resection of the CC (83% female; 50.3 ± 12.9 years) within 11 ± 6 years after initial RYGB. In addition, 58.6% underwent a concomitant procedure (10 hiatal hernia repair, 4 revision gastrojejunostomy, and 3 internal hernia reduction and defect closure). The mean length of the CC was 7.5 ± 3.9 cm. Resection of CC was performed in 62.1% as stapling only, 34.5% as stapling and oversewing, and 3.4% as oversewing only. The 30-day hospital readmission rate was 7.4% (n = 2). At 8.5-month follow-up, there was a significant reduction (P < .005) of bloating, nausea or vomiting, and dysphagia; however, abdominal pain and diarrhea slightly decreased. The estimated weight loss percentage was 29.4% ± 5.6%, and body mass index decreased from 32.1 ± 7.3 kg/m2 to 29.1 ± 4.7 kg/m2.
Conclusions:
Resection of blind afferent limb can be managed safely with excellent outcomes and resolution of symptoms, even if major procedures are performed concomitantly. Surgeons should resect excess Roux limb in the initial RYGB to decrease the likelihood of this syndrome.


Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: