Related Experiment Video
Updated: Jun 22, 2026
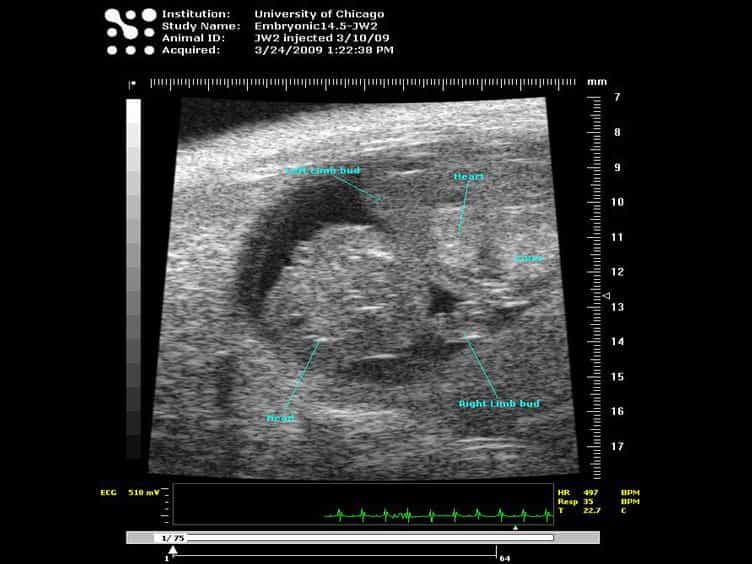
Murine Fetal Echocardiography
Published on: February 15, 2013
Fetal death: Expert consensus of the French College of Obstetricians and Gynecologists
Charles Garabedian1, Jeanne Sibiude2, Olivia Anselem3
1CHU Lille, Clinique d'Obstétrique, Lille, France.

Fetal death is defined as the spontaneous cessation of cardiac activity after 14 weeks gestational age (GA). Regarding prevention of fetal death in the general population, it is not recommended to counsel or prescribe rest, aspirin, vitamin A, vitamin D, or micronutrient supplementation; systematically look for nuchal cord during prenatal screening ultrasound; or perform systematic antepartum monitoring by cardiotocography for the sole purpose of reducing the risk of fetal death. It is recommended to offer vaccination against influenza in epidemic periods and against SARS-CoV-2. Regarding evaluation in the event of fetal death, it is recommended that a fetal autopsy and anatomopathologic examination of the placenta be performed; chromosomal analysis be performed by microarray testing, rather than by conventional karyotype (with postnatal sampling of the fetal placental surface preferred for genetic purposes); testing for antiphospholipid antibodies be performed, with systematic Kleihauer-Betke testing and for irregular agglutinins; and summary consultation to discuss these examination results be offered. Regarding announcement and support, it is recommended that fetal death be announced without ambiguity, using simple words adapted to each situation, after which the couple should be supported with empathy across the different stages of their care. Regarding patient management in cases of fetal death, it is recommended that: in the absence of risks for disseminated intravascular coagulation or maternal demise, the patient's wishes regarding the timing between the fetal death diagnosis and labor induction should be considered; return home is possible, according to the patient's wishes; in all situations except maternal life-threatening emergencies, the preferred mode of delivery is vaginal, regardless of previous cesarean section(s); mifepristone 200 mg be prescribed at least 24 h before induction; and perimedullary analgesia be initiated at the start of induction if requested by the patient, regardless of GA. Of note, there is insufficient evidence to recommend either the administration route (i.e., vaginal or oral) of misoprostol or prostaglandin type. Regarding the risk of recurrence after unexplained fetal death: the incidence does not appear to be increased in subsequent pregnancies; in cases with a history of fetal death due to vascular problems, low-dose aspirin is recommended to reduce perinatal morbidity (otherwise, evidence is insufficient to recommend the prescription of aspirin); no optimal delay in initiating another pregnancy should be recommended based solely on a history of fetal death; fetal heart rate monitoring is not indicated based solely on a history of fetal death; although systematic labor induction is not recommended, induction may be considered depending on the context and parental request, and considering fetal age, benefits, and risks, especially before 39 weeks GA. Note that if the cause of fetal death is identified, management should be adjusted on a case-by-case basis. Regarding fetal death in a twin pregnancy, it is recommended that the surviving twin be examined immediately upon fetal death diagnosis; in a dichorionic twin pregnancy, preterm delivery induction is not recommended; in a monochorionic twin pregnancy, the surviving twin should be immediately evaluated for signs of acute fetal anemia, with weekly ultrasound monitoring for the first month, though immediate labor induction is not recommended.
Fetal death is defined as the spontaneous cessation of cardiac activity after 14 weeks gestational age (GA). Regarding prevention of fetal death in the general population, it is not recommended to counsel or prescribe rest, aspirin, vitamin A, vitamin D, or micronutrient supplementation; systematically look for nuchal cord during prenatal screening ultrasound; or perform systematic antepartum monitoring by cardiotocography for the sole purpose of reducing the risk of fetal death. It is recommended to offer vaccination against influenza in epidemic periods and against SARS-CoV-2. Regarding evaluation in the event of fetal death, it is recommended that a fetal autopsy and anatomopathologic examination of the placenta be performed; chromosomal analysis be performed by microarray testing, rather than by conventional karyotype (with postnatal sampling of the fetal placental surface preferred for genetic purposes); testing for antiphospholipid antibodies be performed, with systematic Kleihauer-Betke testing and for irregular agglutinins; and summary consultation to discuss these examination results be offered. Regarding announcement and support, it is recommended that fetal death be announced without ambiguity, using simple words adapted to each situation, after which the couple should be supported with empathy across the different stages of their care. Regarding patient management in cases of fetal death, it is recommended that: in the absence of risks for disseminated intravascular coagulation or maternal demise, the patient's wishes regarding the timing between the fetal death diagnosis and labor induction should be considered; return home is possible, according to the patient's wishes; in all situations except maternal life-threatening emergencies, the preferred mode of delivery is vaginal, regardless of previous cesarean section(s); mifepristone 200 mg be prescribed at least 24 h before induction; and perimedullary analgesia be initiated at the start of induction if requested by the patient, regardless of GA. Of note, there is insufficient evidence to recommend either the administration route (i.e., vaginal or oral) of misoprostol or prostaglandin type. Regarding the risk of recurrence after unexplained fetal death: the incidence does not appear to be increased in subsequent pregnancies; in cases with a history of fetal death due to vascular problems, low-dose aspirin is recommended to reduce perinatal morbidity (otherwise, evidence is insufficient to recommend the prescription of aspirin); no optimal delay in initiating another pregnancy should be recommended based solely on a history of fetal death; fetal heart rate monitoring is not indicated based solely on a history of fetal death; although systematic labor induction is not recommended, induction may be considered depending on the context and parental request, and considering fetal age, benefits, and risks, especially before 39 weeks GA. Note that if the cause of fetal death is identified, management should be adjusted on a case-by-case basis. Regarding fetal death in a twin pregnancy, it is recommended that the surviving twin be examined immediately upon fetal death diagnosis; in a dichorionic twin pregnancy, preterm delivery induction is not recommended; in a monochorionic twin pregnancy, the surviving twin should be immediately evaluated for signs of acute fetal anemia, with weekly ultrasound monitoring for the first month, though immediate labor induction is not recommended.
More Related Videos
 07:34
Fetal Mouse Cardiovascular Imaging Using a High-frequency Ultrasound 30/45MHZ System
Published on: May 5, 2018
 05:50
International Expert Consensus and Recommendations for Neonatal Pneumothorax Ultrasound Diagnosis and Ultrasound-guided Thoracentesis Procedure
Published on: March 12, 2020
Related Concept Videos
 01:38
Fertilization
 01:30
Overview of Cell Death
Cell death was observed in the early 19th century, but there was no experimental evidence to prove it. In 1842, Carl Vogt first discovered cell death in a metamorphic toad; however, it was not termed ‘cell death.’ Scientists discovered different cell death pathways only in the 20th century...
 01:07
Teratogenicity
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:15
Development of the Sexual Organs in the Embryo and Fetus
Near the gonadal ridges, two duct systems are present: the mesonephric ducts (Wolffian ducts) and paramesonephric ducts (Müllerian ducts). These ducts form the basis for the male...