Related Experiment Video
Updated: Jun 5, 2025


Intravascular Delivery of Biologics to the Rat Kidney
Published on: September 1, 2016
Ex vivo assessment of sulbactam-durlobactam clearance during continuous renal replacement therapy to guide dosing
Yasmeen Abouelhassan1, Yuwei Shen1, April Chen2
1Center for Anti-Infective Research and Development, Hartford Hospital, Hartford, Connecticut, USA.

Abstract:
Sulbactam-durlobactam is approved for the treatment of hospital-acquired and ventilator-associated bacterial pneumonia caused by susceptible isolates of Acinetobacter baumannii-calcoaceticus complex. Patients with serious Acinetobacter infections may require support with continuous renal replacement therapy (CRRT), which presents challenges for optimal dosing of antibiotics. Sulbactam-durlobactam dosing regimens were derived for this population using an ex vivo CRRT model and Monte Carlo simulation (MCS). Transmembrane clearance (CLTM) was determined in hemofiltration (CVVH) and hemodialysis (CVVHD) modes using the Prismaflex M100 and HF1400 hemofilter sets and with effluent rates of 1, 2, and 3 L/h. Pre-filter, post-filter blood, and effluent samples were collected over 60 min to calculate sieving (SC) and saturation (SA) coefficients for CVVH and CVVHD, respectively. An established population pharmacokinetic model was integrated with the CLTM; then, a 1,000 patient MCS was conducted to determine exposures of potential dosing regimens. Adsorption and degradation in the ex vivo CRRT model were negligible. The overall mean ± standard deviation SC/SA was 1.14 ± 0.12 and 0.93 ± 0.08 for sulbactam and durlobactam, respectively. In multivariable regression analyses, effluent rate was the primary driver of CLTM for both drugs. For effluent rates <3 L/h, sulbactam-durlobactam 1 g-1g q8h as 3 h infusion achieved a high probability of pharmacodynamic target attainment while retaining area under the curve exposures consistent with the standard dose in non-CRRT patients. For effluent rates ≥3 to 5 L/h, the optimal regimen was 1 g-1g q6h 3 h infusion. Sulbactam-durlobactam regimens that provide optimum drug exposures for efficacy and safety were identified for CRRT based on the prescribed effluent rate.
Insights
Optimized sulbactam-durlobactam dosing for patients on continuous renal replacement therapy (CRRT) was determined. New regimens ensure effective treatment of Acinetobacter infections during CRRT, balancing efficacy and safety.
Area of Science:
- Pharmacokinetics and Pharmacodynamics
- Infectious Diseases
- Nephrology
Background:
- Sulbactam-durlobactam is indicated for hospital-acquired and ventilator-associated bacterial pneumonia caused by Acinetobacter baumannii-calcoaceticus complex.
- Continuous renal replacement therapy (CRRT) in critically ill patients presents challenges for optimal antibiotic dosing.
- Acinetobacter infections often require CRRT support, necessitating specific dosing strategies for sulbactam-durlobactam.
Purpose of the Study:
- To determine optimal sulbactam-durlobactam dosing regimens for patients undergoing CRRT.
- To evaluate the impact of CRRT parameters on drug clearance and patient exposure.
- To ensure therapeutic efficacy and safety of sulbactam-durlobactam in CRRT patients.
Main Methods:
- An ex vivo CRRT model (hemofiltration and hemodialysis modes) was used to determine transmembrane clearance (CLTM).
- Population pharmacokinetic modeling and Monte Carlo simulations (MCS) were integrated with CLTM data.
- Drug adsorption and degradation were assessed; sieving (SC) and saturation (SA) coefficients were calculated.
Main Results:
- Adsorption and degradation of sulbactam-durlobactam in the CRRT model were negligible.
- Effluent rate was the primary determinant of CLTM for both drugs.
- Recommended regimens: 1g-1g q8h (3h infusion) for effluent rates <3 L/h, and 1g-1g q6h (3h infusion) for effluent rates ≥3 to 5 L/h.
Conclusions:
- Established sulbactam-durlobactam dosing regimens provide optimal drug exposures for efficacy and safety in CRRT patients.
- Dosing adjustments are guided by the prescribed effluent rate during CRRT.
- These findings support effective management of Acinetobacter infections in patients requiring CRRT.
Related Concept Videos
 01:06
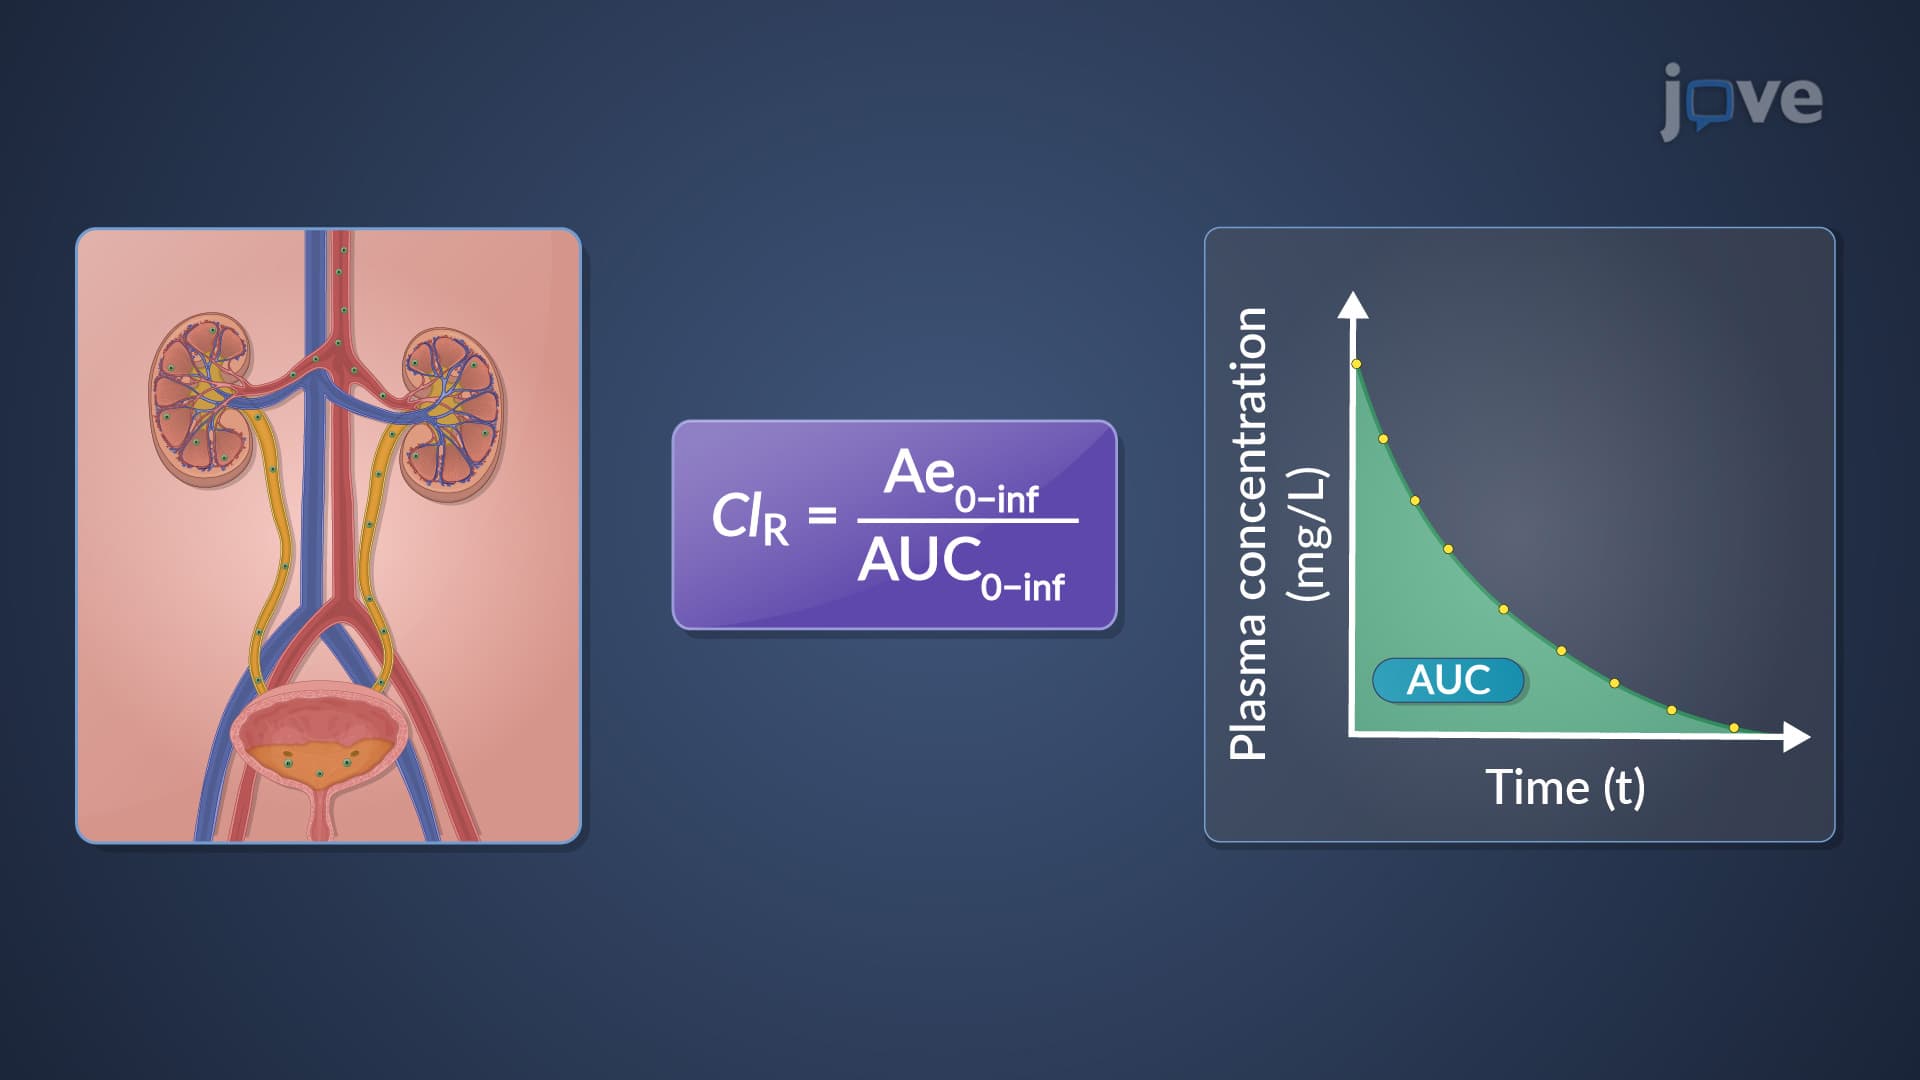
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:08
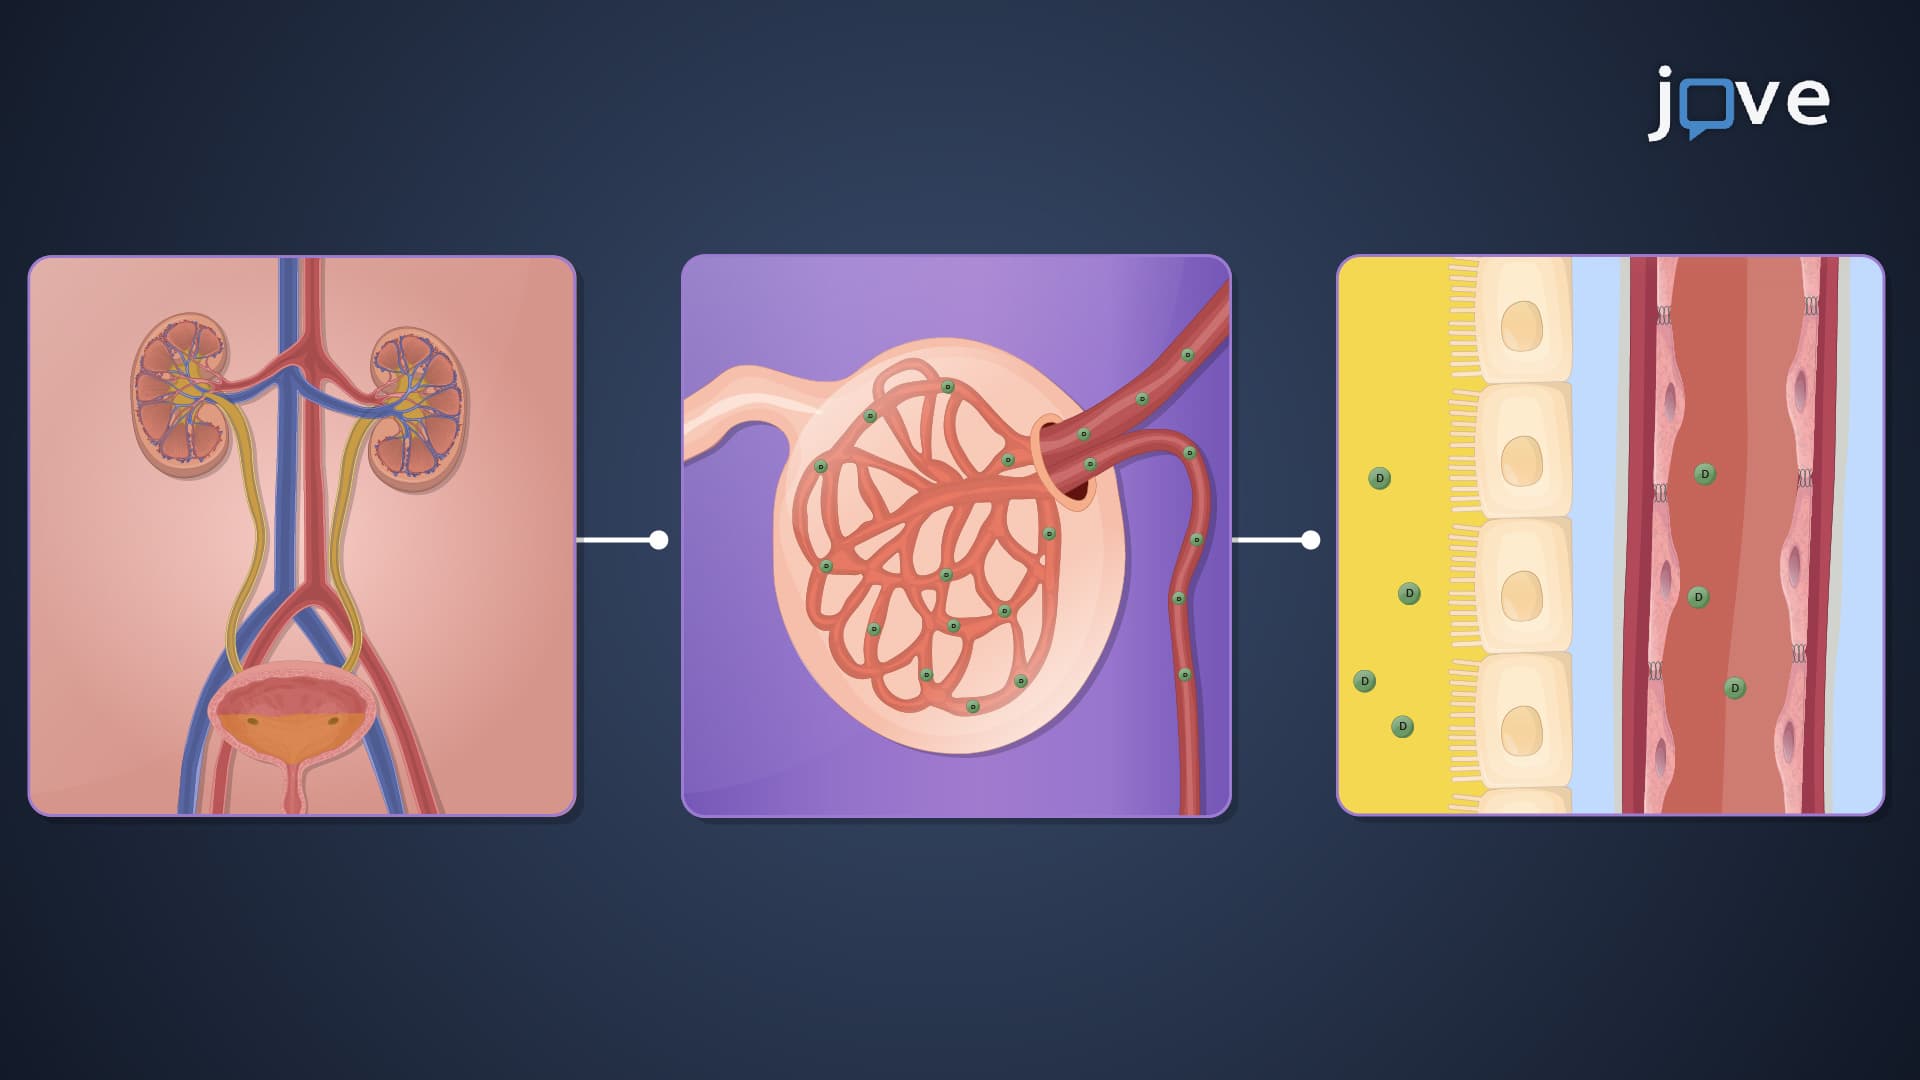
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:11
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...