Related Experiment Video
Updated: Jun 4, 2025
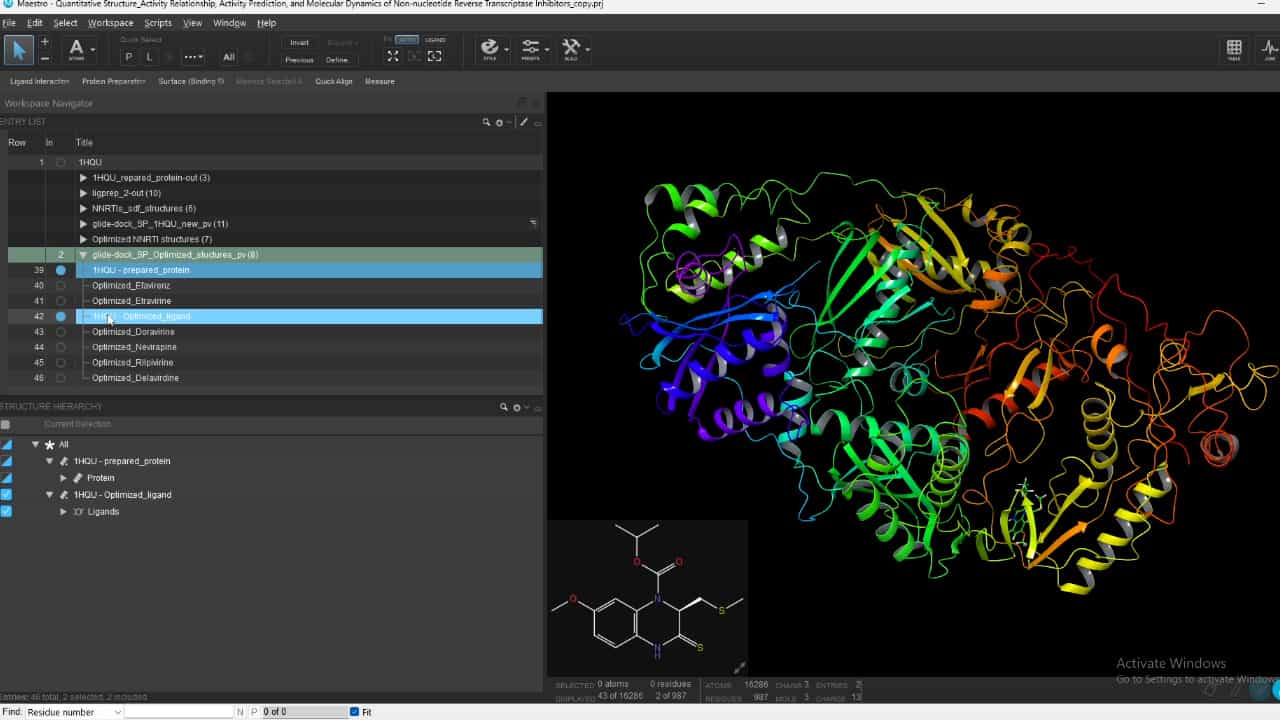
Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Independent FDA Analyses of Nirmatrelvir/Ritonavir Resistance in the Phase 2/3 Trials EPIC-HR and EPIC-SR
Jonathan M O Rawson1, Eric F Donaldson1, Julian J O'Rear1
1Division of Antivirals, Office of Infectious Diseases, Center for Drug Evaluation and Research, Food and Drug Administration, Silver Spring, Maryland, USA.

Background:
PAXLOVID consists of nirmatrelvir, an inhibitor of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) main protease (Mpro), copackaged with ritonavir, a pharmacokinetic enhancer. Nirmatrelvir/ritonavir received emergency use authorization in the United States in 2021 and was approved in 2023. However, there is limited published information on SARS-CoV-2 clinical resistance to nirmatrelvir/ritonavir.
Methods:
To investigate SARS-CoV-2 resistance development to nirmatrelvir/ritonavir in treated patients, we analyzed baseline and matching post-baseline SARS-CoV-2 next-generation sequencing data from 1862 participants (912 nirmatrelvir/ritonavir, 950 placebo) in Evaluation of Protease Inhibition for COVID-19 in High-Risk Patients (EPIC-HR) and Evaluation of Protease Inhibition for COVID-19 in Standard-Risk Patients (EPIC-SR), which were Phase 2/3, randomized, double-blind, placebo-controlled trials in participants with mild-to-moderate coronavirus disease 2019 (COVID-19). Potential resistance-associated substitutions (RAS) were defined as those that were enriched in nirmatrelvir/ritonavir-treated participants or occurred at Mpro positions of interest, defined using nonclinical data. SARS-CoV-2 sequence databases were analyzed to characterize temporal frequencies of nirmatrelvir/ritonavir RAS in circulating viruses.
Results:
In EPIC-HR, nirmatrelvir/ritonavir RAS included Mpro T21I (n = 1), E166V (n = 3), A173T (n = 1), and T304I (n = 1), with E166V being the clearest RAS observed. In EPIC-SR, no RAS were detected. Nirmatrelvir/ritonavir RAS were not associated with hospitalization or death. Analyses of SARS-CoV-2 sequence databases did not reveal concerning increases in the frequencies of nirmatrelvir/ritonavir RAS over time.
Conclusions:
In clinical trials, emergence of SARS-CoV-2 resistance to nirmatrelvir/ritonavir was infrequent (<0.3%-1.1%). Surveillance data currently indicate a low frequency of circulating SARS-CoV-2 variants with nirmatrelvir/ritonavir RAS. Collectively, these results provide the most comprehensive analysis of SARS-CoV-2 resistance to nirmatrelvir/ritonavir in the clinical setting to date. Viral sequences should continue to be closely monitored to identify the potential emergence of nirmatrelvir/ritonavir-resistant variants.