Related Experiment Video
Updated: Jun 4, 2025

Metacarpal Small Incision for Carpal Tunnel Syndrome
Published on: April 5, 2024
Revision Carpal Tunnel Release with Endoscopic Technique: Clinical Outcomes and Intraoperative Findings
Patricia K Wellborn1, Alexander D Jeffs2, Andrew D Allen2
1Department of Orthopaedics, University of North Carolina, Chapel Hill, NC; Department of Orthopaedics, University of Colorado, Aurora, CO.

Purpose:
The standard treatment for recurrent carpal tunnel syndrome (CTS) has been open revision. We hypothesize that endoscopic carpal tunnel release can be used successfully in the revision setting.
Methods:
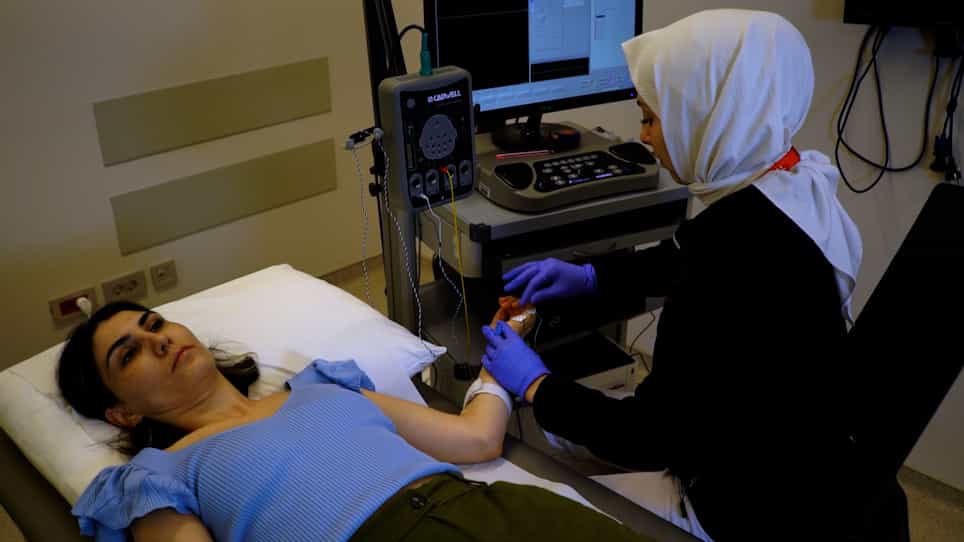
We identified patients between 2018-2023 who underwent revision carpal tunnel release (CTR). All patients underwent prior open or mini-open CTR (OCTR). All had electrodiagnostically proven CTS and CTS-6 scores >12. Those with suspected or documented nerve injury after primary CTR were excluded. Patient-reported outcomes, including visual analog scale pain scores and 5-point Likert-style rating of symptom improvement, were collected.
Results:
Thirty patients were identified: 22 with recurrent and 8 with persistent CTS. Average time from index surgery was 110 months in recurrent and 18 months in persistent CTS cases. Twenty-five patients had prior mini-open CTR, and five underwent traditional-open CTR. Intraoperative findings included incomplete release (n = 4), median nerve (MN) adhesions to skin (n = 1) or flexor retinaculum (n = 4), inadequate visualization of the MN (n = 5) and no documented findings (n = 17). Five of 30 patients (16%) were converted from endoscopic to open release procedures intraoperatively. All conversions occurred in patients with prior traditional-open CTR and incisions crossing the wrist flexion crease. At 6-month follow-up, average visual analog pain scores improved from 7 to 2 after revision endoscopic release and from 7 to 3 in cases in which conversion from endoscopic to open release was required. Of the patients, 92% in the revision endoscopic group and 60% in the conversion group had symptom improvement (5-point Likert score ≥3 at final follow-up).
Conclusions:
Revision endoscopic carpal tunnel release can be performed successfully after primary mini-open CTR. A prior traditional OCTR with an incision crossing the wrist crease is more likely to require conversion to open release. A lower proportion of patients converted to OCTR have postoperative symptom improvement than those treated with revision endoscopic release.
Type Of Study/Level Of Evidence:
Therapeutic IV.