Association between glottis screen location and intubation difficulty: a retrospective video laryngoscopy study
Related Experiment Video
Updated: Jun 4, 2025
The Rigid Tube as an Alternative in Controlling the Problematic Airway
Published on: June 6, 2020
Kai-Yuan Cheng1, Pang Hsu Liu1, Yung-Cheng Su1
1Department of Emergency Medicine, Ditmanson Medical Foundation Chia-Yi Christian Hospital, No. 539, Zhongxiao Road, East District, Chiayi City, 600, Taiwan.

Background:
In emergency settings, difficult intubations often occur unexpectedly despite pre-intubation assessments. Traditional glottic view scoring systems for direct laryngoscope may not apply to video laryngoscopy. With video laryngoscopy, the vertical location of the glottis on the monitor can be clearly defined. If the glottis location is associated with intubation difficulty, it could serve as a simple indicator for anticipating intubation challenges. This study aimed to investigate the relationship between the glottis screen location during video laryngoscopy-guided intubation and the success and timing of the first-attempt intubation.
Methods:
We retrospectively analyzed laryngoscopy recordings from adult intubations in the emergency department of a tertiary teaching hospital in Chiayi, Taiwan, using the C-MAC video laryngoscope between March 2020 and April 2023. The vertical screen location of the vocal cords, determined by the arytenoid cartilage position after laryngeal blade engagement, was categorized into upper and lower locations for analysis. The primary outcome was first-attempt intubation success within 90 s, analyzed using Kaplan-Meier survival curves and multivariable Cox proportional hazard analysis.
Results:
Among 209 laryngoscopy records, 113 had the arytenoid in the lower field of view and 96 in the upper field. Kaplan-Meier analysis showed a significantly lower cumulative success rate for intubations with a higher arytenoid location (log-rank test, P < 0.001). Multivariable Cox models, adjusted for factors like modified Cormack-Lehane grade, blade tip engagement, and other intubation findings, confirmed the arytenoid's location as an independent predictor of successful intubation within 90 s, with an adjusted hazard ratio of 0.55 (95% confidence interval, 0.38-0.79) for the upper location group compared to the lower (P < 0.001).
Conclusions:
A higher screen location of the vocal cords after blade engagement is associated with reduced first-attempt intubation success. Assessing glottis location during video laryngoscopy intubation provides a quick method to anticipate intubation challenges.
Related Concept Videos
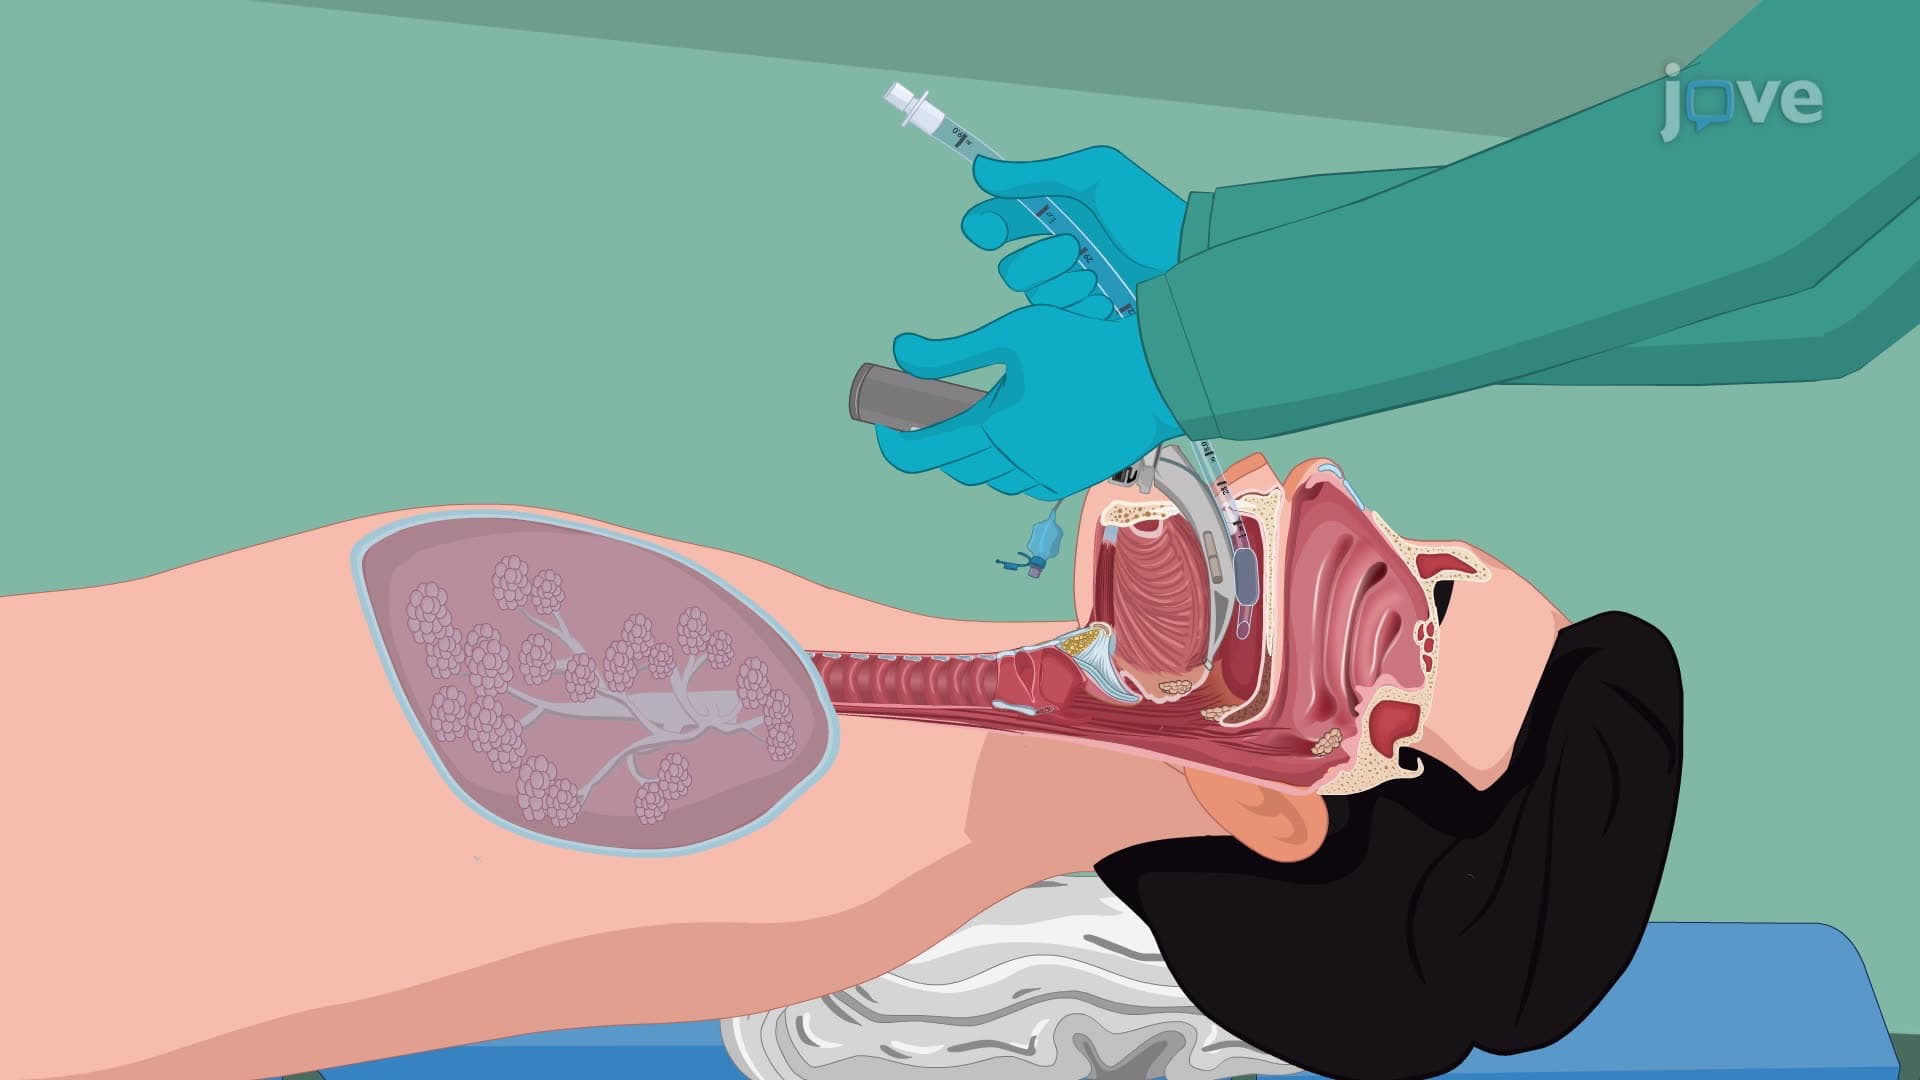 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...