Related Experiment Video
Updated: Jun 4, 2025
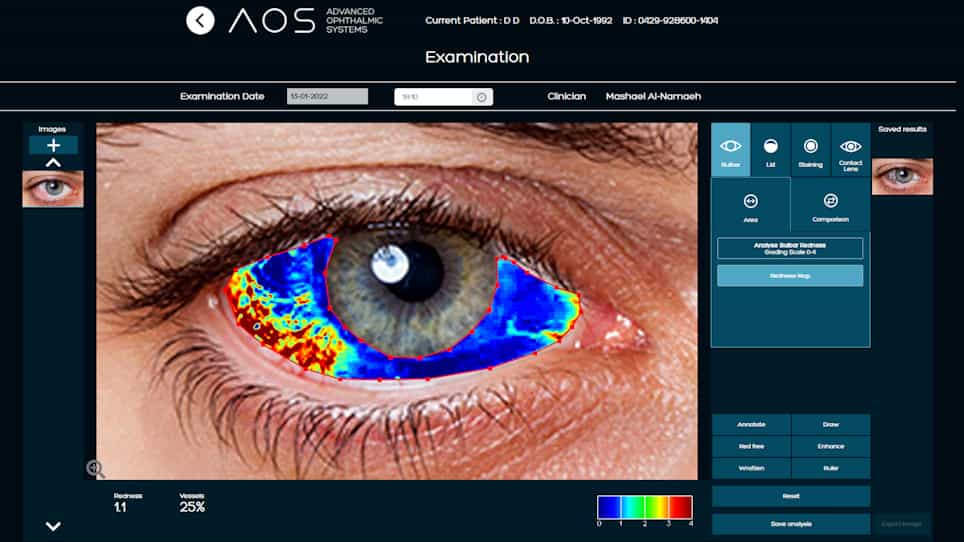
Comparing Objective Conjunctival Hyperemia Grading and the Ocular Surface Disease Index Score in Dry Eye Syndrome During COVID-19
Published on: May 25, 2022
Comparative Analysis of qSOFA, PRIEST, PAINT, and ISARIC4C Scores in Predicting Severe COVID-19 Outcomes Among
Daniela Rosca1, Vamsi Krishna2, Chandramouli Chetarajupalli3
1Doctoral School, "Victor Babes" University of Medicine and Pharmacy Timisoara, Eftimie Murgu Square 2, 300041 Timisoara, Romania.

Background:
Elderly patients, particularly those over 75 years old, have been disproportionately affected by COVID-19, exhibiting higher rates of severe outcomes, such as ICU admissions and mortality. This study aimed to evaluate and compare the effectiveness of various clinical scoring systems-qSOFA, PRIEST, PAINT, and ISARIC4C-in predicting ICU admission, the need for mechanical ventilation, and mortality among elderly COVID-19 patients.
Methods:
In this retrospective cohort study conducted at two tertiary care hospitals, 131 elderly patients (aged ≥ 75) and 226 younger controls (aged < 65) with confirmed COVID-19 were included. Clinical scores were computed at admission and five days after symptom onset. Kaplan-Meier survival analysis and Receiver Operating Characteristic (ROC) curve analysis were performed to assess the predictive performance of the scores regarding severe outcomes.
Results:
Kaplan-Meier analysis indicated significantly lower survival probabilities for elderly patients with high scores at admission. Those with an ISARIC4C score above 11.8 had a survival probability of 25% compared to 74% for those below this threshold (p < 0.001). Similarly, elderly patients with a qSOFA score above 2.1 had a survival probability of 36% compared to 72% for those with lower scores (p < 0.001). The PRIEST and PAINT scores also demonstrated predictive validity; patients with a PRIEST score above 6.3 and a PAINT score above 6.5 at admission showed comparable decreases in survival probabilities. ROC analysis at five days post-symptom onset revealed that the ISARIC4C score had the highest area under the curve (AUC) of 0.772, suggesting excellent predictive validity for severe outcomes, including mortality. The optimal cutoffs identified were 11.2 for ISARIC4C, 6.3 for PRIEST, and 6.5 for PAINT, each displaying high sensitivity and specificity.
Conclusions:
The ISARIC4C, qSOFA, PRIEST, and PAINT scores are robust predictors of severe outcomes in elderly COVID-19 patients over 75 years old, as confirmed by Kaplan-Meier and ROC analyses. These tools can be crucial for early identification of patients at high risk of adverse outcomes, guiding clinical decision making, and optimizing resource allocation. The use of these scoring systems should be encouraged in clinical settings to enhance the management of elderly COVID-19 patients. Further research is necessary to validate these findings across different populations and settings.

Related Concept Videos
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:17
Cochran's Q Test
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Statistical Methods for Analyzing Epidemiological Data
 01:12
Relative Risk
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...