Related Experiment Video
Updated: Jun 4, 2025
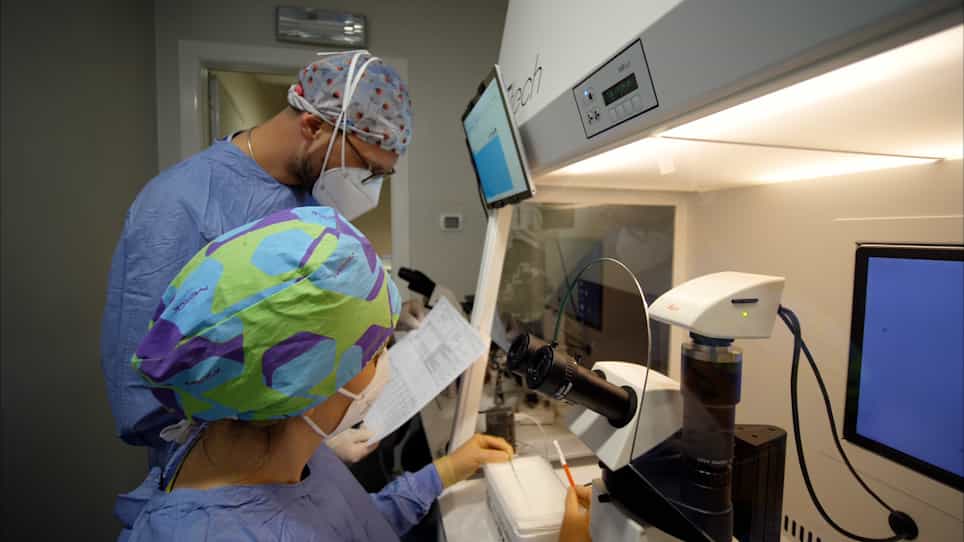
Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Flexible progestin-primed ovarian stimulation versus a GnRH antagonist protocol in predicted suboptimal responders
He Cai1, Zan Shi1, Danmeng Liu2
1Assisted Reproduction Center, Northwest Women's and Children's Hospital, Xi'an, China.

Study Question:
Are live birth rates (LBRs) per woman following flexible progestin-primed ovarian stimulation (fPPOS) treatment non-inferior to LBRs per woman following the conventional GnRH-antagonist protocol in expected suboptimal responders undergoing freeze-all cycles in assisted reproduction treatment?
Summary Answer:
In women expected to have a suboptimal response, the 12-month likelihood of live birth with the fPPOS treatment did not achieve the non-inferiority criteria when compared to the standard GnRH antagonist protocol for IVF/ICSI treatment with a freeze-all strategy.
What Is Known Already:
The standard PPOS protocol is effective for ovarian stimulation, where medroxyprogesterone acetate (MPA) is conventionally administered in the early follicular phase for ovulatory suppression. Recent retrospective cohort studies on donor cycles have shown the potential to prevent premature ovulation and maintain oocyte yields by delaying the administration of MPA until the midcycle (referred to as fPPOS), similar to GnRH antagonist injections. With milder pituitary suppression, the fPPOS protocol may be a less costly option for women expected to have a low or suboptimal response if a fresh embryo transfer is not intended.
Study Design, Size, Duration:
This was a non-inferiority, open-label randomized controlled trial conducted at a tertiary assisted reproduction center. A total of 484 participants were randomized in the study between July 2020 and June 2023 with a 1:1 allocation.
Participants/Materials, Setting, Methods:
Infertile women with a predicted suboptimal ovarian response (<40 years old, antral follicle count <10, and basal serum FSH < 12 mIU/ml) were randomly assigned to receive either fPPOS treatment or GnRH antagonist treatment. MPA (10 mg) or GnRH antagonist (0.25 mg) was administered daily once the leading follicle reached 14 mm and continued until the day of trigger. All viable embryos were cryopreserved for subsequent frozen-thawed embryo transfer in both groups. The primary endpoint was the proportion of live births per woman within 12 months post-randomization (with a non-inferiority margin of -12.5%). The analysis was assessed in the per-protocol population.
Main Results And The Role Of Chance:
Twenty-two women withdrew at the beginning of the stimulation phase due to COVID-19. Eight women did not proceed with the assigned frozen embryo transfer, and six switched from the fPPOS to the antagonist protocol. Overall, 449 women were included in the per-protocol analysis, with 216 in the fPPOS group and 233 in the GnRH antagonist group. The LBRs per woman were 44.4% (96/216) for participants in the fPPOS group and 48.9% (114/233) for participants in the GnRH antagonist group [risk ratio (RR) 0.91 (95% CI, 0.74, 1.11), risk difference (RD) -4.5% (95% CI, -13.7, 4.7)], which did not meet the non-inferiority criterion (-12.5%). Oocyte and embryonic parameters were not significantly different between the two groups. Nine women (4.17%) in the fPPOS group experienced a premature luteinizing hormone surge, compared to five women (2.15%) in the antagonist group. Only one woman in the fPPOS group ovulated before oocyte retrieval.
Limitations, Reasons For Caution:
The distinct routes of administration for the medications precluded blinding in this open-label trial, potentially influencing outcome assessments. All participants were recruited in a single center from one country, limiting the generalizability.
Wider Implications Of The Findings:
While MPA is considered a patient-friendly alternative to antagonists for women undergoing scheduled freeze-all cycles, the GnRH antagonist protocol should still be the preferred treatment for anticipated suboptimal responders in terms of LBR.
Study Funding/Competing Interest(S):
This trial was funded by Science and Technology Department of Shaanxi Province, China (2021SF-210). Innovation Team of Shaanxi Provincial Health and Reproductive Medicine Research (2023TD-04); Key Industrial Chain Projects in Shaanxi Province: Research on Assisted Reproductive Technologies and Precision Prevention System for Genetic Diseases Preconception (2023-ZDLSF-48). Science and Technology Department of Shaanxi Province, China (2022SF-564). B.W.M. reports consultancy, travel support and research funding from Merck KGaA and consultancy for Organon and Norgine; owning stock in ObsEva; and holding an NHMRC Investigator Grant (GNT1176437). Other authors declare no conflicts of interest. All other authors have nothing to declare.
Trial Registration Number:
Registered at Chinese clinical trial registry (www.chictr.org.cn). Registry Identifier: ChiCTR2000030356.
Trial Registration Date:
29 February 2020.
Date Of First Patient’S Enrolment:
11 March 2020.


Related Concept Videos
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:27
Ovarian Cycle
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...