Related Experiment Video
Updated: Jun 10, 2026
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Endoscopic resection of a giant irregular leiomyoma in fundus and cardia: A case report
Peng Li1, Guang-Ming Tang1, Pei-Lin Li2
1Department of Gastroenterology, Central Hospital Affiliated to Chongqing University of Technology, Chongqing 400054, China.

Insights
Endoscopic resection of giant gastric leiomyomas is challenging but feasible. Skilled endoscopists can successfully treat these large tumors using advanced endoscopic techniques.
Area of Science:
- Gastroenterology
- Surgical Endoscopy
Background:
- Giant gastric leiomyomas, especially in the fundus and cardia, pose significant endoscopic surgical challenges.
- Documented cases of endoscopic resection for such large tumors are infrequent.
Observation:
- A 59-year-old woman presented with right upper abdominal pain due to an 8 cm x 5 cm giant gastric leiomyoma.
- The patient underwent combined laparoscopic cholecystectomy and endoscopic submucosal excavation with full-thickness resection for the gastric submucosal tumor (SMT).
Findings:
- Complete endoscopic resection of the giant gastric leiomyoma was achieved.
- The procedure involved approximately 3 hours for resection and 3 hours for wound closure and extraction.
- Post-operative transient peritonitis occurred, but the patient recovered without cardiac complications.
Implications:
- Endoscopic resection is a viable and suitable treatment option for giant gastric leiomyomas in the cardiac fundus.
- This technique requires significant expertise and skill from the endoscopist.
Background:
Endoscopic resection of giant gastric leiomyomas, particularly in the fundus and cardia regions, is infrequently documented and presents a significant challenge for endoscopic surgery.
Case Summary:
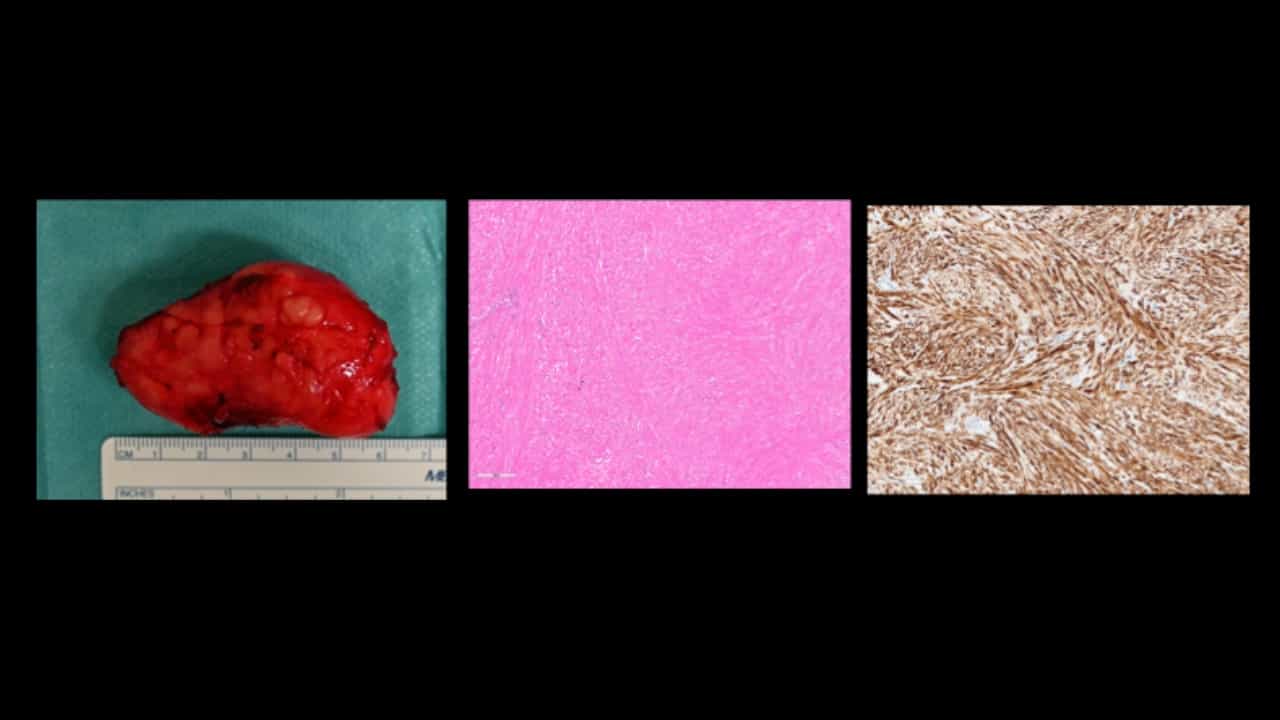
Herein, a case of a 59-year-old woman with a giant gastric leiomyoma was reported. The patient presented to the department of hepatological surgery with a complaint of right upper abdominal pain for one month and worsening for one week. The patient was diagnosed as gastric submucosal tumor (SMT), gallstone, and cholecystitis combined with computed tomography and gastroendoscopy prior to operation. Upon admission, following a multi-disciplinary treatment discussion, it was determined that the patient would undergo a laparoscopic cholecystectomy and endoscopic resection of gastric SMT. It took 3 hours to completely resect the lesion by Endoscopic submucosal excavation and endoscopic full-thickness resection, and about 3 hours to suture the wound and take out the lesion. The lesion, ginger-shaped and measuring 8 cm × 5 cm, led to transient peritonitis post-surgery. With no cardiac complications, the patient was discharged one week after surgery.
Conclusion:
Endoscopic resection of a giant leiomyoma in the cardiac fundus is feasible and suitable for skilled endoscopists.