Related Experiment Video
Updated: Jun 4, 2025
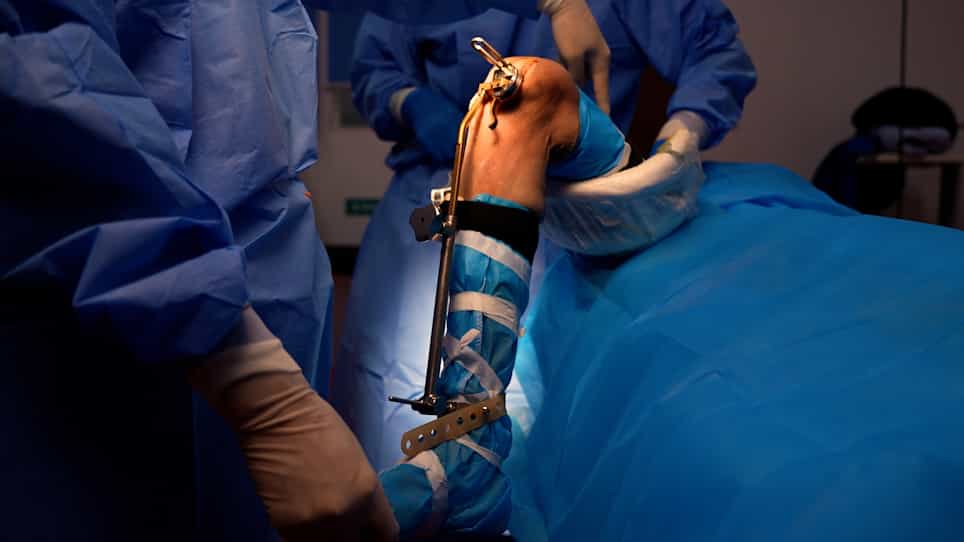

In Vitro Application of a Wireless Sensor in Flexion-Extension Gap Balance of Unicompartmental Knee Arthroplasty
Published on: May 5, 2023
Robotic arm-assisted medial compartment knee arthroplasty is a cost-effective intervention at ten-year follow-up
Mark J G Blyth1, Nick D Clement2, Xin Y Choo1
1Department of Trauma and Orthopaedics, Glasgow Royal Infirmary, Glasgow, UK.

Aims:
The aim of this study was to perform an incremental cost-utility analysis and assess the impact of differential costs and case volume on the cost-effectiveness of robotic arm-assisted medial unicompartmental knee arthroplasty (rUKA) compared to manual (mUKA).
Methods:
Ten-year follow-up of patients who were randomized to rUKA (n = 64) or mUKA (n = 65) was performed. Patients completed the EuroQol five-dimension health questionnaire preoperatively, at three months, and one, two, five, and ten years postoperatively, which was used to calculate quality-adjusted life years (QALY) gained and the incremental cost-effectiveness ratio (ICER). Costs for the index and additional surgery and healthcare costs were calculated.
Results:
mUKA had a lower survival for reintervention (84.8% (95% CI 76.2 to 93.4); p = 0.001), all-cause revision (88.9% (95% CI 81.3 to 96.5); p = 0.007) and aseptic revision (91.9% (95% CI 85.1 to 98.7); p = 0.023) when compared to the rUKA group at ten years, which was 100%. The rUKA group had a greater QALY gain per patient (mean difference 0.186; p = 0.651). Overall rUKA was the dominant intervention, being cost-saving and more effective with a greater health-related quality of life gain. On removal of infected reinterventions (n = 2), the ICER was £757 (not discounted) and £481 (discounted). When including all reintervention costs, rUKA was cost-saving when more than 100 robotic cases were performed per year. When removing the infected cases, rUKA was cost-saving when undertaking more than 800 robotic cases per year.
Conclusion:
rUKA had lower reintervention and revision risks at ten years, which was cost-saving and associated with a greater QALY gain, and was the dominant procedure. When removing the cost of infection, which could be a random event, rUKA was a cost-effective intervention with an ICER (£757) which was lower than the willingness-to-pay threshold (£20,000).
More Related Videos
 07:24
Autologous Microfractured and Purified Adipose Tissue for Arthroscopic Management of Osteochondral Lesions of the Talus
Published on: January 23, 2018
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022