Small bowel duplication cyst in the pediatric population-when to operate?
Related Experiment Video
Updated: May 7, 2025
Robotic D3 Partial Duodenal Resection with Primary Side-to-Side Anastomosis
Published on: December 15, 2023
Yael Dreznik1,2, Anastasia Almog3,4, Maya Paran3,4
1Department of Pediatric and Adolescent Surgery, Schneider Children's Medical Center of Israel, 14 Kaplan St, Petah Tiqwa, Israel. yael.dreznik@gmail.com.

Insights
For pediatric small bowel duplications, expectant management of asymptomatic cysts is safe. Surgery after one year of age allows for laparoscopic exploration and good outcomes.
Area of Science:
- Pediatric Surgery
- Gastrointestinal Surgery
- Congenital Abnormalities
Background:
- Small bowel duplications are rare congenital anomalies.
- Optimal surgical timing for pediatric small bowel duplications remains a subject of investigation.
Purpose of the Study:
- To determine the optimal timing for surgical intervention in pediatric patients diagnosed with small bowel duplications.
Main Methods:
- A retrospective cohort study was conducted on pediatric patients (<18 years) diagnosed with small bowel duplications between 2013 and 2024.
- Data collected included demographics, duplication characteristics, pathology, and clinical outcomes.
Main Results:
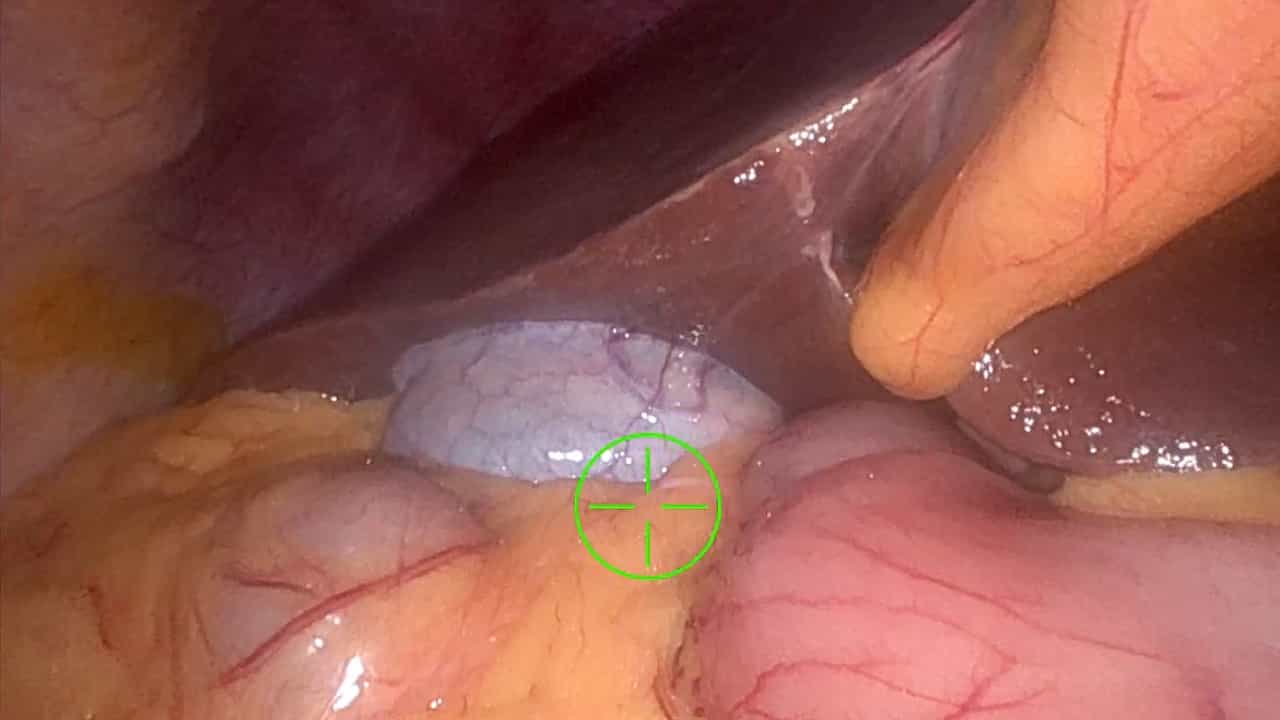
- Sixteen patients underwent laparoscopic-assisted resection of small bowel duplications.
- Patients with prenatal diagnosis (n=11) underwent elective surgery at a median age of 1.3 years and had smaller duplications.
- Urgent surgery was required for six patients due to complications, most lacking prenatal evaluation.
Conclusions:
- Asymptomatic, small small bowel duplication cysts in pediatric patients can be managed expectantly.
- Surgery after the first year of age is safe and facilitates laparoscopic exploration in older infants.
- This approach leads to satisfactory clinical outcomes and recovery.
Introduction:
AIM: The aim of the study is to determine the optimal timing for surgery in patients with small bowel duplications.
Methods:
A retrospective cohort study, including all patients younger than 18 years who were diagnosed with small bowel duplications from 2013 until 2024 in a single tertiary medical center, was performed. Patients' demographics, duplication size and location, pathological results, and clinical outcomes were collected.
Results:
Sixteen patients (nine boys, seven girls) underwent laparoscopic-assisted resection of small bowel duplication at an average age of 3 years. A prenatal diagnosis was made in 11 patients, 10 (91%) of whom underwent elective surgery at a median age of 1.3 years. Overall, six patients required semi-elective or urgent surgery due to bowel obstruction, abdominal discomfort, or symptomatic anemia, with most (83%) lacking prenatal evaluation. Elective surgery patients had significantly smaller duplications (13 cm3 vs. 135 cm3). Post-operative recovery was satisfactory in all patients, with an average hospital stay of 6 days.
Conclusion:
In conclusion, asymptomatic, small duplication cysts in the small bowel of pediatric patients can be managed expectantly and can be operated after the first year of age. This approach is safe and allows for laparoscopic exploration in older infants, yielding satisfactory outcomes.