Related Experiment Video
Updated: Jun 4, 2025

Robotic Spleen-Preserving Distal Pancreatectomy: The Warshaw and Kimura Techniques
Published on: July 26, 2024
Laparoscopic Warshaw Procedure for Solid Pseudopapillary Neoplasms in Children
Chirag Ram1, Katharyn Cassella2, Jan A Niec1
1Vanderbilt University School of Medicine, Nashville, TN, USA.

Abstract:
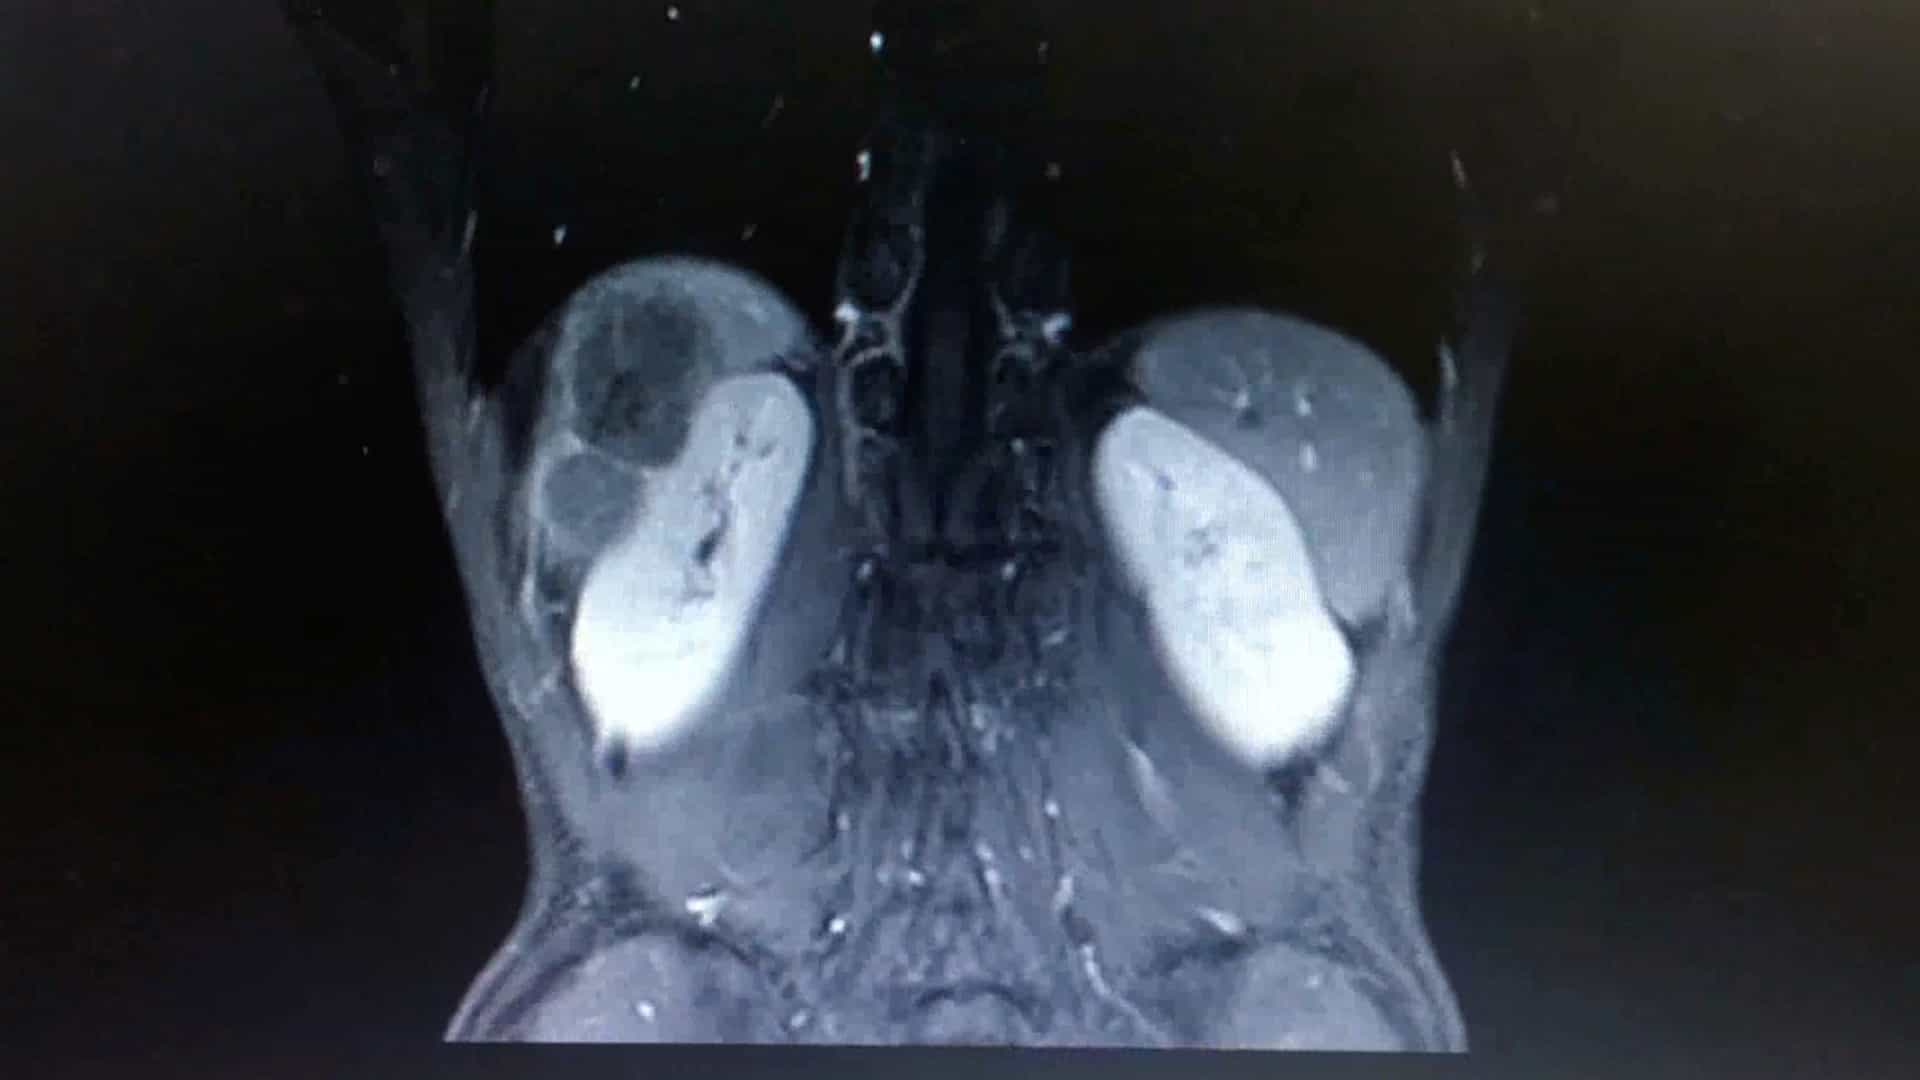
BackgroundSolid pseudopapillary neoplasms (SPNs) arising in the body or tail of the pancreas can be amenable to laparoscopic distal pancreatectomy with or without concomitant splenectomy. The purpose of this study was to evaluate laparoscopic distal pancreatectomy for SPN using the Warshaw technique as a means to preserve spleens in children.MethodsWe reviewed our database of SPN patients 19 years and younger (January 2006-December 2023). Five had a laparoscopic Warshaw procedure. Using the volumetric analysis tool in Sectra, a pediatric radiologist calculated preoperative tumor, pancreas, and spleen volumes (including postoperative organ volumes) on computed tomography. Descriptive statistics were performed.ResultsAll five spleens were salvaged, although small infarcts occurred centrally in four patients. Splenic volumes on first imaging after Warshaw averaged 93.9% of preoperative size. Splenic volumes were preserved over time, as the most recent scans averaged 110.6% of the preoperative spleen volume. Collateral flow through the short gastric arteries, inferred from dilation on scans, increased in all patients. Median tumor volume was 85.2 mL, and all SPN were resected with negative margins. No relapse occurred (median follow up: 407 days). Median estimated blood loss was 100 mL, median length of procedure was 4.9 hours, and median inpatient length of stay was 3 days. A multimodal pain regimen, including preoperative TAP blocks, non-opiate, and opiate medications, resulted in a median 81 Morphine Milligram Equivalents (MMEs) administered during the hospital stay.ConclusionLaparoscopic Warshaw for SPN in children appears highly effective at preserving splenic volume without compromising oncologic fidelity or consuming excess inpatient resources.