Related Experiment Video
Updated: May 7, 2025


Author Spotlight: Development of a Novel Finite Element Analysis Model for Improved Orthognathic Surgical Techniques
Published on: October 20, 2023
Changes in upper airway airflow after rapid maxillary expansion considering normal craniofacial development as a
Antonino Lo Giudice1, Alessandro Polizzi1, Manuel Lagravere2
1Department of General Surgery and Medical-Surgical Specialties, Section of Orthodontics, University of Catania, Policlinico Universitario 'Gaspare Rodolico-San Marco', Via Santa Sofia 78, 95123, Catania, Italy.

Background/Objectives:
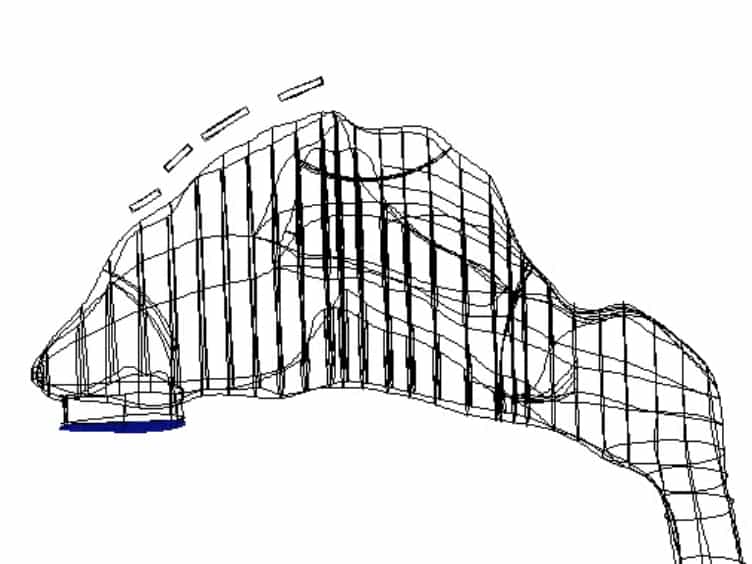
Evidence suggests nasal airflow resistance reduces after rapid maxillary expansion (RME). However, the medium-term effects of RME on upper airway (UA) airflow characteristics when normal craniofacial development is considered are still unclear. This retrospective cohort study used computer fluid dynamics (CFD) to evaluate the medium-term changes in the UA airflow (pressure and velocity) after RME in two distinct age-based cohorts.
Materials/Methods:
The study included 48 subjects who underwent RME divided into two cohorts: a 6-9-year-old group (EEG group: early expansion group - 25 subjects) and an 11-14-year-old group (LEG group: late expansion group - 23 subjects). The nasal cavity and pharyngeal anatomy were segmented from Cone-beam computed tomography reconstructions taken before RME (T0) and 12 after RME (T1). The two UA airflow variables (pressure and velocity) were simulated using CFD. The maxillary expansion (PW) amount, two cross-sectional area measurements (CS1 = anterior cross-section and CS2 = posterior cross-section), and four UAs' subregions (NC = nasal cavity, PAtotal = pharyngeal airway, NP = nasopharynx, VP = velopharynx, and OP = Oropharynx) were also considered. All data were statistically analyzed.
Results:
At the baseline, the airflow pressure, velocity, and noted obstructions were significantly higher in the EEG compared to LEG. At T1, there was a significant improvement in the median airway parameters in both groups, which was remarkably greater in the EEG. A significant negative correlation was found between pressure/velocity and both CS2 and NP. According to the CFD plots, the airflow pressure and velocity changes could be attributed to the reduction of the adenotonsillar tissues' sizes, which were remarkably more marked in the EEG.
Limitations:
The results of this study cannot be generalized since they referred to a retrospective orthodontic sample without obstructive adenotonsillar hypertrophy.
Conclusions/Implications:
Twelve months after RME, normal craniofacial developmental changes and spontaneous adenotonsillar tissues volume regression could represent the most significant factors influencing UA airflow changes.

Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
Anatomy of Respiratory System I: Upper Respiratory Tract
Nose and nasal cavity
The nose and nasal cavity represent the main external openings of the respiratory tract....