Related Experiment Video
Updated: Jun 3, 2025
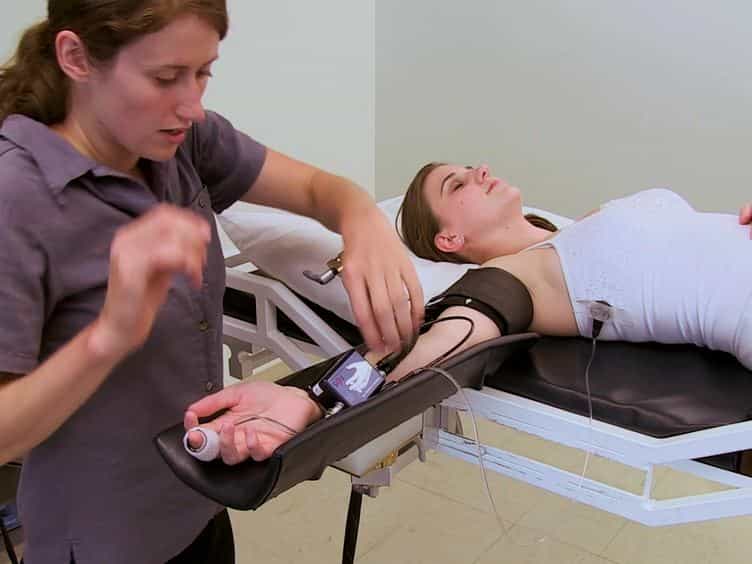

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
The Cardiac Output-Cerebral Blood Flow Relationship Is Abnormal in Most Myalgic Encephalomyelitis/Chronic Fatigue
C Linda M C van Campen1, Freek W A Verheugt2, Peter C Rowe3
1Stichting Cardio Zorg, Kraayveld 5, 1171 JE Badhoevedorp, The Netherlands.

Insights
Most myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) patients exhibit abnormal cerebral blood flow (CBF) and cardiac output (CO) during tilt testing. This suggests potential endothelial dysfunction in ME/CFS, impacting clinical management.
Area of Science:
- Cardiology
- Neurology
- Physiology
Background:
- Orthostatic intolerance is common in myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS), linked to reduced cerebral blood flow (CBF).
- In healthy individuals, cardiac output (CO) significantly influences CBF regulation.
- Previous studies indicated similar reductions in CO and CBF in ME/CFS patients during tilt tests.
Purpose of the Study:
- To investigate the relationship between CBF and CO in ME/CFS patients.
- To determine if this relationship differs between ME/CFS patients and healthy controls (HCs).
Main Methods:
- A retrospective analysis of tilt testing data from 534 ME/CFS patients and 49 HCs.
- Measurements included heart rate (HR), blood pressure (BP), CBF, CO, and end-tidal PCO2 (PETCO2).
- CBF and CO were measured using Doppler ultrasound, focusing on patients with normal HR and BP responses during tilt.
Main Results:
- 91% of ME/CFS patients showed abnormal reductions in CO and CBF during tilt testing.
- In these patients, CO reduction strongly predicted CBF reduction (1:1 relationship).
- End-tidal PCO2 reduction played a minor role in CBF changes.
Conclusions:
- Two distinct groups of ME/CFS patients were identified based on tilt test responses.
- The majority (91%) exhibited abnormal CO and CBF reductions, suggesting impaired compensatory vasodilation.
- This points to potential endothelial dysfunction in most ME/CFS patients, with implications for treatment.
Introduction:
Orthostatic intolerance is highly prevalent in patients with myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and is caused by an abnormal reduction in cerebral blood flow (CBF). In healthy controls (HCs), the regulation of CBF is complex and cardiac output (CO) is an important determinant of CBF: a review showed that a 30% reduction in CO results in a 10% reduction in CBF. In previous and separate ME/CFS studies, we showed that CO and CBF decreased to a similar extent during tilt testing.
The Aim Of The Study:
to test the relationship between CBF and CO, which seems to be abnormal in ME/CFS patients and is different from that in HCs.
Methods:
In this retrospective study we analyzed this relationship in a large group of patients. To compare the patient data with those of HCs, we focused on patients with a normal heart rate (HR) and blood pressure (BP) response to upright tilt. Also, the influence of clinical data was analyzed. A total of 534 ME/CFS patients and 49 HCs underwent tilt testing with measurements of HR, BP, CBF, CO, and end-tidal PCO2. To measure CBF, extracranial Doppler flow velocity and vessel diameters were obtained using a GE echo system. The same device was used to measure suprasternal aortic flow velocities. End-tidal PCO2 was recorded using a Nonin Lifesense device.
Results:
In 46 (9%) patients, CO and CBF changes were in the normal range for HCs, and in 488 (91%) an abnormal CO and CBF reduction was found. In patients with abnormal CO and CBF reductions, the slope of the regression line of CO versus CBF reduction was almost 1. The multiple regression analysis of the latter group showed that the CO reduction for the most part predicted the CBF reduction, with a limited role for the PETCO2 reduction.
Conclusions:
Two different patient groups with a normal HR and BP response during the tilt were identified: those with a CO and CBF in the normal range for HCs and those with an abnormal CO and CBF reduction during the tilt (91% of patients). In the latter group of patients, an almost 1:1 relationship between the CO and CBF reduction suggests the absence of compensatory vasodilation in the cerebral vasculature. This might indicate endothelial dysfunction in most ME/CFS patients and may have clinical and therapeutic implications.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
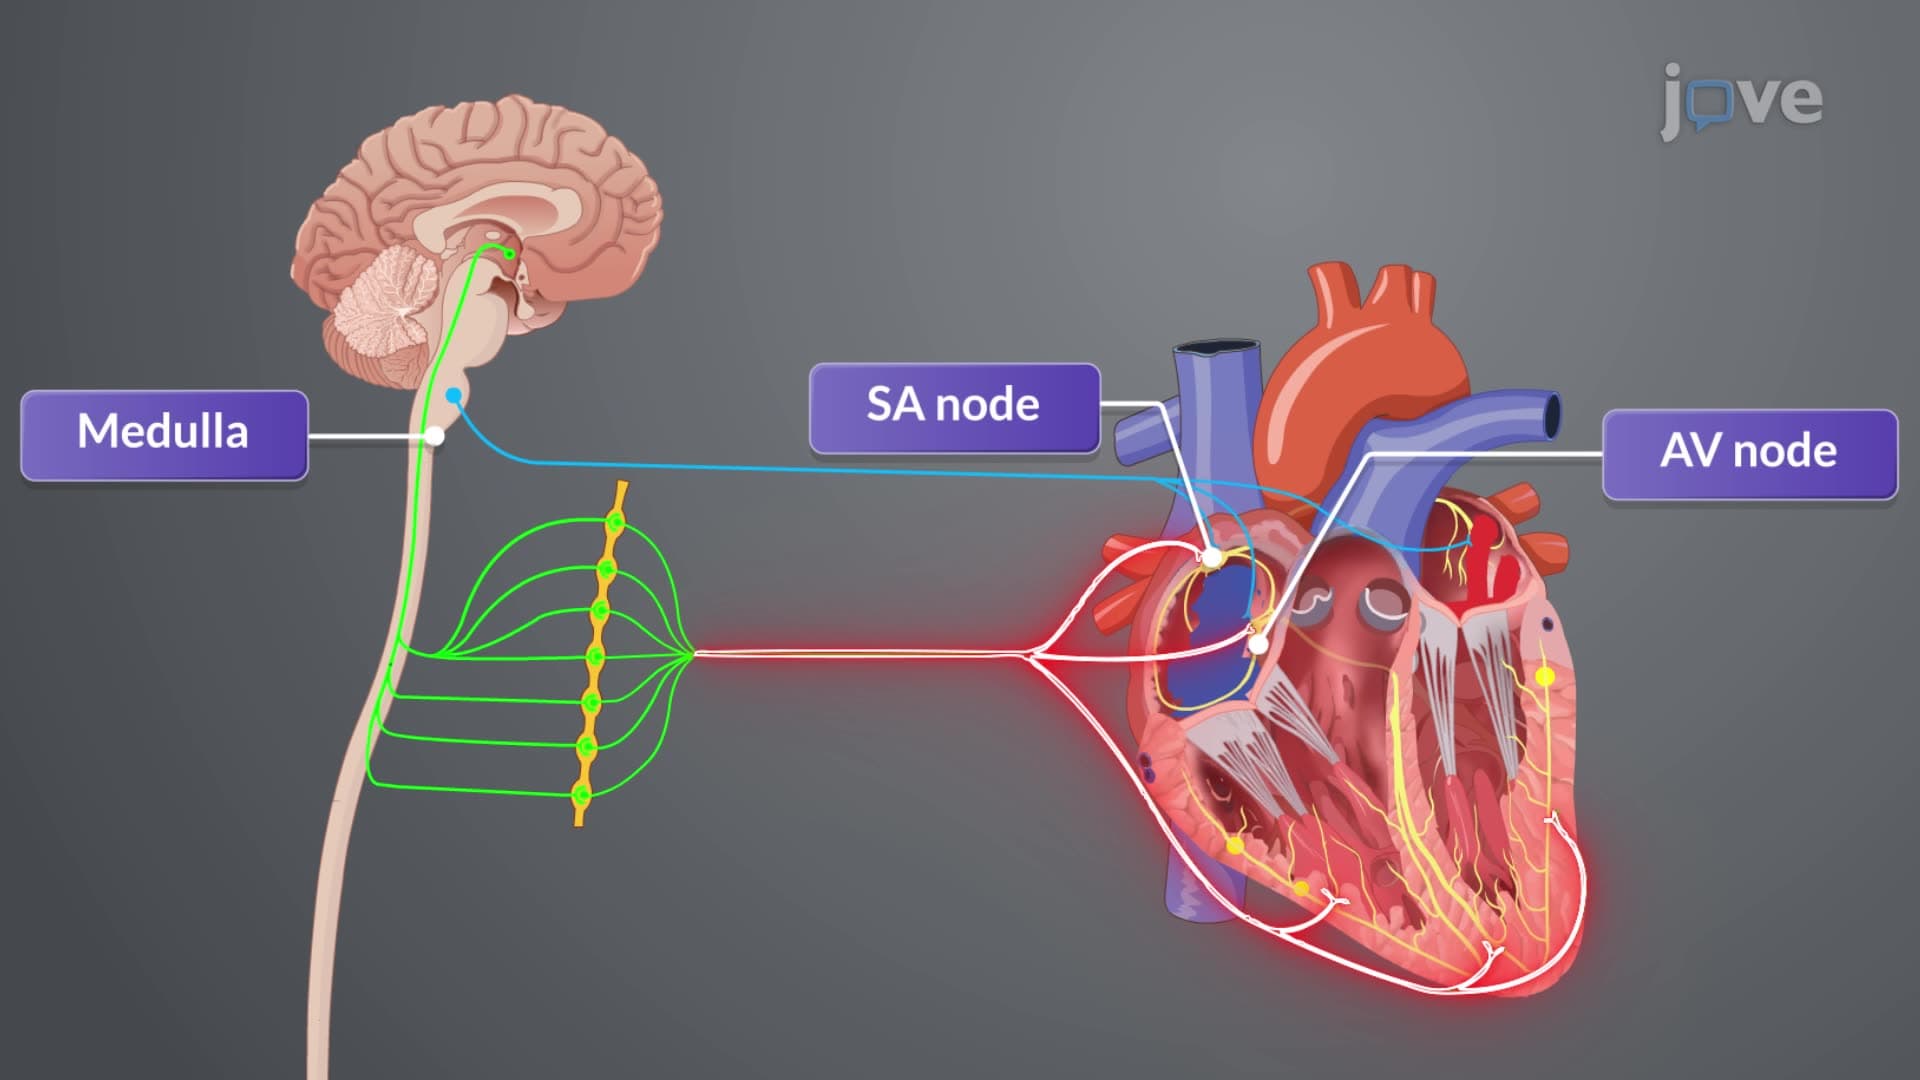
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...