Comparative Analysis of Outcomes in Adult Spinal Deformity Patients with Proximal Junctional Kyphosis or Failure Initially Fused to Upper Versus Lower Thoracic Spine
Related Experiment Video
Updated: Jun 3, 2025
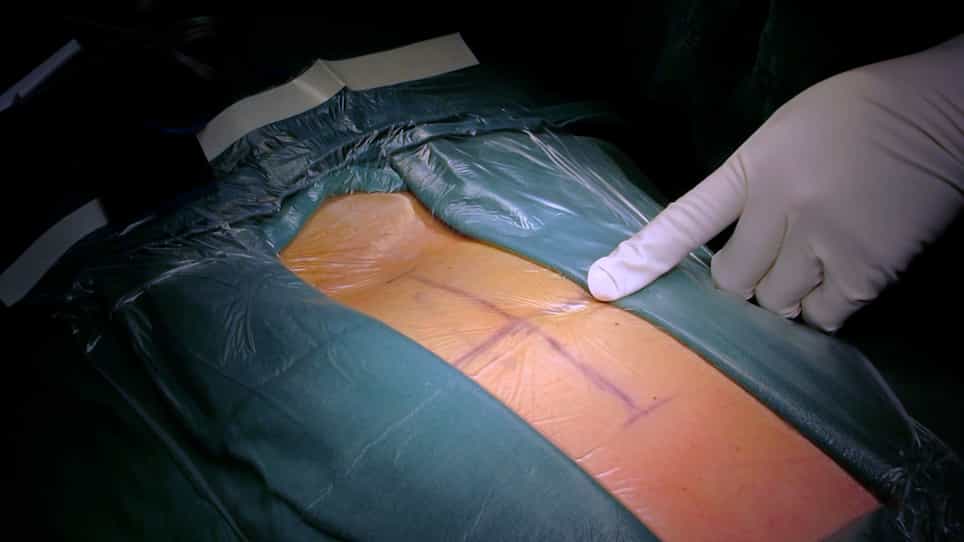
Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Oluwatobi O Onafowokan1, Renaud Lafage2, Peter Tretiakov1
1Duke Spine Division, Departments of Neurological and Orthopaedic Surgery, Duke School of Medicine, Durham, NC 27710, USA.

Abstract:
Background: Patients with proximal junctional kyphosis (PJK) or failure (PJF) may demonstrate disparate outcomes and recovery when fused to the upper (UT) versus lower (LT) thoracic spine. Few studies have distinguished the reoperation and recovery abilities of patients with PJK or PJF when fused to the upper (UT) versus lower (LT) thoracic spine. Methods: Adult spine deformity patients ≥ 18 yrs with preoperative and 5-year (5Y) data fused to the sacrum/pelvis were included. The rates of PJK, PJK revision, and radiographic PJF were compared between patients with upper instrumented vertebra (UIV) in the upper thoracic spine (UT; T1-T7) and lower thoracic spine (LT; T8-L1). Mean differences were assessed via analyses of covariance, factoring in any differences between cohorts at baseline and any use of PJF prophylaxis. Backstep logistic regressions assessed predictors of achieving Smith et al.'s Best Clinical Outcomes (BCOs) and complications, controlling for similar covariates. Results: A total of 232 ASD patients were included (64.2 ± 10.2 years, 78% female); 36.3% were UT and 63.7% were LT. Postoperatively, the rates of PJK for UT were lower than LT at 1Y (34.6 vs. 50.4%, p = 0.024), 2Y (29.5 vs. 49.6% (p = 0.003), and 5Y (48.7 vs. 62.8%, p = 0.048), with comparable rates of PJF. In total, 4.0% of UT patients underwent subsequent reoperation, compared to 13.0% of LT patients (p = 0.025). A total of 6.0% of patients had recurrent PJK, and 3.9% had recurrent PJF (both p > 0.05). After reoperation, UT patients reported higher rates of improvement in the minimum clinically important difference for ODI by 2Y (p = 0.007) and last follow-up (p < 0.001). While adjusted regression revealed that, for UT patients, the minimization of construct extension was predictive of achieving BCOs by last follow-up (model p < 0.001), no such relationship was identified in LT patients. Conclusions: Patients initially fused to the lower thoracic spine demonstrate an increased incidence of PJK and lower rates of disability improvement, but are at a lessened risk of neurologic complications if reoperation is required.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Related Concept Videos
 01:16
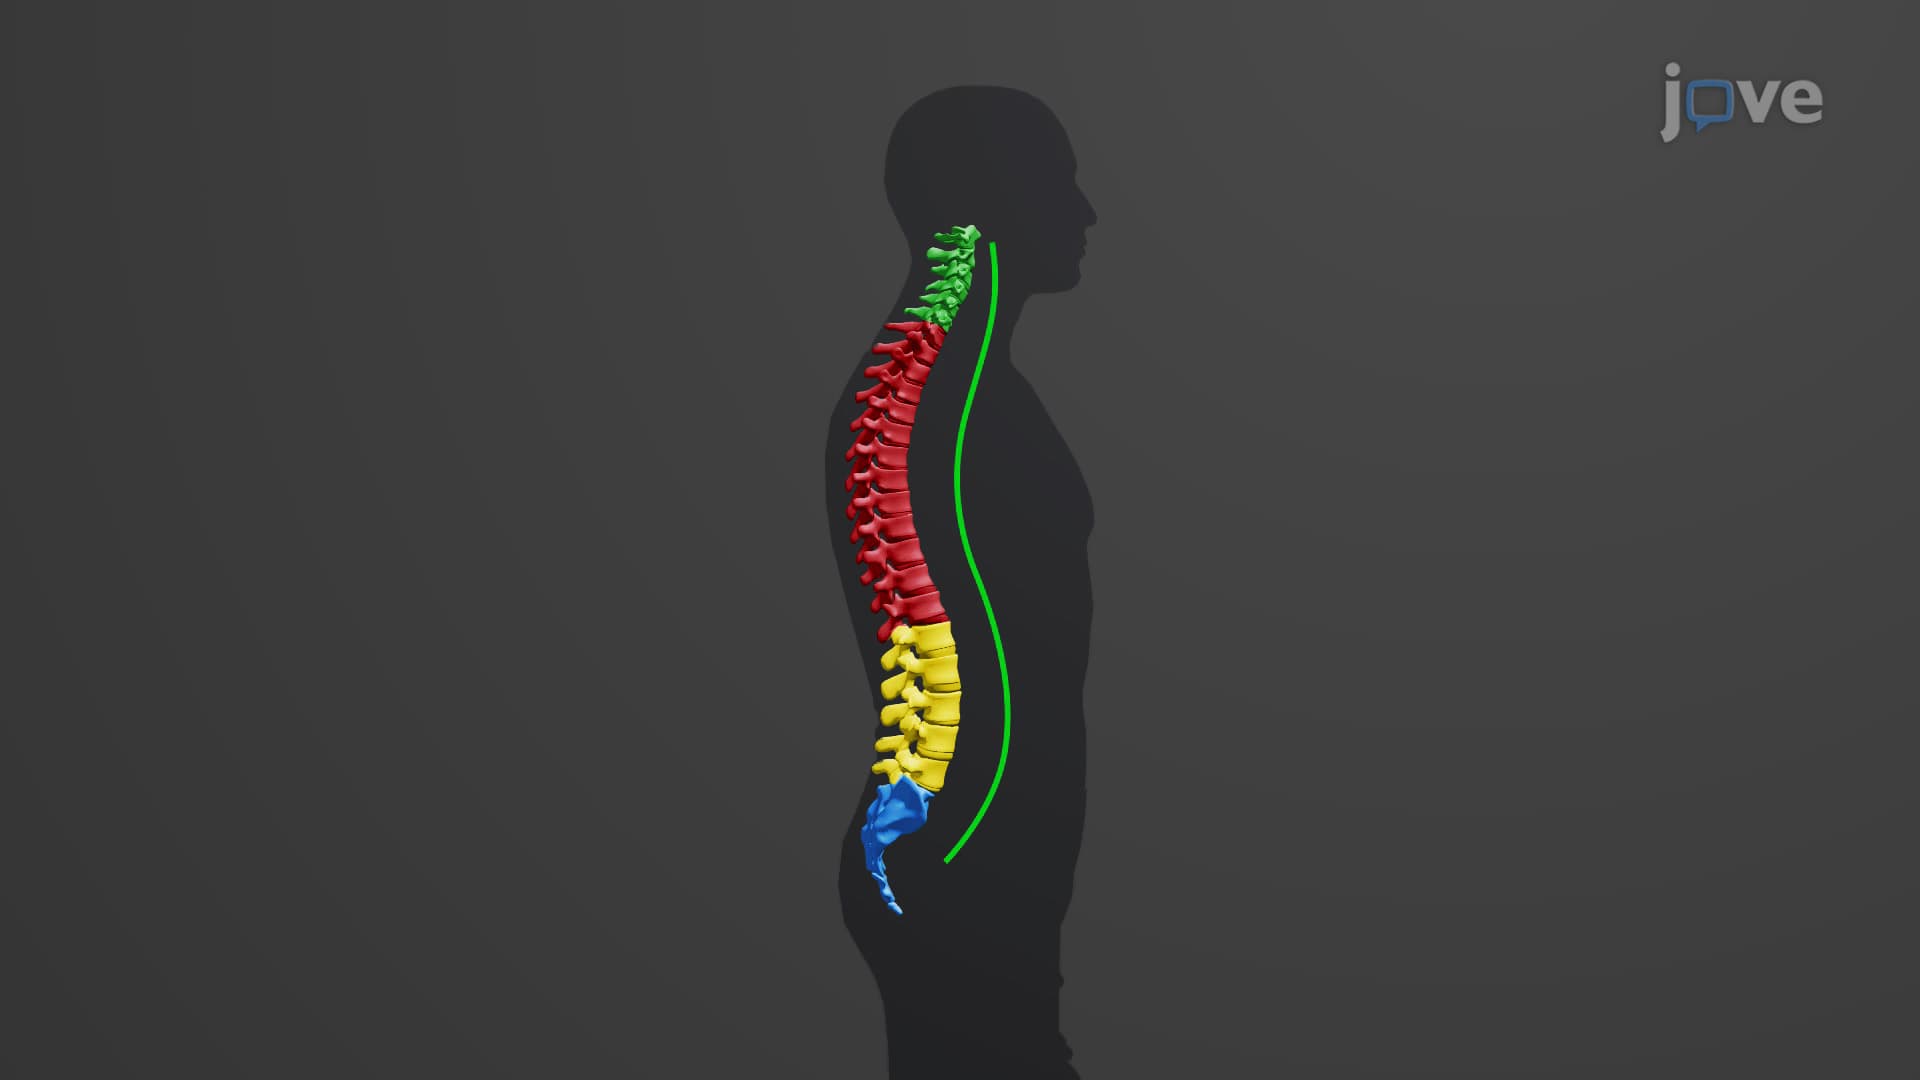
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:30
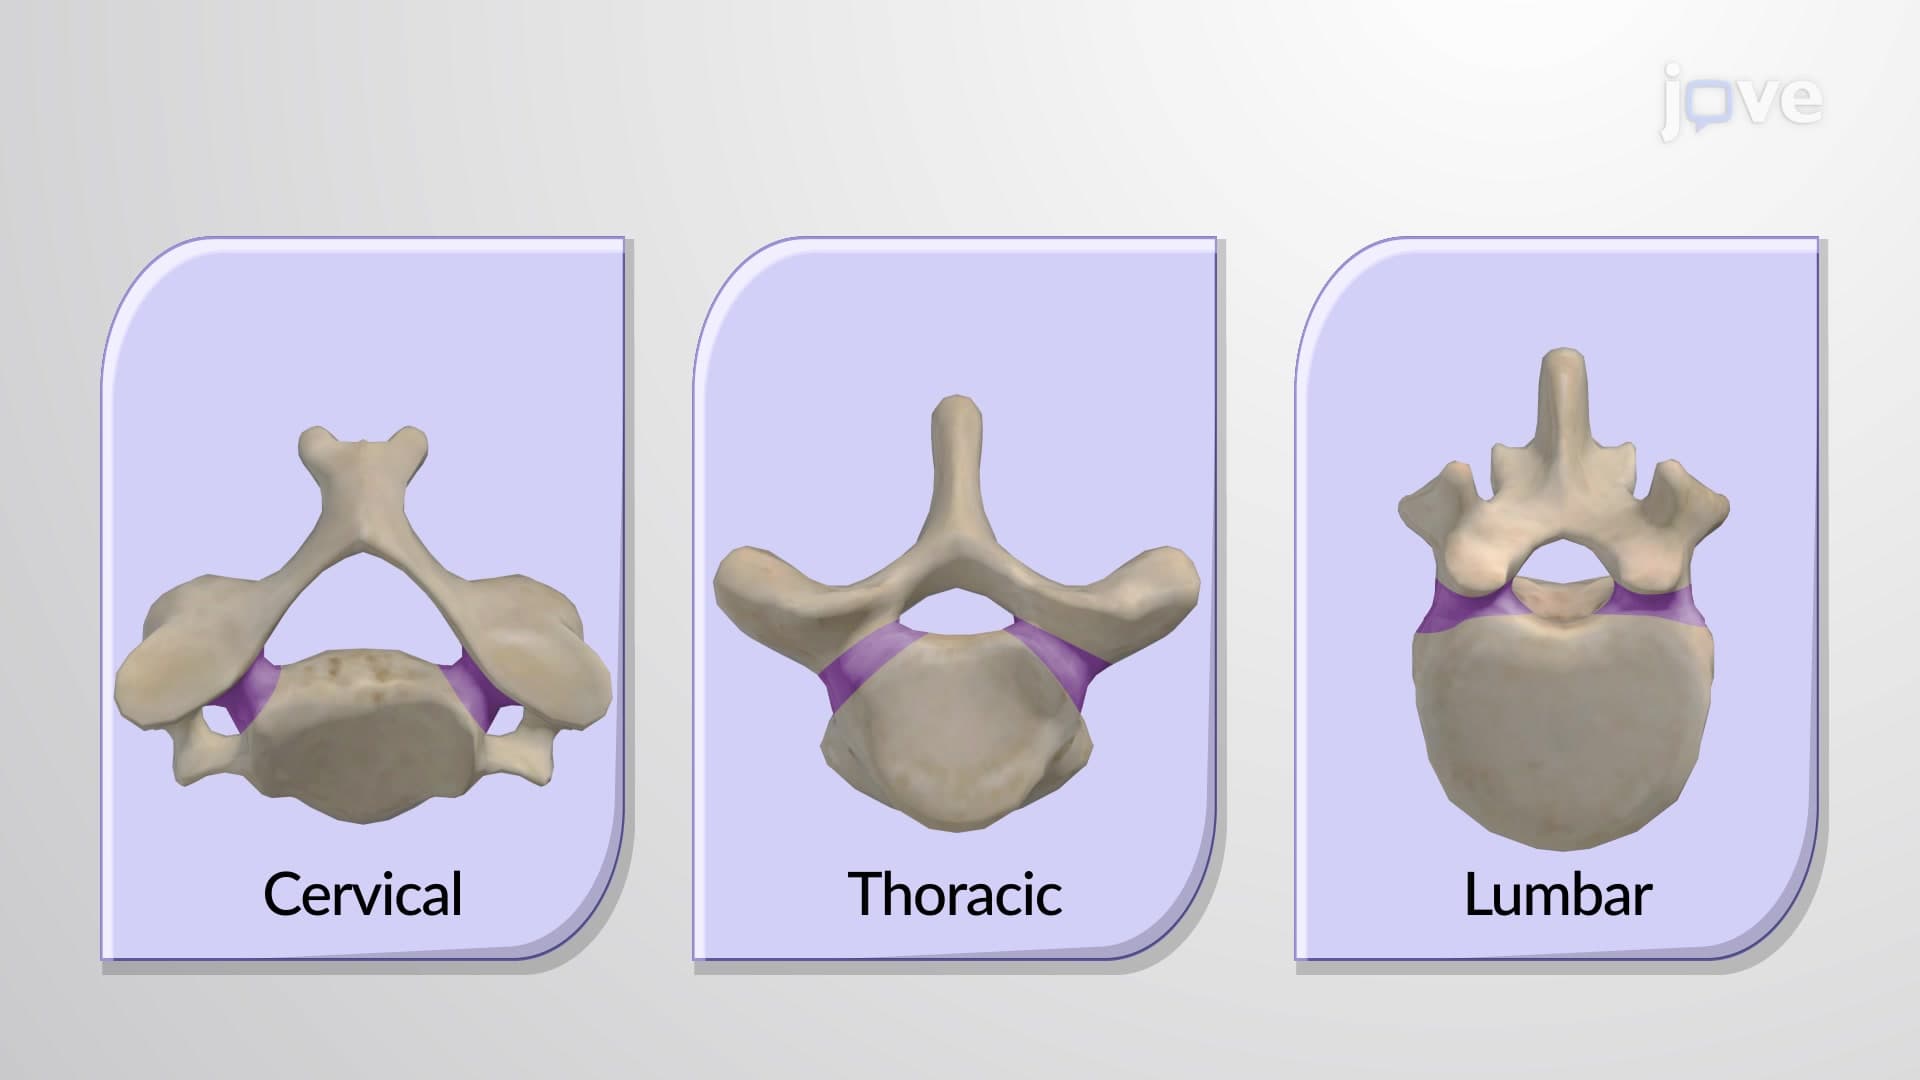
General Structure of a Vertebra
 01:16
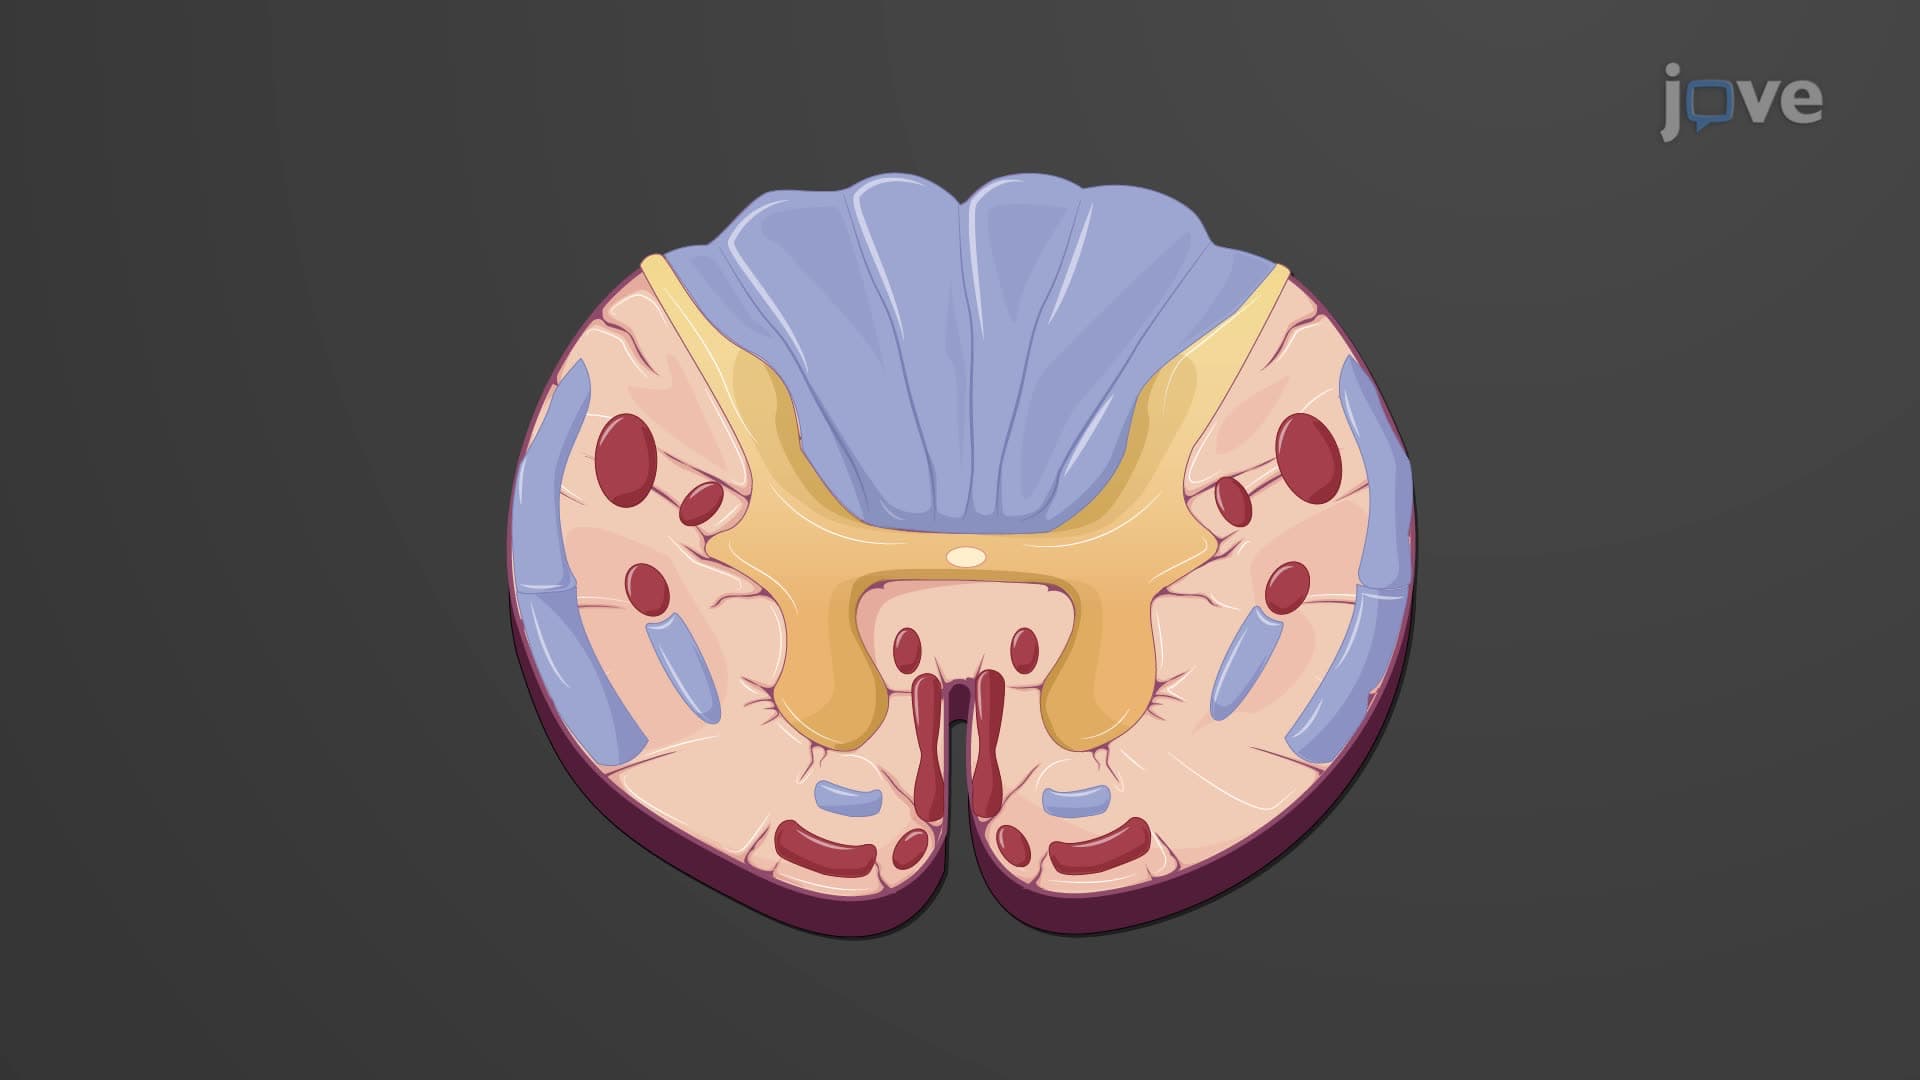
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray...