Related Experiment Video
Updated: Jun 3, 2025
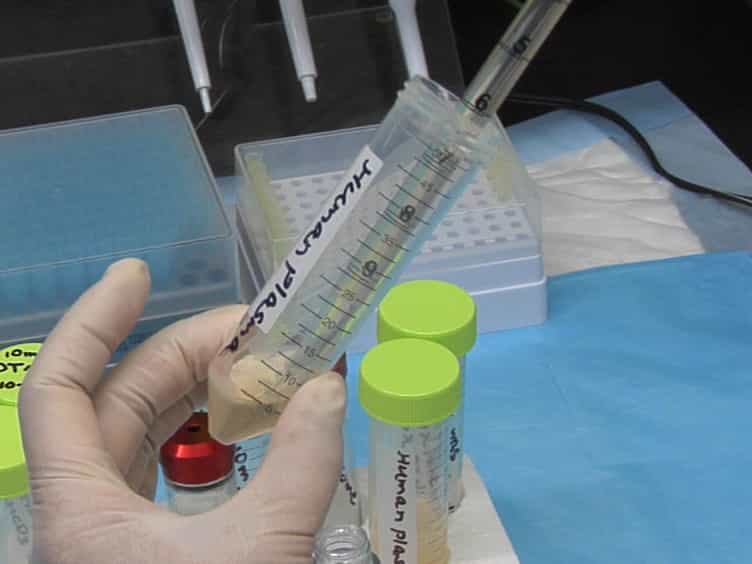
Isolation of Exosomes from the Plasma of HIV-1 Positive Individuals
Published on: January 5, 2016
The Impact of HIV on B Cell Compartment and Its Implications for COVID-19 Vaccinations in People with HIV
Lixing Wang1,2, Branka Vulesevic2, MariaLuisa Vigano2,3
1Department of Microbiology and Immunology, McGill University, Montreal, QC H3A 2B4, Canada.

HIV causes intense polyclonal activation of B cells, resulting in increased numbers of spontaneously antibody-secreting cells in the circulation and hypergammaglobulinemia. It is accompanied by significant perturbations in various B cell subsets, such as increased frequencies of immature/transitional B cells, activated memory B cells, atypical memory B cells, short-lived plasmablasts and regulatory B cells, as well as by decreased frequencies of resting memory and resting naïve B cells. Furthermore, both memory and antigen-inexperienced naïve B cells show exhausted and immune-senescent phenotypes. HIV also drives the expansion and functional impairment of CD4+ T follicular helper cells, which provide help to B cells, crucial for the generation of germinal center reactions and production of long-lived plasma and memory B cells. By suppressing viral replication, anti-retroviral therapy reverses the virus-induced perturbations and functional defects, albeit inadequately. Due to HIV's lingering impact on B cells, immune senescence and residual chronic inflammation, people with HIV (PWH), especially immune non-responders, are immunocompromised and mount suboptimal antibody responses to vaccination for SARS-CoV-2. Here, we review how functionally and phenotypically distinct B cell subsets are induced in response to a vaccine and an infection and how HIV infection and anti-retroviral therapy (ART) impact them. We also review the role played by HIV-induced defects and perturbations in B cells in the induction of humoral immune responses to currently used anti-SARS-CoV-2 vaccines in PWH on ART. We also outline different strategies that could potentially enhance the vaccine-induced antibody responses in PWH. The review will provide guidance and impetus for further research to improve the immunogenicity of these vaccines in this human population.
HIV causes intense polyclonal activation of B cells, resulting in increased numbers of spontaneously antibody-secreting cells in the circulation and hypergammaglobulinemia. It is accompanied by significant perturbations in various B cell subsets, such as increased frequencies of immature/transitional B cells, activated memory B cells, atypical memory B cells, short-lived plasmablasts and regulatory B cells, as well as by decreased frequencies of resting memory and resting naïve B cells. Furthermore, both memory and antigen-inexperienced naïve B cells show exhausted and immune-senescent phenotypes. HIV also drives the expansion and functional impairment of CD4+ T follicular helper cells, which provide help to B cells, crucial for the generation of germinal center reactions and production of long-lived plasma and memory B cells. By suppressing viral replication, anti-retroviral therapy reverses the virus-induced perturbations and functional defects, albeit inadequately. Due to HIV's lingering impact on B cells, immune senescence and residual chronic inflammation, people with HIV (PWH), especially immune non-responders, are immunocompromised and mount suboptimal antibody responses to vaccination for SARS-CoV-2. Here, we review how functionally and phenotypically distinct B cell subsets are induced in response to a vaccine and an infection and how HIV infection and anti-retroviral therapy (ART) impact them. We also review the role played by HIV-induced defects and perturbations in B cells in the induction of humoral immune responses to currently used anti-SARS-CoV-2 vaccines in PWH on ART. We also outline different strategies that could potentially enhance the vaccine-induced antibody responses in PWH. The review will provide guidance and impetus for further research to improve the immunogenicity of these vaccines in this human population.
Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Sexually Transmitted Infections
 01:29
Immune Response Against Viral Pathogens
NK Cells
NK cells are a crucial part of our innate immune system, acting as the first line of defense against viral infections. These cells can recognize and kill infected cells without prior exposure to the virus, effectively slowing down the spread of infection. Additionally, NK cells produce proinflammatory...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:10
Retrovirus Life Cycles