Related Experiment Video
Updated: Jun 3, 2025
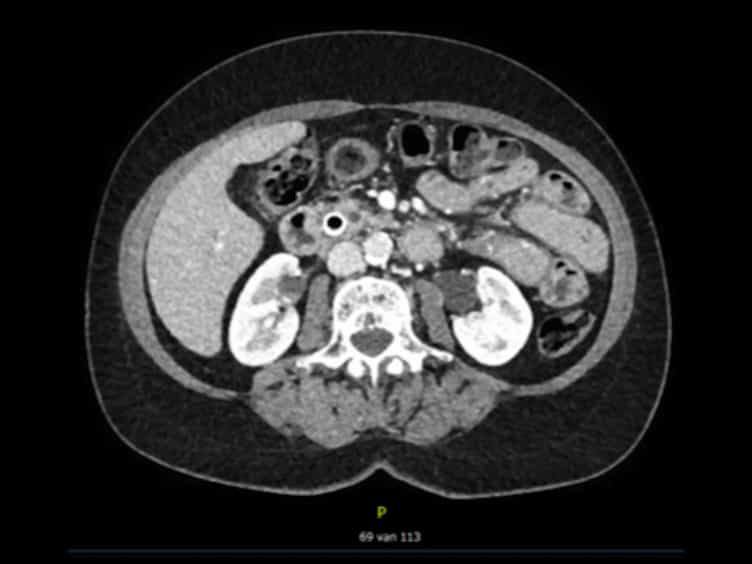

Laparoscopic Pancreatoduodenectomy With Modified Blumgart Pancreaticojejunostomy
Published on: June 17, 2018
Laparoscopic peritoneal mucinous cystadenoma debulking: A case report
Zhitang Guo1, Kui Long1, Zhanbin Chen1
1Department of Hepatopancreatobiliary Surgery, The Second Affiliated Hospital of Kunming Medical University, Kunming, China.

Rationale:
Peritoneal mucinous cystadenoma is rare in the clinic, lacks specific clinical manifestations, tumor markers, and imaging features, and is easily misdiagnosed and missed. Clinical practitioners should maintain a high level of vigilance. Here, we report a case of laparoscopic peritoneal mucinous cystadenoma stripping to improve our understanding of the disease.
Patient Concerns:
A 34-year-old woman was admitted to our hospital with a history of epigastric pain over the past year that had worsened over the previous 4 months. The patient had no history of trauma or surgery.
Diagnoses:
A computed tomography scan of the whole abdomen, as well as hepatobiliary and pancreatic scans and magnetic resonance cholangiopancreatography examinations, showed a low-density mass of approximately 5.8 × 4.8 cm between the right lobe of the liver and the right kidney. The lesion showed no significant enhancement on the enhanced scan, and analysis of tumor markers was normal. The preoperative diagnosis was cholelithiasis with cholecystitis and hepatic cysts.
Interventions:
It was proposed to perform "laparoscopic cholecystectomy + hepatic cyst decapitation and decompression" under general anesthesia; however, intraoperative exploration revealed that the abdominal cyst had originated from the right side of the peritoneum and was located between the liver and kidney. The surgical procedure was thus changed to "laparoscopic abdominal cyst removal + cholecystectomy."
Outcomes:
The patient recovered well and was discharged on the fourth postoperative day. Postoperative pathological examination (abdominal cyst) showed mostly serous cells partially covered with high columnar mucus cells, which was consistent with mucinous cystadenoma. The postoperative diagnosis was peritoneal mucinous cystadenoma and cholecystolithiasis with cholecystitis.
Lessons:
Clinical diagnosis of mucinous cystadenoma of the abdominal wall is difficult. The possibility of the disease should be considered when a cystic space is found in the abdominal cavity. Diagnosis depends on postoperative pathological examination, and surgery is the preferred treatment option. During the operation, attention should be paid to avoid rupture of the cyst wall and overflow of cyst fluid, and to avoid blind fenestration and drainage or puncture and aspiration sclerotherapy when the diagnosis is unclear.
More Related Videos
 03:34
Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
 03:55
Laparoscopic Posterior Radical Antegrade Modular Pancreatosplenectomy for Distal Pancreatic Carcinoma
Published on: December 29, 2023